Related Experiment Video
Updated: Aug 3, 2026


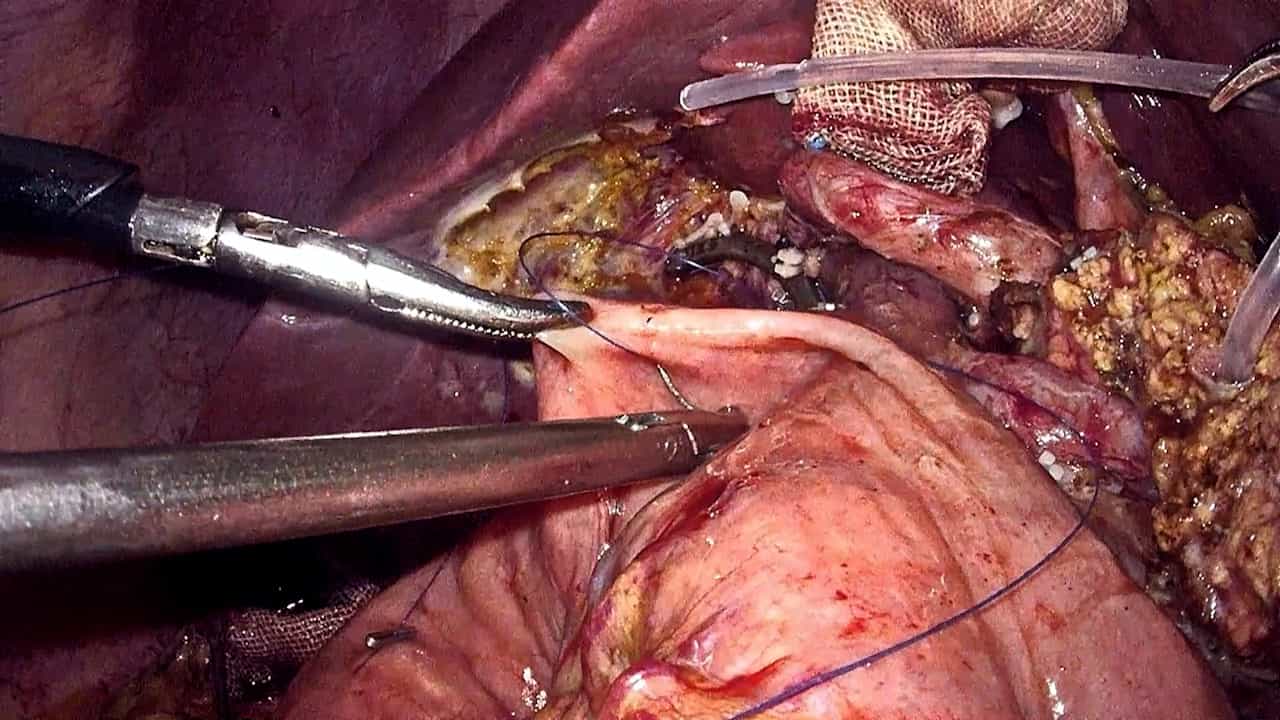
Retroperitoneal Laparoscopic Debridement and Drainage for Pancreatic Abscess
Published on: March 15, 2024
Pancreatic pseudocysts. When and how should drainage be performed?
1Department of Medicine, New York Medical College, Valhalla, USA.

Abstract:
A better definition of a pseudocyst that clearly separates it from acute fluid collection, improvements in imaging studies, and a better understanding of the natural history of pseudocysts have changed the concepts regarding their management. The old teaching that cysts of more than 6 cm in diameter that have been present for 6 weeks should be drained is no longer true. Indications for drainage are presence of symptoms, enlargement of cyst, complications (infection, hemorrhage, rupture, and obstruction), and suspicion of malignancy. The available forms of therapy include percutaneous drainage, transendoscopic approach, and surgery. The choice of procedure of depends on a number of factors, including the general condition of the patient; size, number, and location of cysts; presence or absence of communication of the cyst with the pancreatic duct; presence or absence of infection; and suspicion of malignancy. Expertise of the radiologist and the endoscopist is also a major deciding factor in the choice of therapy. Percutaneous catheter drainage is safe and effective and should be the treatment of first choice in poor-risk patients, for immature cysts, and for infected pseudocysts. Contraindications include intracystic hemorrhage and presence of pancreatic ascites. For mature cysts, in skilled endoscopic drainage should be given the first preference. It is less invasive, less expensive, and easier to perform with better outcomes in smaller pseudocysts and pancreatic head pseudocysts. Endoscopic expertise is limited, however, and at present endoscopic drainage cannot be advocated as the procedure for general use. In the absence of endoscopic expertise, percutaneous catheter drainage is the procedure of choice. Surgical treatment has been the traditional approach and is still the preferred treatment in most centers. Multiple pseudocysts, giant pseudocysts, presence of other complications related to chronic pancreatitis in addition to pseudocyst, and suspected malignancy are best managed surgically. Surgery is also the backup management in the event that percutaneous or endoscopic drainage fails. Because radiologic diagnosis of pseudocyst may be inaccurate in 20%; it is imperative to be sure that the cystic structure is not a neoplasm before percutaneous or endoscopic drainage. There have been no prospective, randomized trials that have evaluated the results of the three major modalities of therapy (percutaneous, endoscopic, and surgical), and before one can definitely recommend percutaneous drainage or endoscopic approach as the preferred initial mode of therapy, further studies are needed.
More Related Videos
 04:31
Reverse Needle Continuous Suture of the Pancreatic Duct to Jejunal Mucosal Pancreaticointestinal Anastomosis in Laparoscopic Pancreaticoduodenectomy
Published on: August 29, 2025
 05:11
Treatment of Middle-segment Pancreatic Benign Tumor Using Laparoscopic Central Pancreatectomy with End-to-end Pancreatic Duct Reconstruction
Published on: January 2, 2026
Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:22
Aneurysm IV: Nursing Management