Related Experiment Video
Updated: Jul 30, 2026
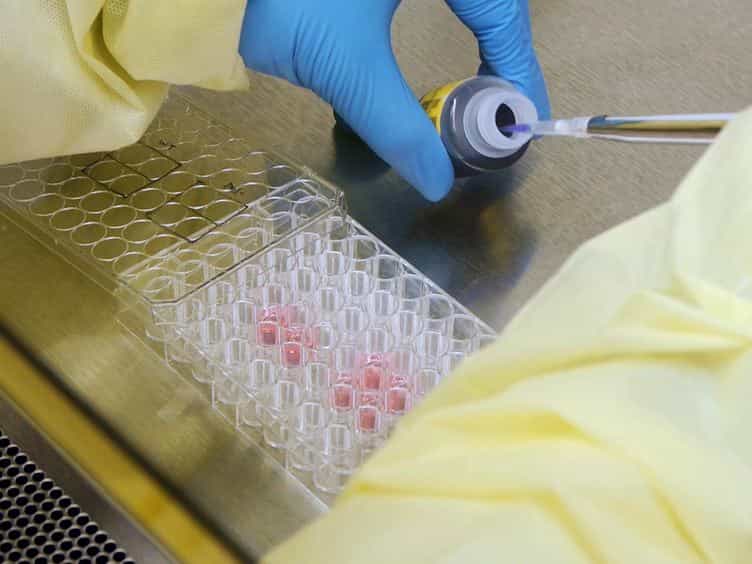

A Protocol for Analyzing Hepatitis C Virus Replication
Published on: June 26, 2014
Commentary: Iron metabolism in hepatitis C infection
1University of Kentucky School of Medicine, Lexington, USA.

Insights
Hepatitis C virus (HCV) infection can lead to chronic liver disease. Excess liver iron negatively impacts interferon treatment effectiveness in HCV patients, necessitating assessment and management through phlebotomy.
Area of Science:
- Hepatology
- Virology
- Internal Medicine
Background:
- Hepatitis C virus (HCV) infection, though declining, still causes significant chronic liver disease and mortality.
- Diagnosis involves antibody detection via recombinant immunoblot assays and confirmation with HCV RNA in serum.
- Hepatic iron overload is linked to poor response to interferon therapy in HCV patients.
Purpose of the Study:
- To highlight the negative impact of hepatic iron overload on interferon therapy efficacy in Hepatitis C virus patients.
- To recommend assessment and investigation of excess iron in HCV-infected individuals.
- To underscore the importance of managing hepatic iron levels for improved treatment outcomes.
Main Methods:
- Review of existing literature on Hepatitis C virus infection and hepatic iron metabolism.
- Analysis of patient data correlating hepatic iron levels with interferon therapy response.
- Clinical guidelines review for managing iron overload in HCV patients.
Main Results:
- HCV patients with significant hepatic iron accumulation demonstrate reduced response to interferon treatment.
- Normal hepatic iron stores are associated with better outcomes in interferon-treated HCV patients.
- Phlebotomy is identified as a practical and well-tolerated method for reducing iron levels.
Conclusions:
- Physicians must consider hepatic iron levels when treating HCV patients with interferon.
- Assessing and addressing hepatic iron overload is crucial for optimizing interferon therapy.
- Phlebotomy offers a viable solution for managing iron overload and potentially improving treatment success in HCV infection.
Abstract:
Hepatitis C virus (HCV) infections have started to decline, but up to 10,000 deaths each year are the consequence of chronic liver disease, following the infection. Laboratory testing identifies HCV-infected individuals using positive recombinant immunoblot assays to detect the presence of the antibody; the diagnosis is confirmed by detecting HCV RNA in serum. HCV-infected patients who have large accumulations of hepatic iron have not responded well to interferon therapy, compared to patients with normal hepatic iron stores. Physicians who treat patients infected with HCV should be aware of the detrimental effect of excess liver iron on interferon therapy. The degree of hepatic iron overload should be assessed and the reason for the excess iron should be investigated. Phlebotomy is the most practical method for iron removal and is well tolerated by patients with HCV infection.
More Related Videos
 06:28
Immunofluorescence to Monitor the Cellular Uptake of Human Lactoferrin and its Associated Antiviral Activity Against the Hepatitis C Virus
Published on: October 1, 2015
 11:34
A Competent Hepatocyte Model Examining Hepatitis B Virus Entry through Sodium Taurocholate Cotransporting Polypeptide as a Therapeutic Target
Published on: May 10, 2022
Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:25
Hepatitis
 01:28
Viral Hepatitis I: Introduction
 01:24
Cirrhosis II: Pathophysiology
 01:25
Jaundice