Related Experiment Video
Updated: Aug 11, 2026


A Magnetic Resonance Imaging Protocol for Stroke Onset Time Estimation in Permanent Cerebral Ischemia
Published on: September 16, 2017
False-negative diffusion-weighted MR findings in acute ischemic stroke
C Oppenheim1, R Stanescu, D Dormont
1Department of Neuroradiology, Groupe Hospitalier Pitié-Salpêtrière, Paris VI University, France.

Background And Purpose:
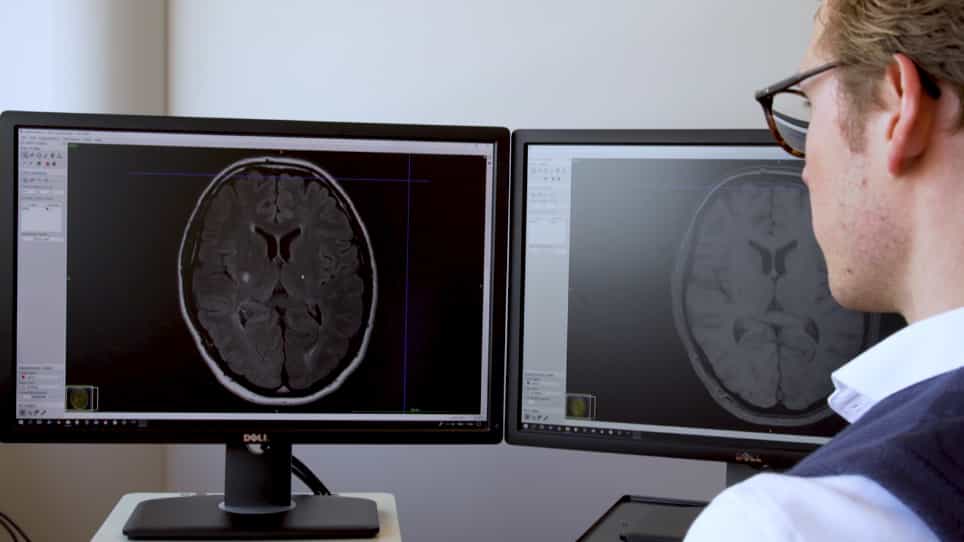
Lesions associated with acute stroke are often missed by diffusion-weighted imaging (DWI), suggesting that the sensitivity of this technique for detecting acute ischemic stroke may not be as high as initially thought. Our aim was to estimate the rate of false-negative DWI studies in patients with persistent neurologic deficit due to an ischemic stroke and to identify which stroke lesions are most likely to be missed by DWI.
Methods:
We reviewed MR images obtained within 48 hours after stroke onset in 139 patients admitted for symptoms consistent with ischemic stroke in whom the deficit lasted more than 24 hours. Cases of negative initial DWI findings with an ischemic lesion visible on follow-up MR studies and a final diagnosis of arterial ischemic stroke were analyzed in terms of delay between onset of symptoms and initial DWI (MR latency), size and vascular distribution of the lesions, and relationship to findings in patients with positive initial DWI results.
Results:
We found eight cases (5.8%) of false-negative initial DWI studies, of which four were positive on initial fluid-attenuated inversion recovery (FLAIR) imaging. Follow-up FLAIR/DWI showed a hyperintensity matching clinical presentation in all eight patients. The mean size of the lesion was 0.19 +/- 0.16 cm3. False-negative studies occurred more often in cases of stroke in the posterior (19%) than in the anterior (2%) circulation or when DWI was obtained within 24 hours after symptom onset. Of the six false-negative vertebrobasilar stroke lesions, five were located in the brain stem. In all, 31% of patients with vertebrobasilar ischemic stroke had a false-negative initial DWI study during the first 24 hours.
Conclusion:
A false-negative DWI study is not uncommon during the first 24 hours of ischemic stroke. Vertebrobasilar stroke should therefore not be ruled out on the basis of early negative DWI, especially when symptoms persist and are suggestive of this diagnosis.
Insights
Diffusion-weighted imaging (DWI) can miss acute ischemic stroke lesions, especially in the posterior circulation within 24 hours. Persistent symptoms warrant further investigation despite negative early DWI results.
Area of Science:
- Neurology
- Radiology
- Medical Imaging
Background:
- Diffusion-weighted imaging (DWI) is crucial for detecting acute ischemic stroke.
- Concerns exist regarding DWI's sensitivity in identifying all acute stroke lesions.
- False-negative DWI findings can delay diagnosis and treatment.
Purpose of the Study:
- To estimate the rate of false-negative DWI studies in patients with persistent neurologic deficits.
- To identify specific stroke lesion characteristics missed by DWI.
Main Methods:
- Retrospective review of MRI scans within 48 hours of stroke onset in 139 patients.
- Analysis of cases with initially negative DWI but positive follow-up imaging.
- Evaluation of lesion size, vascular territory, and timing of DWI acquisition.
Main Results:
- 5.8% of initial DWI studies were false-negative.
- False-negative rates were higher for posterior circulation strokes (19%) vs. anterior (2%).
- 31% of vertebrobasilar strokes had false-negative DWI within 24 hours, often in the brain stem.
Conclusions:
- False-negative DWI is not rare in the early hours of ischemic stroke.
- Vertebrobasilar strokes, particularly in the brain stem, are prone to false-negative DWI.
- Persistent symptoms suggestive of stroke necessitate considering DWI-negative cases, especially early on.
Related Concept Videos
 01:24
Magnetic Resonance Imaging
 01:21
Imaging Studies for Cardiovascular System IV: CMRI