Related Experiment Video
Updated: Aug 9, 2026
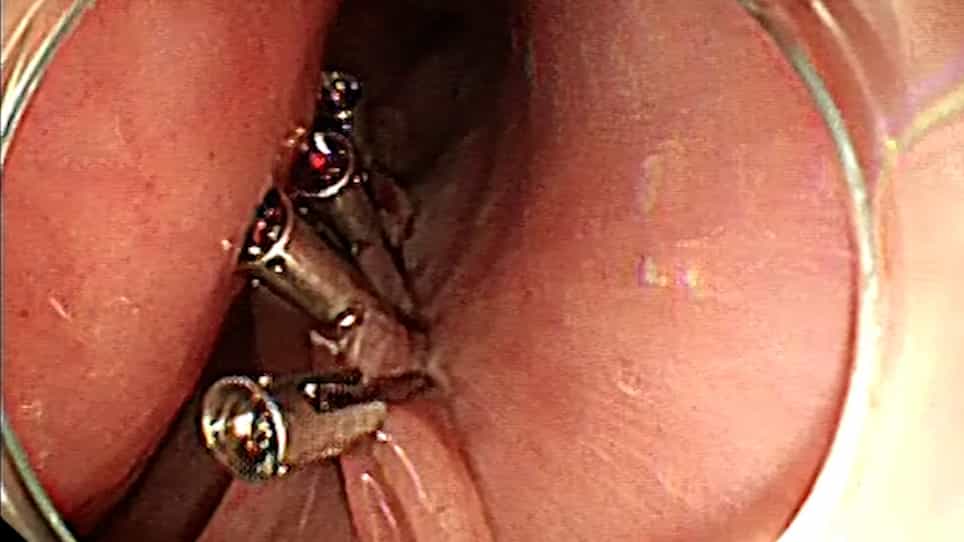
Use of the Scissor-Type Knife During the Peroral Endoscopy Myotomy Procedure for the Treatment of Achalasia
Published on: March 3, 2023
Etiology and treatment of achalasia in the pediatric age group
V M Piñeiro-Carrero1, C A Sullivan, P L Rogers
1Division of Pediatric Gastroenterology and Nutrition, Uniformed Services University of the Health Sciences, Bethesda, Maryland 20814-4799, USA. vpineiro@usuhs.mie

Insights
Pneumatic dilation is the primary definitive therapy for pediatric achalasia, offering safe and effective treatment. Heller myotomy serves as a safe surgical option for cases unresponsive to dilation.
Area of Science:
- Pediatric Gastroenterology
- Esophageal Motility Disorders
Background:
- Achalasia in children shares clinical features and therapeutic approaches with adult cases.
- Pharmacologic treatments offer only temporary symptom relief in pediatric achalasia.
- Botulinum toxin injections provide short-term, safe symptom palliation.
Purpose of the Study:
- To review the safety and effectiveness of pneumatic dilation for pediatric achalasia.
- To establish pneumatic dilation as the primary definitive therapy for achalasia in children.
- To identify effective alternative treatments for refractory pediatric achalasia.
Main Methods:
- Review of safety and effectiveness data for pneumatic dilation in pediatric achalasia.
- Evaluation of outcomes for graduated pneumatic dilation protocols.
- Assessment of Heller myotomy as a secondary treatment option.
Main Results:
- Pneumatic dilation is a safe and effective definitive therapy for pediatric achalasia.
- Graduated pneumatic dilation achieves satisfactory results in most pediatric patients.
- Heller myotomy is a safe and effective surgical treatment for children who do not respond to pneumatic dilation.
Conclusions:
- Pneumatic dilation should be considered the primary definitive treatment for pediatric achalasia.
- Heller myotomy is a viable and effective surgical option for refractory pediatric achalasia cases.
Abstract:
Achalasia in children bears many similarities to the disorder in adults, both in terms of clinical features and in terms of the approach to therapy. Pharmacologic management is of limited temporary benefit until more definitive therapy is undertaken. Intrasphincteric injections of botulinum toxin provides safe but short-term relief from symptoms. Based on our review of the safety and effectiveness of pneumatic dilation, we advocate this procedure as the primary form of definitive therapy for achalasia in children. In patients who do not achieve satisfactory results from a series of graduated pneumatic dilations, Heller myotomy provides safe and effective surgical treatment.


Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:27
Esophageal Achalasia
 01:11
Pyloric Obstruction