Related Experiment Video
Updated: Aug 17, 2026

Measurement of the Pressure-volume Curve in Mouse Lungs
Published on: January 27, 2015
Effect of positive end expiratory pressure on functional residual capacity and compliance in surfactant-treated
J Dinger1, A Töpfer, P Schaller
1Clinic of Pediatrics, Medical Faculty, Technical University of Dresden, Germany.

Insights
Lowering positive end expiratory pressure (PEEP) from 0.4 to 0.2 kPa improved lung compliance and reduced carbon dioxide in most preterm infants. These findings suggest lower PEEP levels may be beneficial after surfactant treatment.
Area of Science:
- Neonatal Medicine
- Respiratory Physiology
- Pediatric Critical Care
Background:
- Positive end expiratory pressure (PEEP) is a standard ventilation strategy for preterm infants.
- Surfactant treatment and PEEP both increase lung volume.
- Optimal PEEP levels require careful consideration to balance lung volume, compliance, and gas exchange.
Purpose of the Study:
- To investigate the impact of varying PEEP levels (0.2 to 0.4 kPa) on lung volume, respiratory system compliance, and arterial blood gases in preterm infants.
- To determine the optimal PEEP setting for preterm infants 72 hours post-surfactant treatment.
Main Methods:
- Functional residual capacity (FRC), respiratory system compliance, and arterial blood gases were measured in 20 preterm infants.
- Infants received surfactant treatment, and PEEP levels were adjusted to 0.2, 0.3, and 0.4 kPa in random order.
- Measurements were taken after maintaining each PEEP level for 20 minutes, with FRC assessed via SF6 washout.
Main Results:
- Increasing PEEP from 0.2 to 0.4 kPa led to increased FRC and oxygenation in all infants.
- In 16 infants, higher PEEP levels decreased compliance and increased paCO2.
- Conversely, 4 infants showed improved compliance and reduced CO2 with elevated PEEP.
Conclusions:
- Reducing PEEP from 0.4 to 0.2 kPa improved compliance and reduced paCO2 in the majority of infants.
- Lower PEEP levels (< 0.3 kPa) may be appropriate for preterm infants 72 hours after surfactant replacement.
- These findings highlight the clinical importance of individualized PEEP testing.
Unlabelled:
Positive end expiratory pressure is routinely used when ventilating preterm infants. Elevation of PEEP increases lung volume, as does surfactant treatment. The purpose of this study was to investigate the effect of various levels of PEEP within the range of 0.2 to 0.4 kPa on lung volume, compliance and gas exchange. We measured functional residual capacity, compliance of the respiratory system and arterial blood gases in 20 infants (median birth weight 1240 g, range 660-1690 g; median gestational age 28 weeks, range 24-32 weeks; postnatal age 3-4 days). The infants were studied at 72 hours after their last dose of natural surfactant. At this time the patients were routinely nursed at 0.3 kPa of PEEP, the PEEP level was lowered to 0.2 kPa or raised to 0.4 kPa in random order. The PEEP level was then changed to the third level 0.4 kPa or 0.2 kPa. Each new setting was maintained for 20 min before FRC, compliance and blood gases were measured. FRC was assessed using SF6 washout technique. Increasing PEEP from 0.2 to 0.3 to 0.4 kPa resulted in increases in FRC (p < 0.01) and oxygenation (ns) in all infants. In 16 infants compliance decreased and paCO2 increased with elevation of PEEP. Only in 4 infants compliance increased and CO2 fell.
Conclusion:
In the majority of our infants reduction of PEEP from 0.4 to 0.2 kPa resulted in increases in compliance and CO2 reduction. Our results might suggest that relatively low levels of PEEP < 0.3 kPa may be appropriate at 72 hours after surfactant replacement. Furthermore, these results underline the importance of PEEP test in clinical practice.

Related Concept Videos
 01:05
Breathing
 01:15
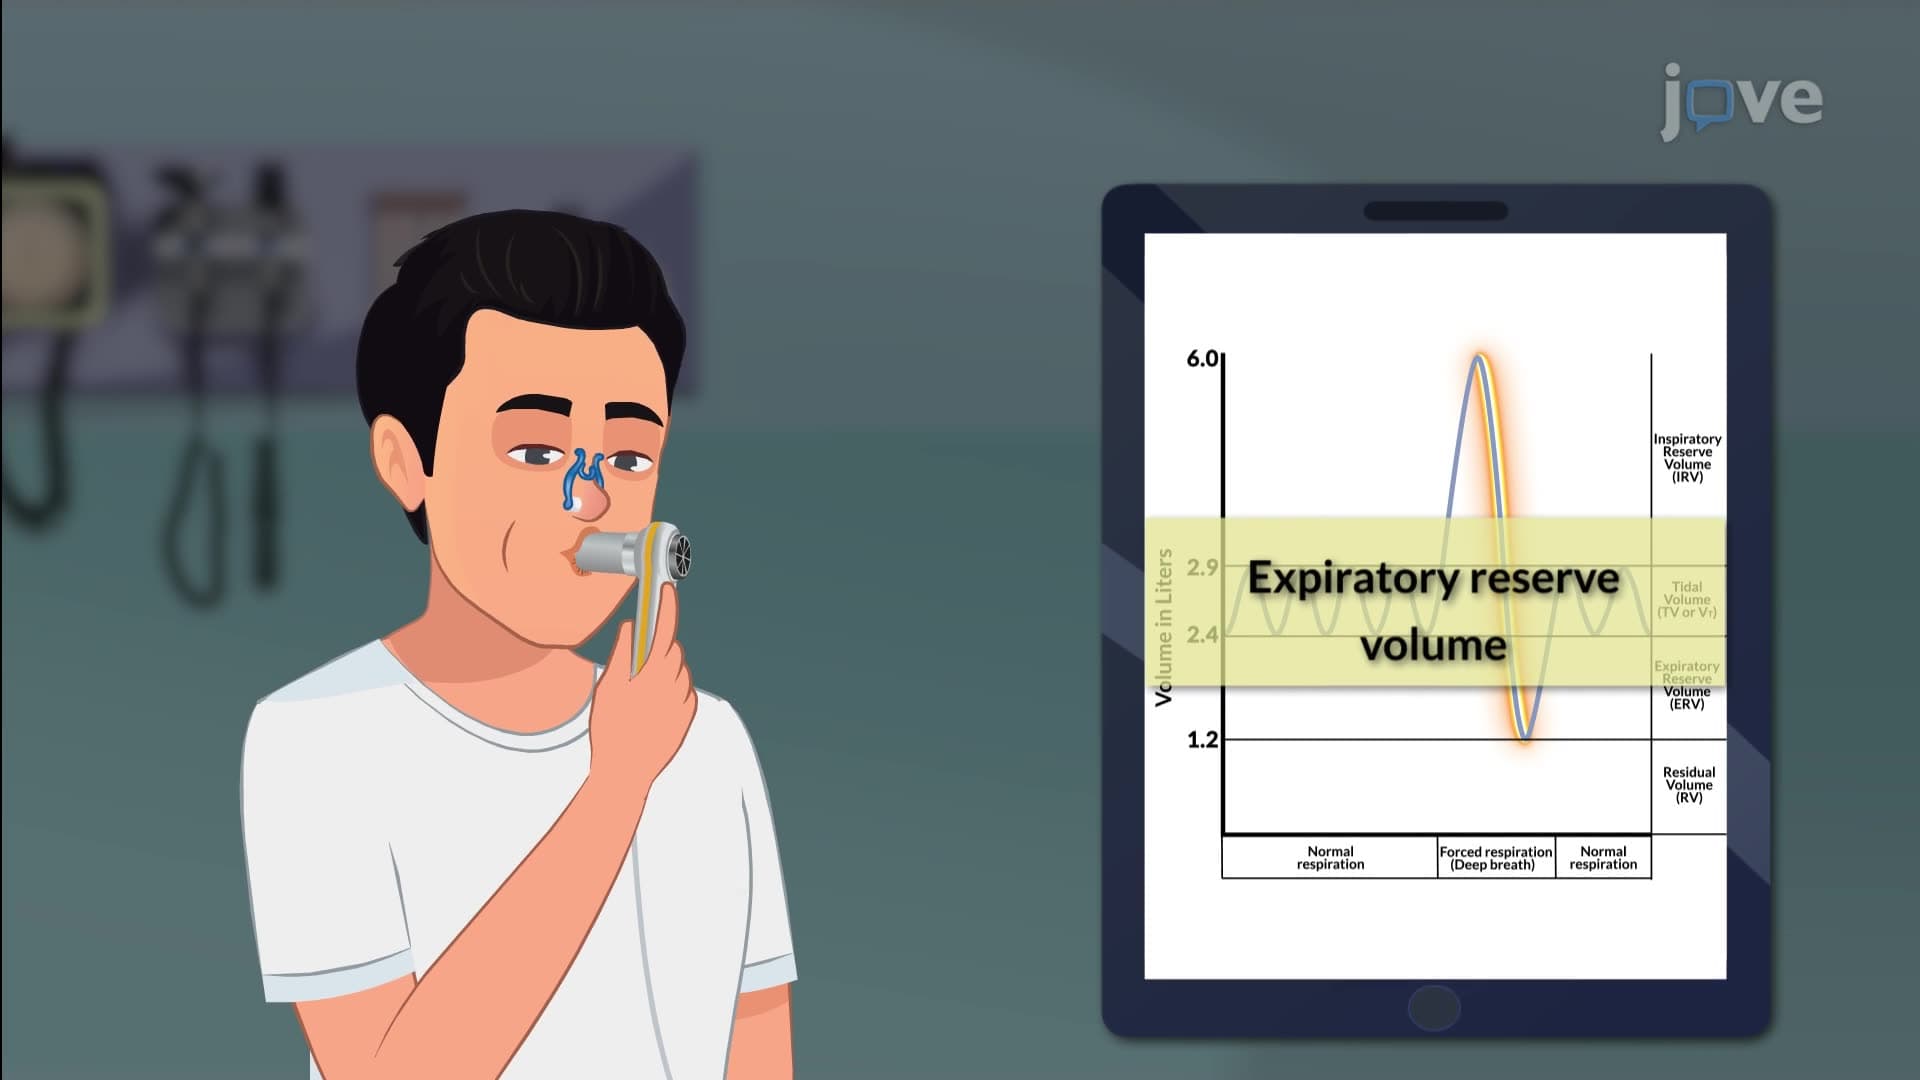
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:24
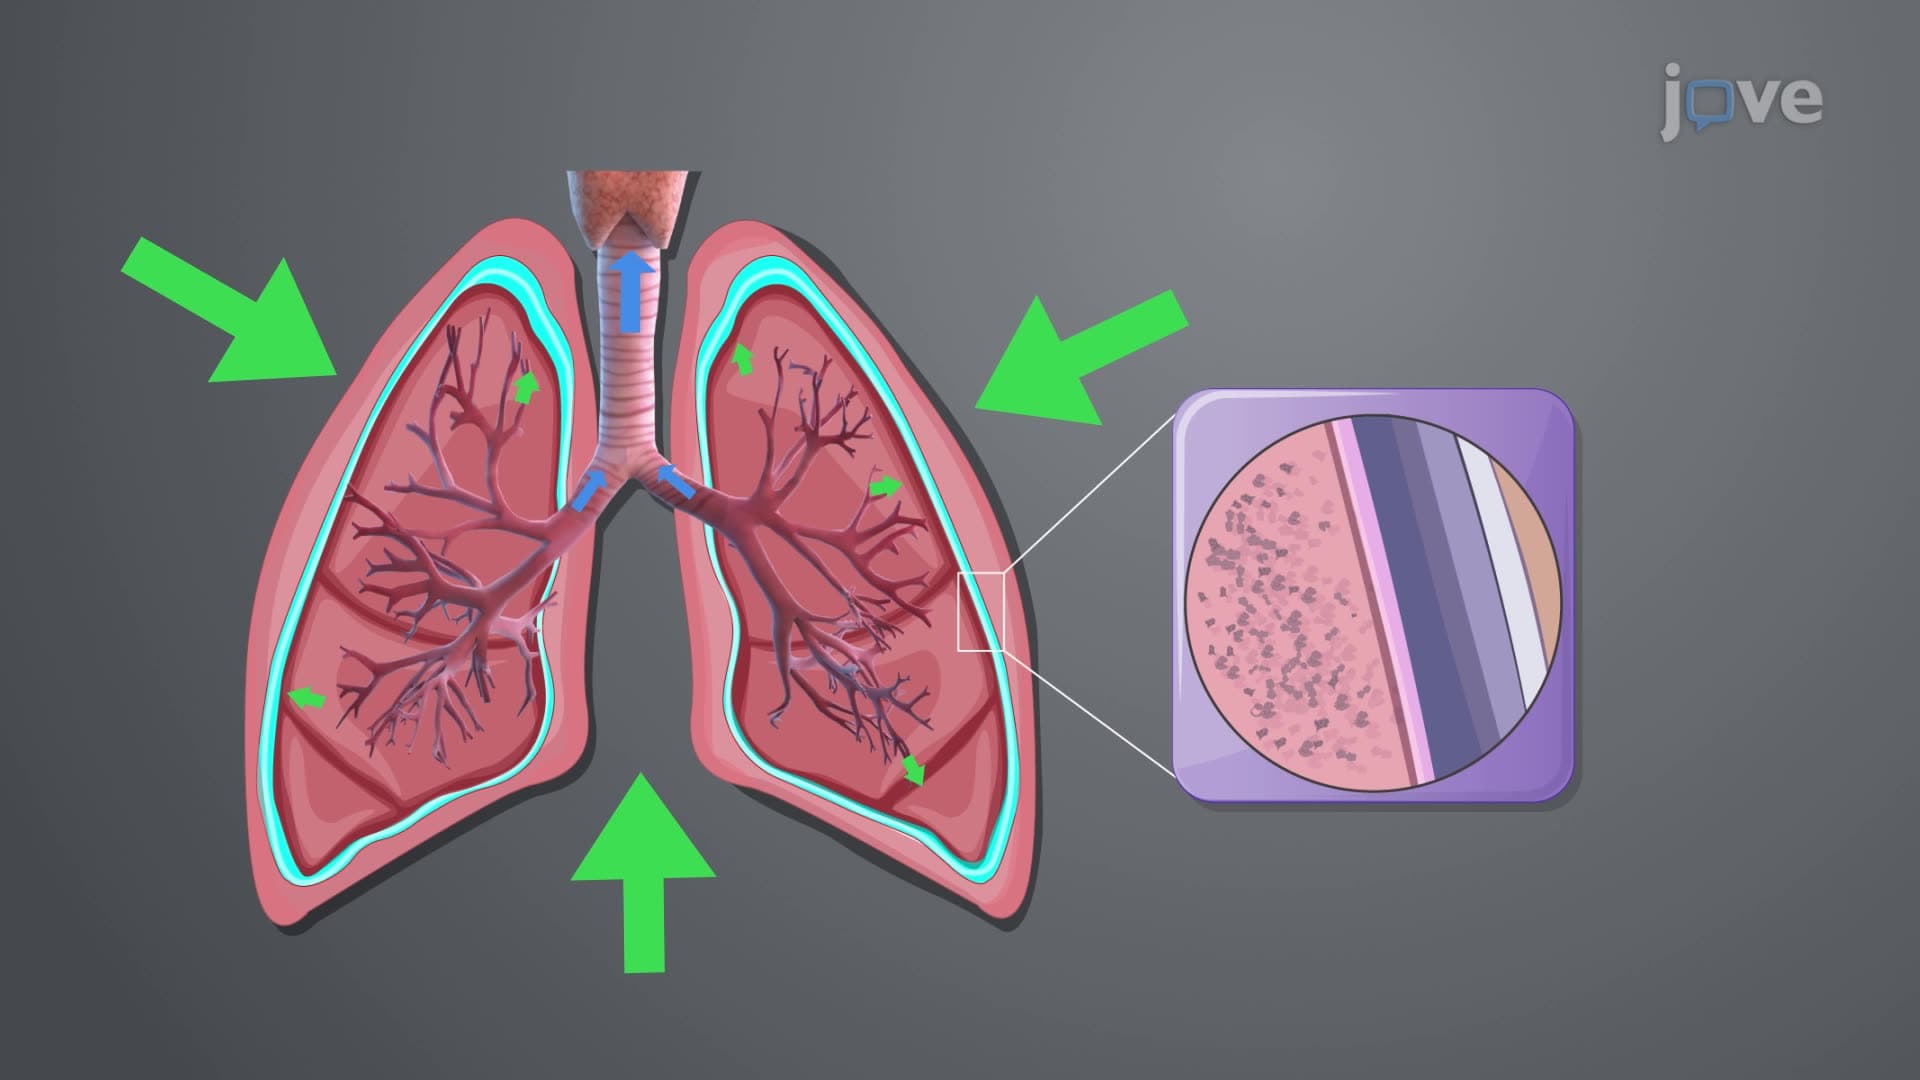
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)