Related Experiment Video
Updated: Oct 5, 2026

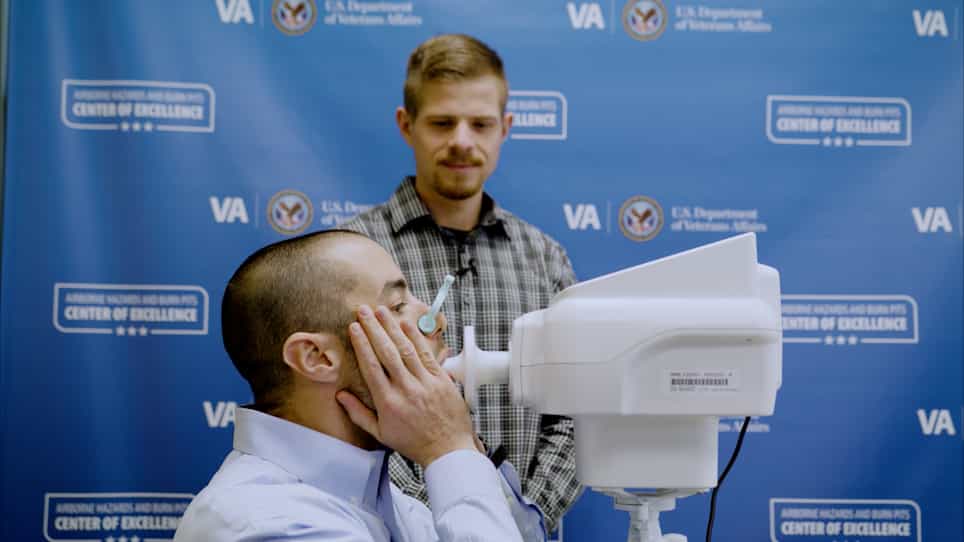
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Prospective trial of high-frequency oscillation in adults with acute respiratory distress syndrome
S Mehta1, S E Lapinsky, D C Hallett
1Departments of Medicine and Anesthesia, Mount Sinai Hospital, Toronto, Ontario, Canada.

Objective:
To evaluate the safety and efficacy of high-frequency oscillatory ventilation (HFOV) in adult patients with the acute respiratory distress syndrome (ARDS) and oxygenation failure.
Design:
Prospective, clinical study.
Setting:
Intensive care and burn units of two university teaching hospitals.
Patients:
Twenty-four adults (10 females, 14 males, aged 48.5 +/- 15.2 yrs, Acute Physiology and Chronic Health Evaluation II score 21.5 +/- 6.9) with ARDS (lung injury score 3.4 +/- 0.6, Pao2/Fio2 98.8 +/- 39.0 mm Hg, and oxygenation index 32.5 +/- 19.6) who met one of the following criteria: Pao2 < or =65 mm Hg with Fio2 > or =0.6, or plateau pressure > or =35 cm H2O.
Interventions:
HFOV was initiated in patients with ARDS after varying periods of conventional ventilation (CV). Mean airway pressure (Paw) was initially set 5 cm H2O greater than Paw during CV, and was subsequently titrated to maintain oxygen saturation between 88% and 93% and Fio2 < or =0.60.
Measurements And Main Results:
Fio2, Paw, pressure amplitude of oscillation, frequency, blood pressure, heart rate, and arterial blood gases were monitored during the transition from CV to HFOV, and every 8 hrs thereafter for 72 hrs. In 16 patients who had pulmonary artery catheters in place, cardiac hemodynamics were recorded at the same time intervals. Throughout the HFOV trial, Paw was significantly higher than that applied during CV. Within 8 hrs of HFOV application, and for the duration of the trial, Fio2 and Paco2 were lower, and Pao2/Fio2 was higher than baseline values during CV. Significant changes in hemodynamic variables following HFOV initiation included an increase in pulmonary artery occlusion pressure (at 8 and 40 hrs) and central venous pressure (at 16 and 40 hrs), and a reduction in cardiac output throughout the course of the study. There were no significant changes in systemic or pulmonary pressure associated with initiation and maintenance of HFOV. Complications occurring during HFOV included pneumothorax in two patients and desiccation of secretions in one patient. Survival at 30 days was 33%, with survivors having been mechanically ventilated for fewer days before institution of HFOV compared with nonsurvivors (1.6 +/- 1.2 vs. 7.8 +/- 5.8 days; p =.001).
Conclusions:
These findings suggest that HFOV has beneficial effects on oxygenation and ventilation, and may be a safe and effective rescue therapy for patients with severe oxygenation failure. In addition, early institution of HFOV may be advantageous.
Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:30
Acute Respiratory Failure-III
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:23
Acute Respiratory Failure-IV