Pulmonary interstitial fibrosis following near-drowning and exposure to short-term high oxygen concentrations

Chest
|September 1, 1975
PubMed

Related Concept Videos

Pulmonary Cycle: Exhalation01:17

Pulmonary Cycle: Exhalation

In terms of human respiration, the act of expelling air, known as exhalation (or expiration), operates on the principle of pressure gradients. During expiration, the pressure within the lungs exceeds that of the surrounding atmosphere. Under normal conditions, quiet breathing involves passive exhalation and is free of muscular contractions. This is because the exhalation process is driven by the natural elastic recoil of the lungs and chest wall, both of which have an inherent tendency to...
Acute Respiratory Failure-II01:21

Acute Respiratory Failure-II

Type I Respiratory Failure, or hypoxemic respiratory failure, occurs when the partial pressure of oxygen (PaO2) in arterial blood falls below 60 mmHg while breathing room air without a corresponding increase in arterial carbon dioxide levels (PaCO2). This condition highlights a significant impairment in the lungs' capacity to oxygenate the blood.
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
Pneumothorax-I01:26

Pneumothorax-I

A pneumothorax is a condition where air builds up in the space between the lung and the chest wall, causing the lung to collapse. This condition arises when air enters the space between the parietal and visceral pleura, disrupting the negative pressure essential for lung inflation. This can lead to a partial or complete collapse of the lung.
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.

Atelectasis II: Pathophysiology01:10

Atelectasis II: Pathophysiology

Atelectasis develops when alveoli lose their air and collapse inward. Because lung tissue is naturally elastic, these air sacs shrink rather than remaining open. Collapsed alveoli are no longer ventilated, reducing their role in gas exchange. Blood flow may continue in these regions, creating a ventilation–perfusion mismatch. Clinical findings include decreased breath sounds, dullness to percussion, reduced chest expansion, and decreased tactile fremitus as sound transmission through collapsed...
Chronic Obstructive Pulmonary Disease II: Emphysema01:23

Chronic Obstructive Pulmonary Disease II: Emphysema
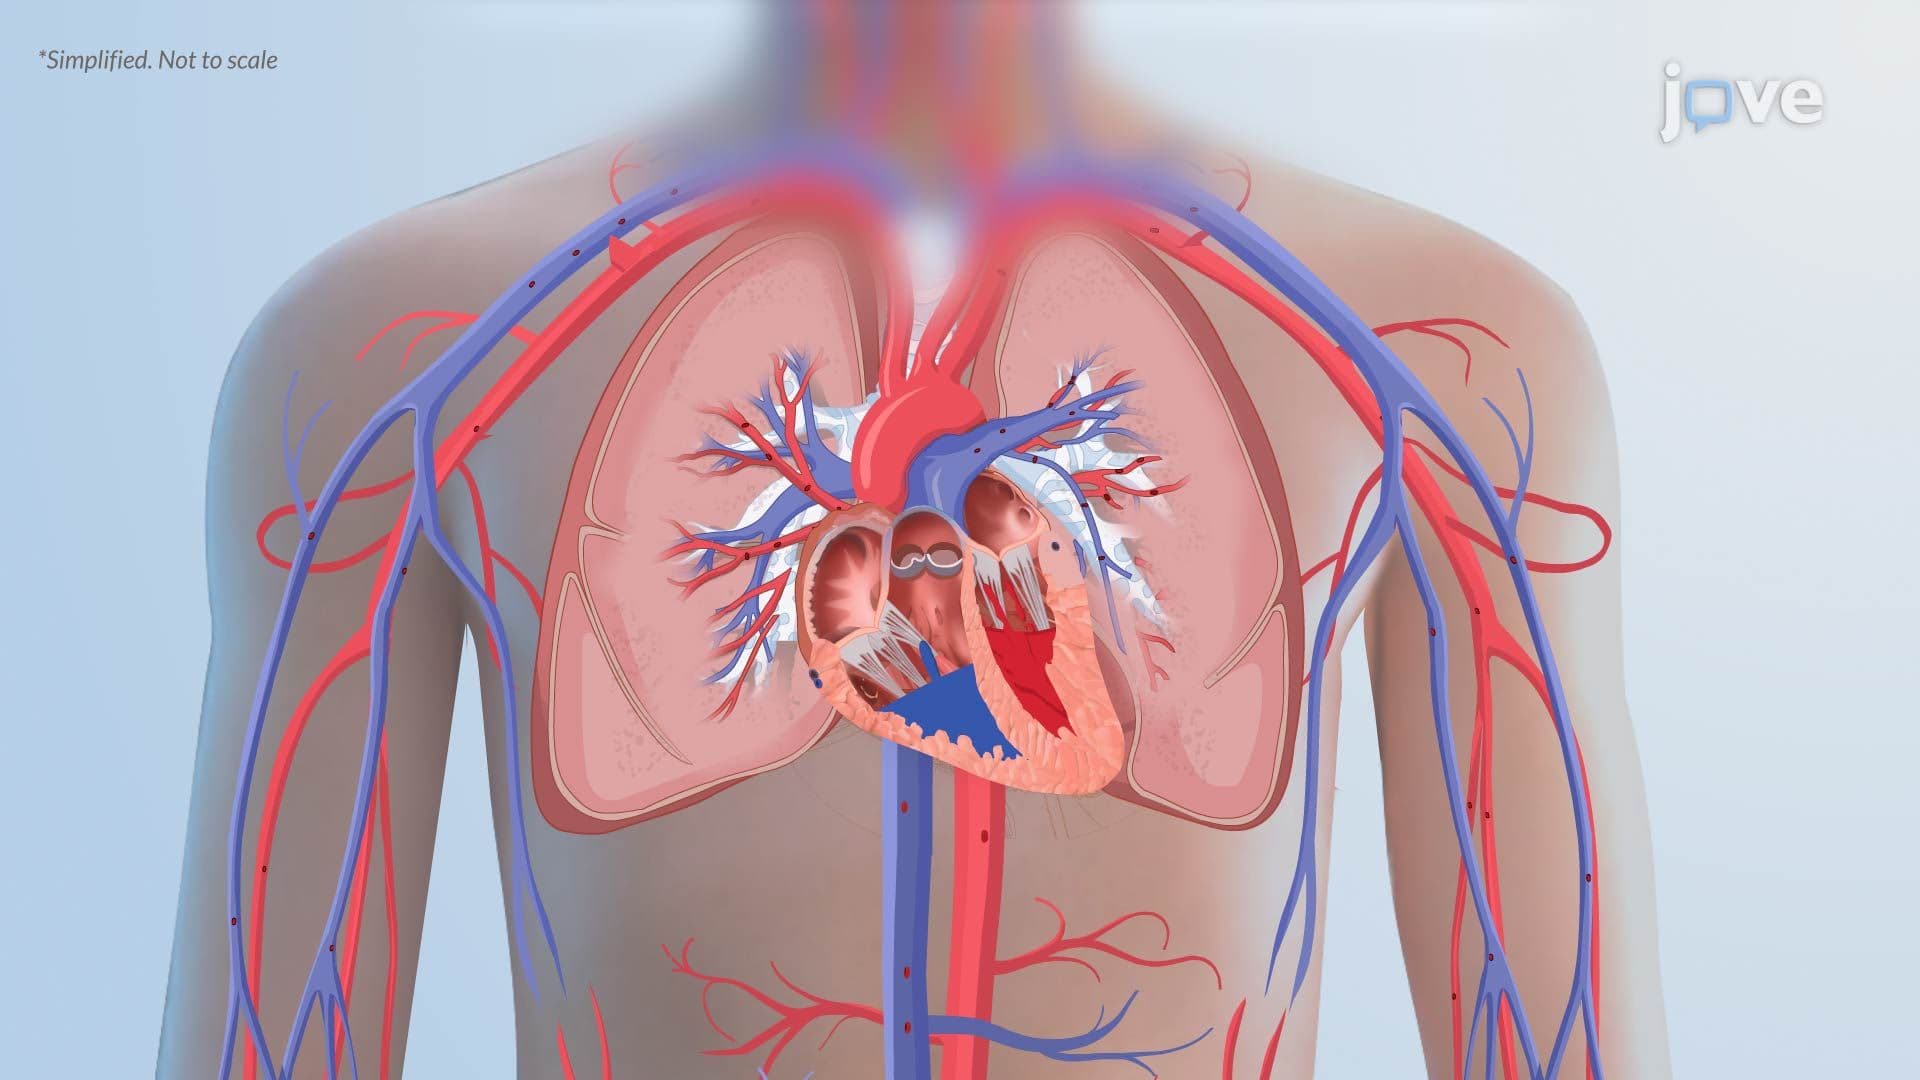
Emphysema, a major phenotype of chronic obstructive pulmonary disease (COPD), is characterized by irreversible destruction of alveolar walls and permanent enlargement of distal airspaces. Unlike chronic bronchitis, which primarily affects the airways, emphysema predominantly involves the lung parenchyma, where structural damage leads to airflow limitation.PathophysiologyIt most commonly results from prolonged exposure to cigarette smoke and other toxic gases, particularly cigarette smoke.
Pulmonary Edema II: Pathophysiology01:18

Pulmonary Edema II: Pathophysiology

Pulmonary edema is the accumulation of fluid in the interstitial and alveolar spaces of the lungs, impairing gas exchange and oxygen delivery. It may be cardiogenic or noncardiogenic, but both reduce oxygenation and lung compliance.Cardiogenic Pulmonary EdemaCardiogenic edema results from increased hydrostatic pressure in pulmonary capillaries, usually due to left ventricular dysfunction from myocardial infarction, heart failure, or valvular disease. Ineffective cardiac pumping causes blood to...



