Related Experiment Video
Updated: Aug 15, 2026


Procoagulant Platelet Characterization by Measuring Phosphatidylserine Exposure and Microvesicle Release from Human Purified Platelets
Published on: November 29, 2024
Common variations in platelet glycoproteins: pharmacogenomic implications
1Department of Cardiovascular Medicine, Desk F 25, The Cleveland Clinic Foundation, 9500 Euclid Avenue, Cleveland, Ohio 44195, USA.

Atherosclerosis and its complications are the result of complex interactions between the environment and genetic factors. Platelets play an important role in this disease process and antiplatelet agents are an essential part of its treatment. However, individual response to antiplatelet therapy is variable and agents that are safe and effective in one individual may be ineffective or harmful in another. It is likely that genetic factors are involved in this variance as platelet, and platelet-associated proteins are highly polymorphic. Up to 30% of natural variation in platelet reactivity is related to genetic inheritance. Rare inherited defects of platelet function due to the absence or reduced surface expression of platelet adhesion receptors have long been recognised. These cause minor bleeding defects and are usually clinically apparent. Antiplatelet agents should be avoided in these situations. The importance of the more common genetic variations or polymorphisms, which result in minor changes in the expressed protein and are often clinically silent, is unknown. Investigations are ongoing into the role of this variation in platelet physiology. A number of polymorphisms in platelet surface glycoproteins have received particular attention; the (A1/2) polymorphism resulting in conformational change at the amino terminus of the beta-3 chain of the platelet fibrinogen receptor glycoprotein (GP) IIb/IIIa and polymorphisms in the platelet collagen (GPIa/IIa and GPVI) and von Willebrand receptors (GPIb-IX). The (A2) allele has been associated with resistance to the antiplatelet agent aspirin and increased platelet responsiveness. The GPIa polymorphism has been associated with increased surface expression of GPIa and increased platelet adhesion to collagen. Recently, conflicting reports of the association of these polymorphisms with coronary artery disease (CAD) and its complications have been described. Mutations have also been identified in other platelet surface receptors including the recently identified G(i)-linked platelet adenosine diphosphate (ADP) receptor (P2Y(12)), targeted by the antiplatelet agents ticlopidine and clopidogrel. These discoveries have stimulated interest in the role of genetic factors in platelet physiology. In this article, the current knowledge of the influence of genetic make-up on antiplatelet therapy is discussed.
Atherosclerosis and its complications are the result of complex interactions between the environment and genetic factors. Platelets play an important role in this disease process and antiplatelet agents are an essential part of its treatment. However, individual response to antiplatelet therapy is variable and agents that are safe and effective in one individual may be ineffective or harmful in another. It is likely that genetic factors are involved in this variance as platelet, and platelet-associated proteins are highly polymorphic. Up to 30% of natural variation in platelet reactivity is related to genetic inheritance. Rare inherited defects of platelet function due to the absence or reduced surface expression of platelet adhesion receptors have long been recognised. These cause minor bleeding defects and are usually clinically apparent. Antiplatelet agents should be avoided in these situations. The importance of the more common genetic variations or polymorphisms, which result in minor changes in the expressed protein and are often clinically silent, is unknown. Investigations are ongoing into the role of this variation in platelet physiology. A number of polymorphisms in platelet surface glycoproteins have received particular attention; the (A1/2) polymorphism resulting in conformational change at the amino terminus of the beta-3 chain of the platelet fibrinogen receptor glycoprotein (GP) IIb/IIIa and polymorphisms in the platelet collagen (GPIa/IIa and GPVI) and von Willebrand receptors (GPIb-IX). The (A2) allele has been associated with resistance to the antiplatelet agent aspirin and increased platelet responsiveness. The GPIa polymorphism has been associated with increased surface expression of GPIa and increased platelet adhesion to collagen. Recently, conflicting reports of the association of these polymorphisms with coronary artery disease (CAD) and its complications have been described. Mutations have also been identified in other platelet surface receptors including the recently identified G(i)-linked platelet adenosine diphosphate (ADP) receptor (P2Y(12)), targeted by the antiplatelet agents ticlopidine and clopidogrel. These discoveries have stimulated interest in the role of genetic factors in platelet physiology. In this article, the current knowledge of the influence of genetic make-up on antiplatelet therapy is discussed.


Related Concept Videos
 01:29
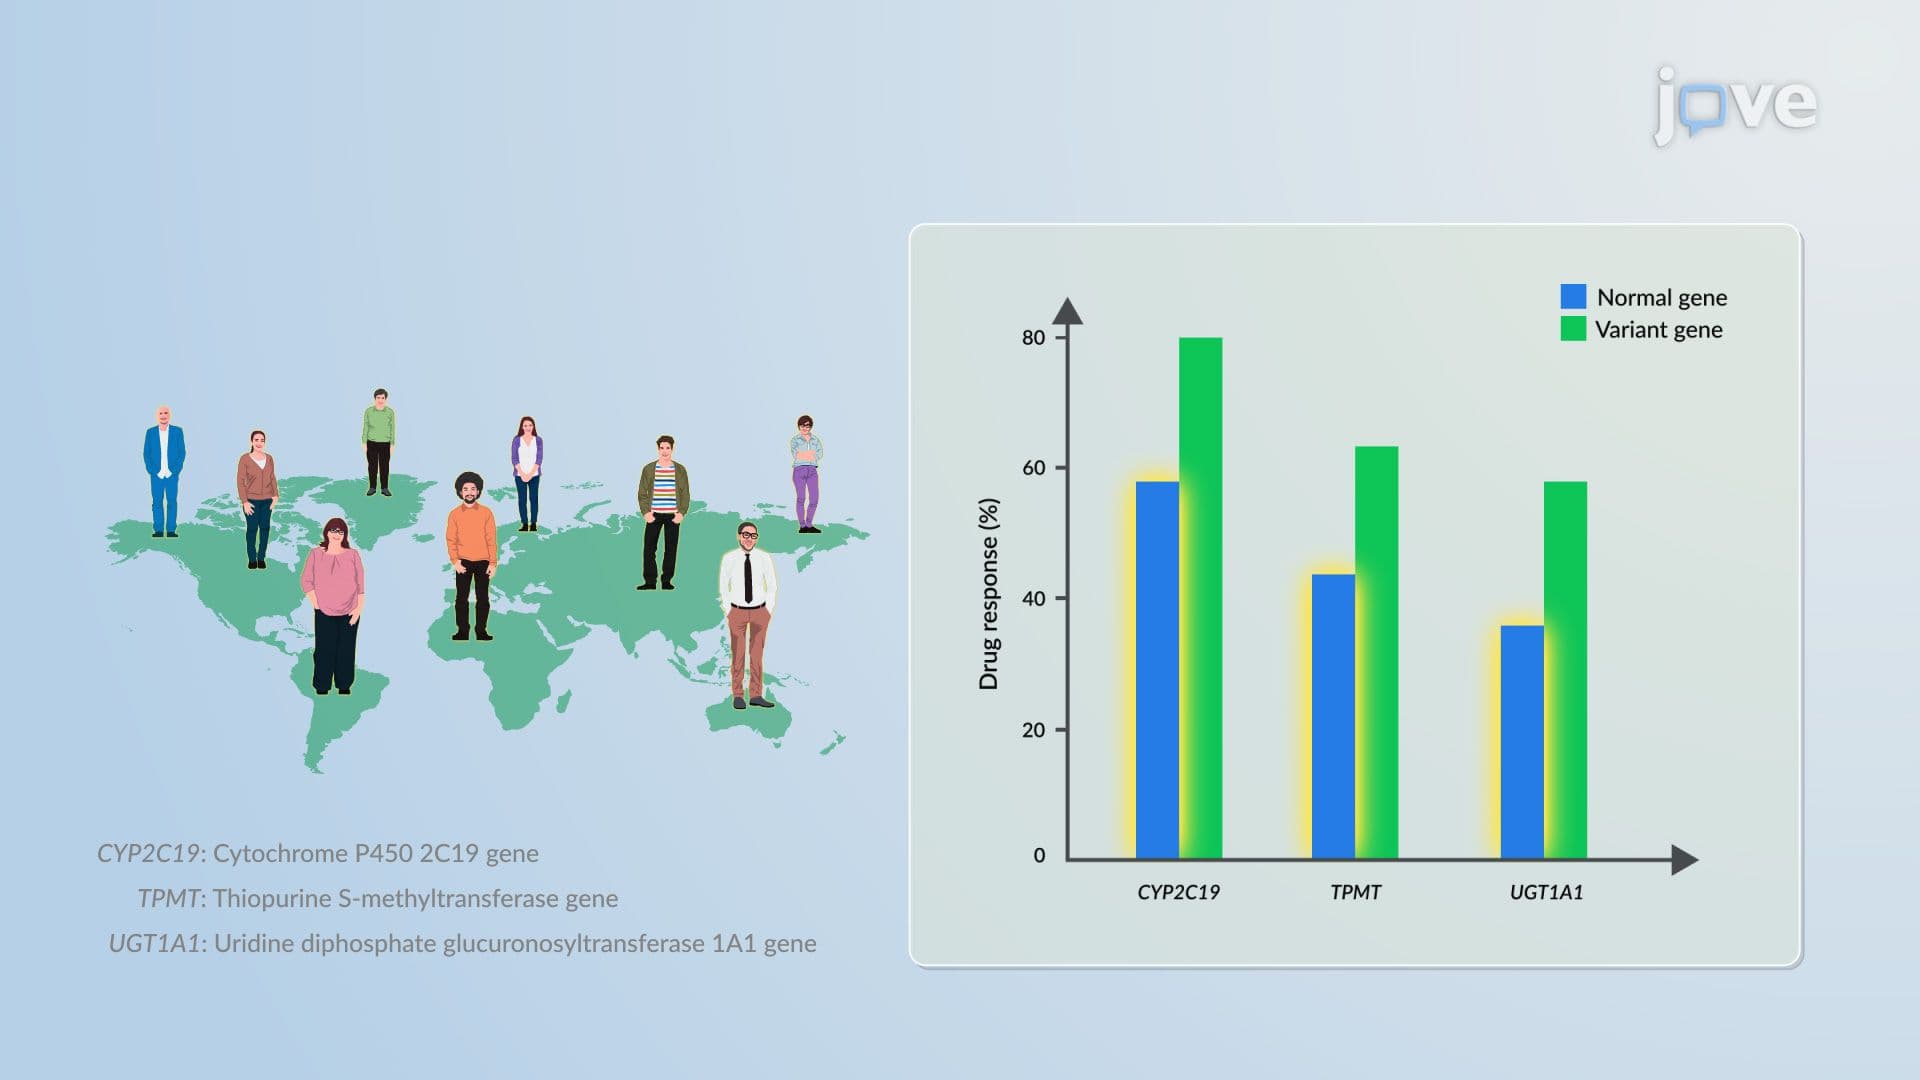
Pharmacogenetics and Pharmacogenomics: Overview
 01:27
Principles of Pharmacogenetics: Types of Genetic Variants
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu
 01:27
Pharmacogenetics of Drug Metabolism: Overview
 01:16
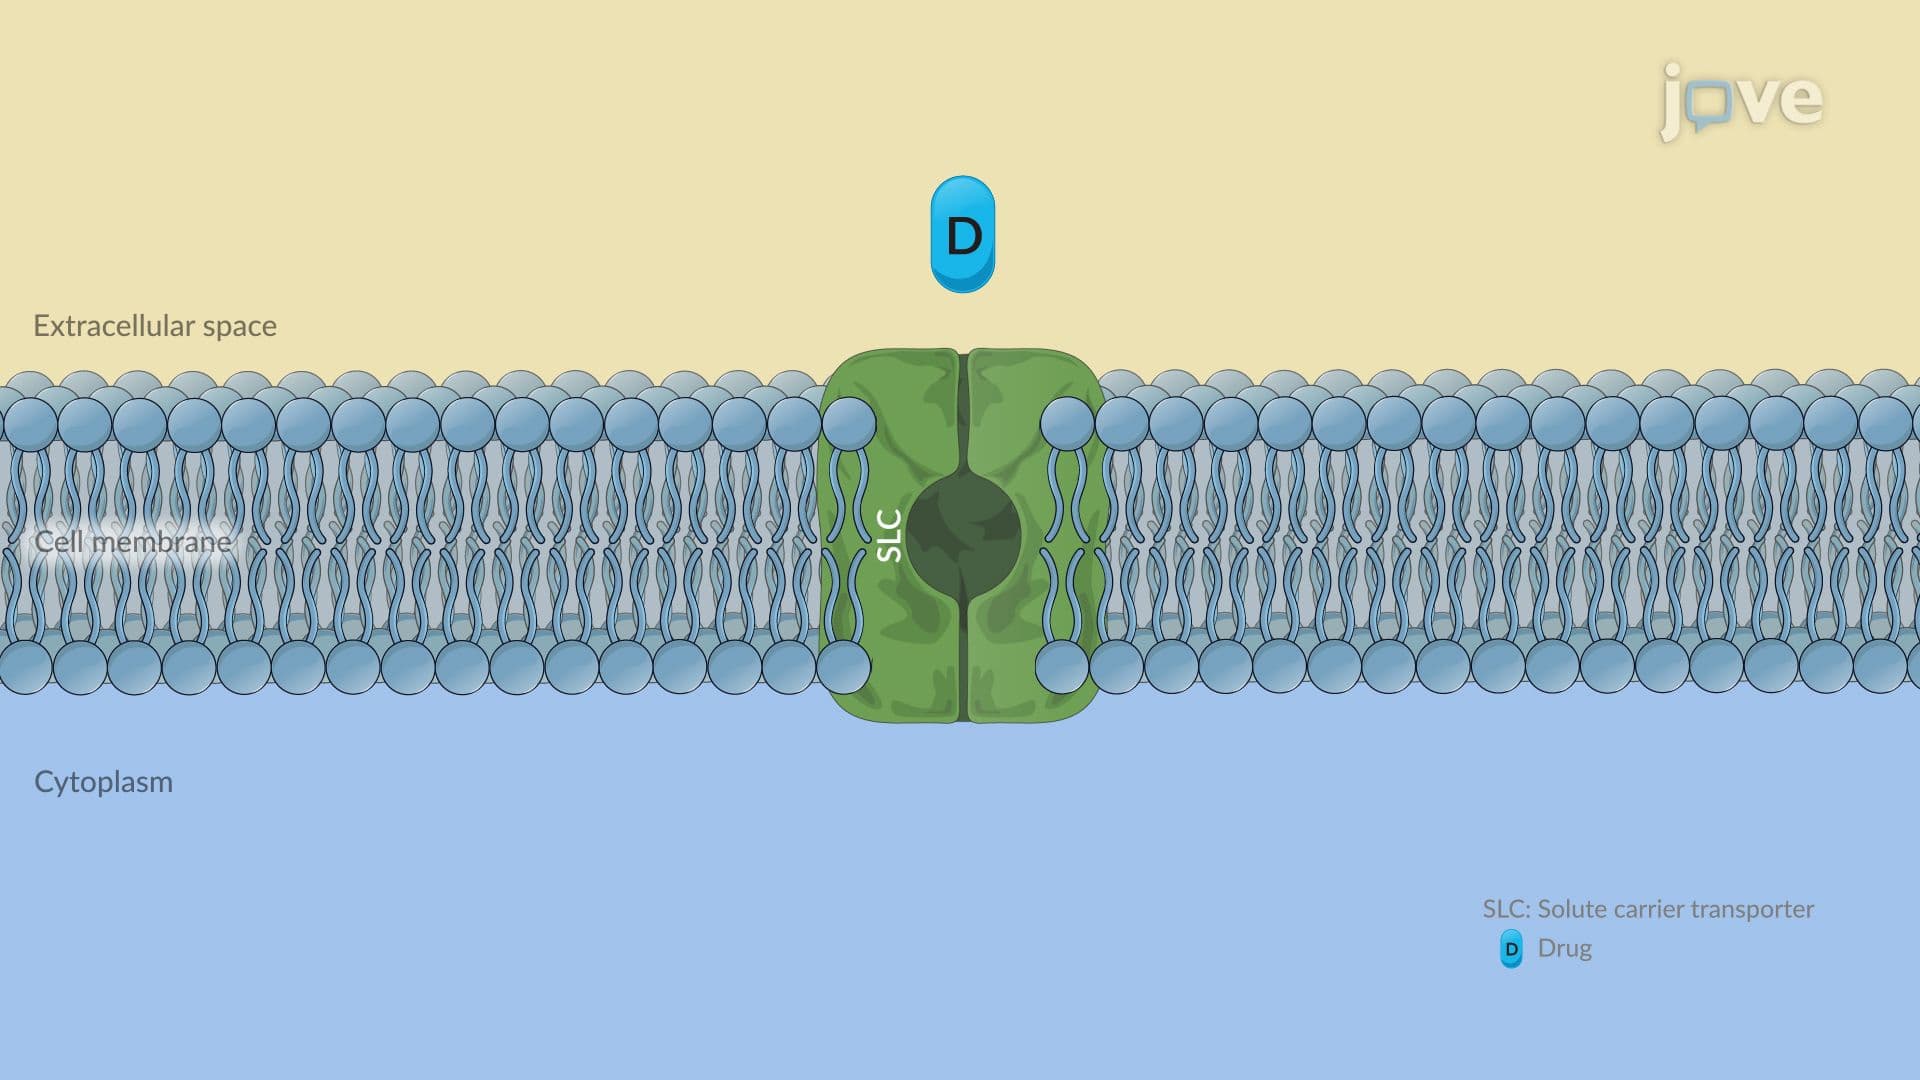
Pharmacogenetics of Drug Transporters: P-Glycoprotein and Solute Carrier Transporters
 01:29
Pharmacogenomics: Identification of New Drug Targets