Related Experiment Video
Updated: Sep 2, 2026
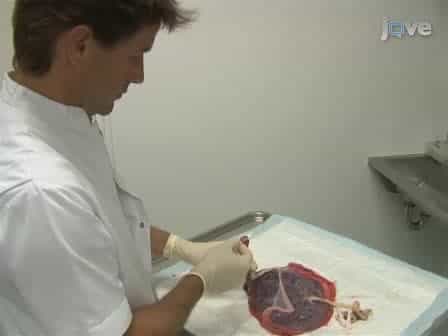

Accurate and Simple Evaluation of Vascular Anastomoses in Monochorionic Placenta using Colored Dye
Published on: September 5, 2011
Polycythemia in the newborn
Debra C Armentrout1, Valerie Huseby
1Univeristy of Texas--Houston Medical School, 77030, USA. Debra.C.Armentrout@uth.tmc.edu

Insights
Neonatal polycythemia, characterized by high red blood cell levels, affects 1-5% of newborns. This review clarifies its causes, symptoms, and nursing management, including treatment options like partial exchange transfusion.
Area of Science:
- Neonatology
- Pediatric Hematology
Background:
- Neonatal polycythemia, defined as a venous hematocrit exceeding 65%, impacts 1-5% of newborns.
- It stems from either excessive red blood cell production (active) or increased fetal blood volume (passive).
Observation:
- Elevated blood viscosity in polycythemia impairs organ blood flow.
- Limited nursing literature exists on neonatal polycythemia management.
- Clinical signs involve various organ systems.
Findings:
- This article details polycythemia's categories, etiologies, and pathophysiology.
- It covers clinical manifestations, supportive/specific therapies, and prognosis.
- A case study of partial exchange transfusion for a symptomatic infant is included.
Implications:
- Enhances nursing understanding of neonatal polycythemia.
- Provides a comprehensive overview for healthcare providers managing this condition.
- Highlights the challenges in treatment decisions for polycythemic infants.
Abstract:
Neonatal polycythemia, a venous hematocrit >65%, occurs in 1% to 5% of the total newborn population. Polycythemia can result from an excess production of red blood cells (active form) or from an increase in fetal blood volume (passive form). Clinical manifestations of polycythemia are caused by an increase in whole blood viscosity with a subsequent decrease in blood flow to organ systems. However, little information exists in the nursing literature concerning neonatal polycythemia. This article addresses the two categories of polycythemia and their etiologies; the involved pathophysiology; clinical manifestations of affected organ systems; supportive and specific therapies that can be used to treat polycythemic infants; the prognosis for polycythemic infants; and the difficulty healthcare providers face in deciding whether to treat this disorder. In addition, a case of a symptomatic infant who was treated with a partial exchange transfusion is presented.
More Related Videos

Related Concept Videos
 01:14
Erythropoiesis
 01:20
Overview of Hematopoiesis
Developmental Phases of Hematopoiesis
Initially, HSCs are formed in the embryonic yolk sac, a critical site for early blood cell production. These stem cells subsequently migrate to other...
01:14Erythropoiesis
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:24
Factors Affecting Erythropoiesis
Several factors influence the erythrocyte production rate, with tissue oxygen level being among the most critical. Intense exercise or high altitudes can cause tissue hypoxia, which triggers the kidneys to release more erythropoietin (EPO) into the bloodstream.
EPO then...