Related Experiment Video
Updated: Aug 25, 2026


Non-Nutritive Suck Parameters Measurements Using a Custom Pressure Transducer System
Published on: April 19, 2024
Relationship between respiratory control and feeding in the developing infant
Martha J Miller1, Pakaphan Kiatchoosakun
1Rainbow Babies and Children's Hospital, Division of Neonatology, 11100 Euclid Avenue, Cleveland, OH 44106-6010, USA. mjm8@po.cwru.edu

Insights
Infant feeding coordination involves complex muscle control for breathing and swallowing. While typically developed by 35 weeks, respiratory issues can interfere, and reflux doesn
Area of Science:
- Neuroscience
- Developmental Biology
- Pediatrics
Background:
- Simultaneous breathing and feeding (suck-swallow-breathe) requires intricate muscle coordination.
- This coordination involves the brainstem controlling buccopharyngeal and esophageal phases of feeding.
- Development of these functions is generally complete by 35 weeks post-conceptional age but can be affected by pathology.
Purpose of the Study:
- To elucidate the neural control mechanisms underlying infant feeding and respiration.
- To understand the developmental trajectory of coordinated breathing and swallowing.
- To investigate the relationship between gastro-oesophageal reflux and apnoea of prematurity.
Main Methods:
- Review of neurophysiological mechanisms controlling deglutition and respiration.
- Analysis of developmental milestones in infant feeding and swallowing.
- Examination of the role of the brainstem in regulating feeding reflexes and esophageal function.
Main Results:
- Brainstem nuclei control sequential muscle activity during the buccopharyngeal phase of feeding.
- Lower esophageal sphincter tone is regulated by brainstem nuclei and modulated by respiratory drive.
- Gastro-oesophageal reflux does not appear to be a common trigger for apnoea of prematurity.
Conclusions:
- Coordinated breathing and feeding in infants rely on complex brainstem circuitry.
- Disruptions in respiratory or neurological function can impair infant feeding coordination.
- While reflux can be symptomatic, it is not a primary cause of apnoea in premature infants.
Abstract:
Simultaneous breathing and nursing from a bottle or breast requires intricate coordination of the muscles that serve both respiration and feeding. During the buccopharyngeal phase of feeding reflex input to the brainstem from the oropharynx and larynx, as well as suprabulbar and chemoreceptor areas controls the sequential activity of the muscles of deglutition. Coordinated development of buccopharyngeal functions generally occurs by 35 weeks post-conceptional age in infants, but can be disrupted by respiratory disease or neuropathology. During the oesophageal phase of feeding, the bolus of food traverses the oesophagus and lower oesophageal sphincter, whose tone is also regulated by nuclei in the brainstem and modulated by respiratory drive. Control of the lower oesophageal sphincter gradually develops postnatally in premature infants. Although symptomatic gastro-oesophageal reflux can be problematic for the term or preterm infant, it does not appear that reflux is a common stimulus for apnoea of prematurity.

Related Concept Videos
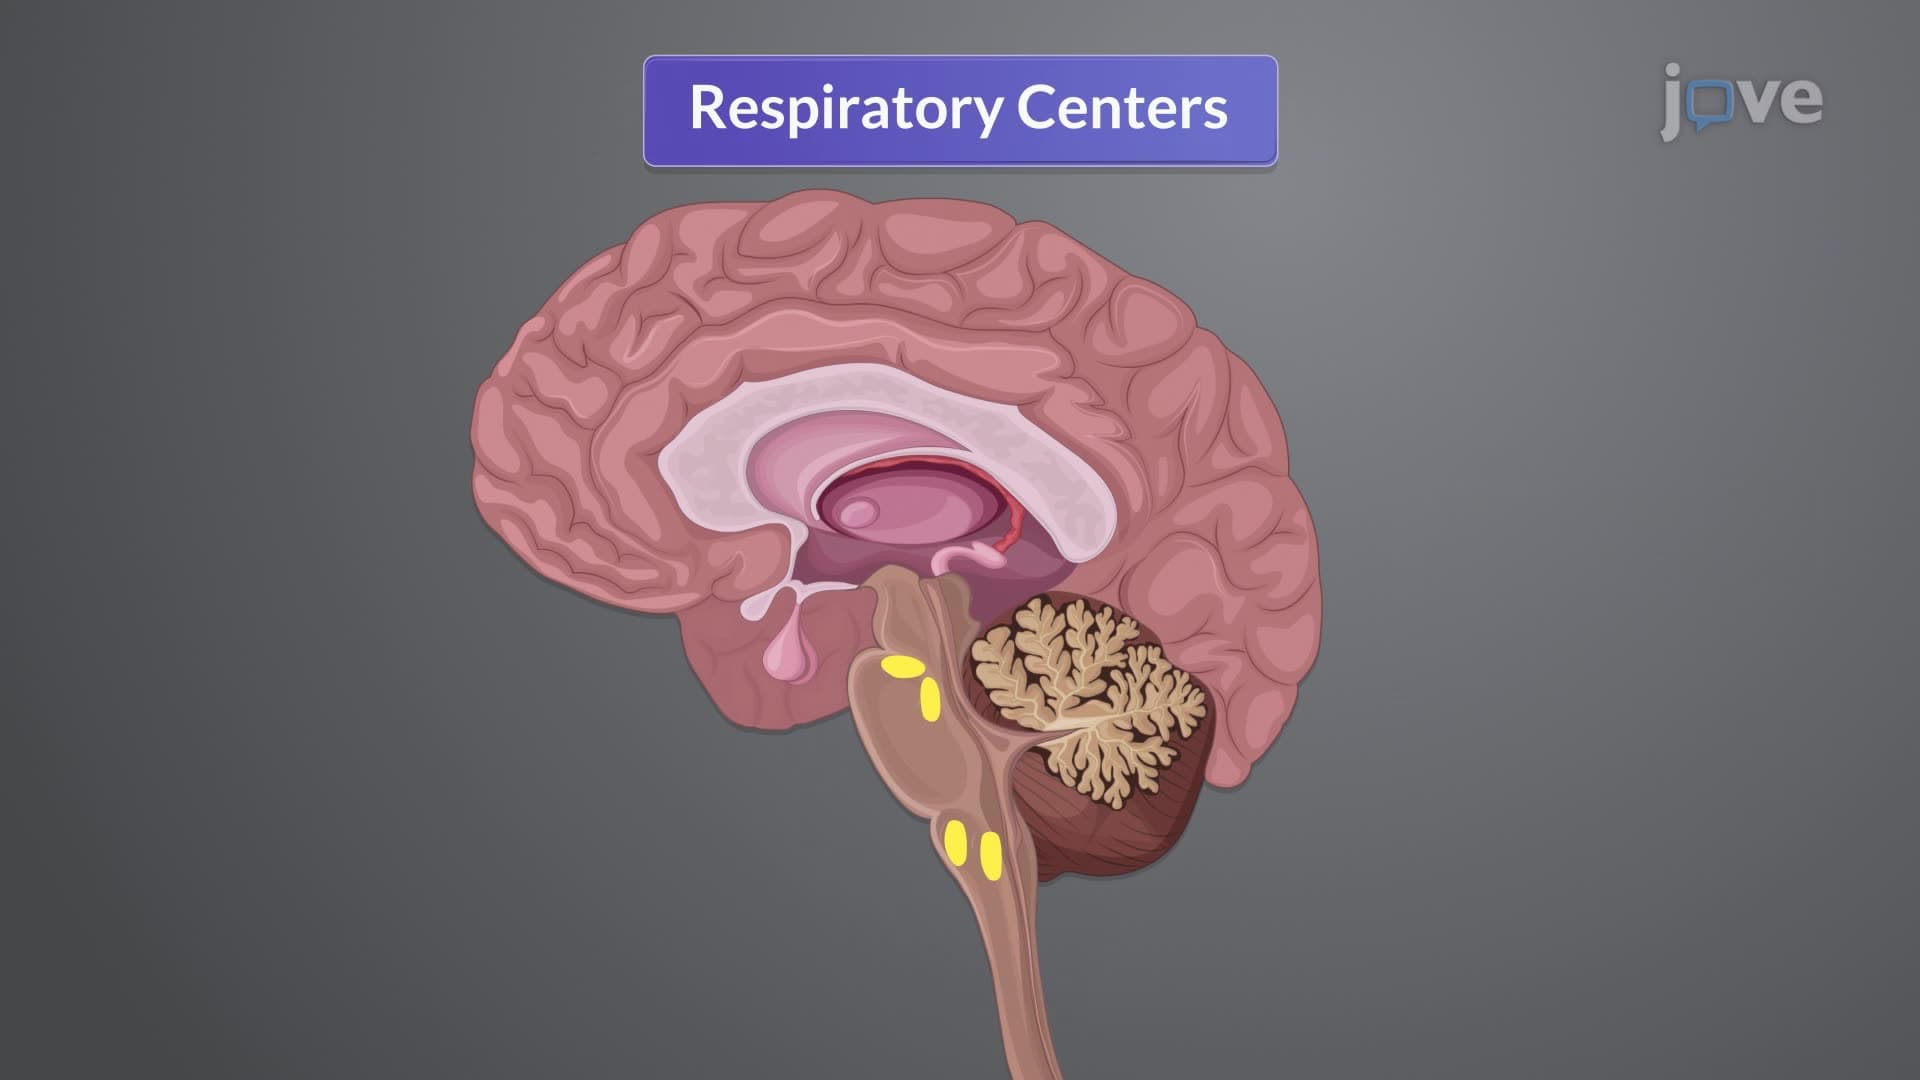 01:22
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers:
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:18
Neural Control of Respiration
Respiratory Centers in the Brainstem
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...
 01:17
Other Factors Affecting Respiration Centers
However, the ability to hold one's breath voluntarily is not limitless. When the CO2 concentration in the blood reaches a critical level,...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: