Related Experiment Video
Updated: Aug 23, 2026
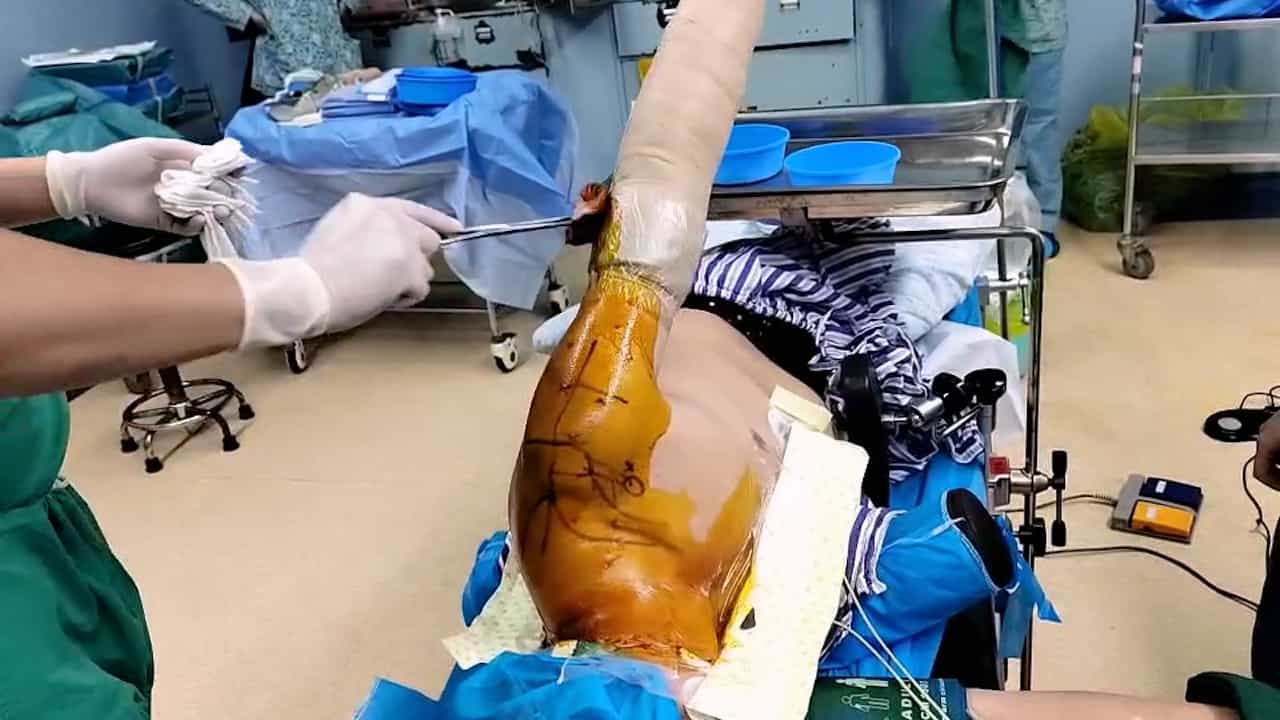
Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025
Arthroscopically assisted rotator cuff repair
Harald Boszotta1, Klaus Prünner
1Department of Trauma Surgery, Hospital of the Barmherzigen Brüder Eisenstadt, Eisenstadt, Austria. boszotta.h@eunet.at

Purpose:
The purpose of this study is to analyze the technique and value of arthroscopically assisted rotator cuff repair based on follow-up results after 3 years.
Type Of Study:
Case series.
Methods:
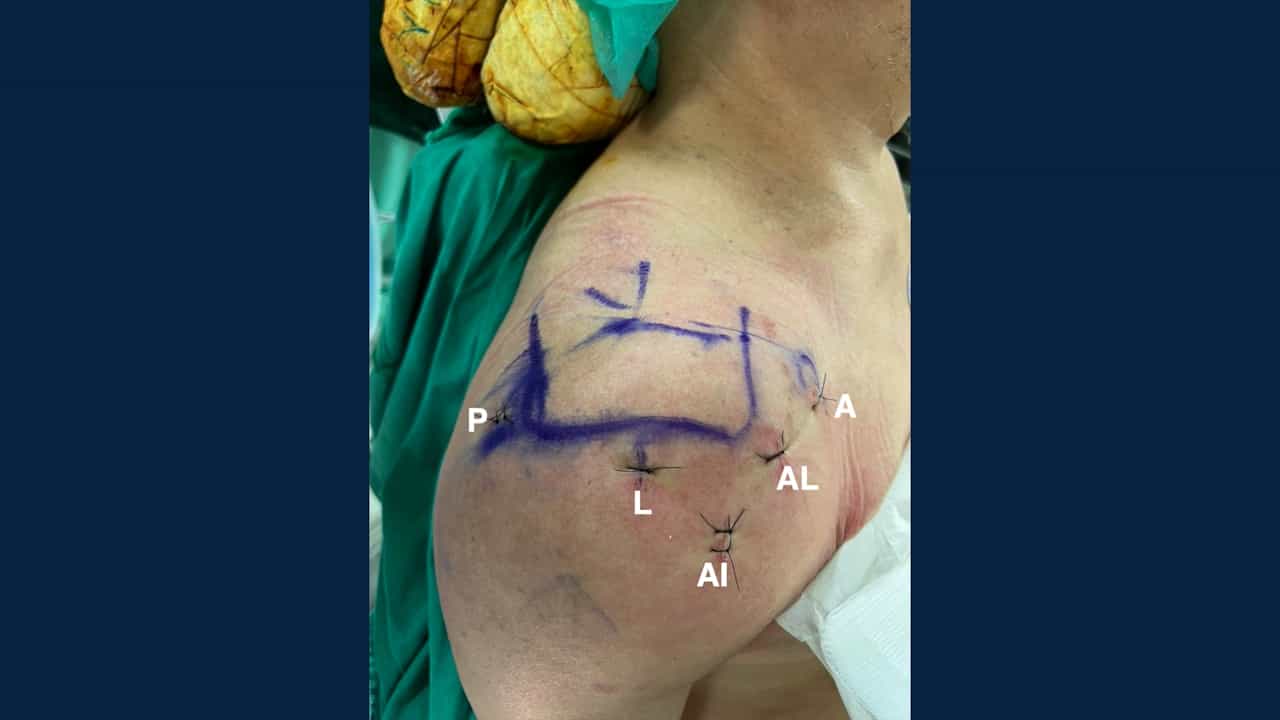
Since the beginning of 1997, 216 patients included in a clinical case series at the Department of Trauma Surgery of the Hospital of the Barmherzigen Brüder Eisenstadt have undergone arthroscopically assisted rotator cuff repair. Radiographic, clinical, and intraoperative parameters were carefully documented. All patients were treated with an arthroscopically assisted transosseous technique, in which bone tunnels are drilled with a target drill unit through the humeral head lateral to the biceps tendon from a third ventrocaudal incision on the humerus. The nonresorbable sutures placed into the cuff with a suture punch are passed transosseously and tied in the incision directly on the humeral head using a knot pusher. In December 2000, 84 patients (average age, 54.8 years; range, 28 to 74 years) underwent a clinical follow-up evaluation after a mean follow-up time of 35 months (28 to 44 months).
Results:
The average Constant score improved from a preoperative rating of 44.9 to a postoperative rating of 87.2. University of California, Los Angeles score was improved from 11.3 to 31.1 ( P <.001). Time of preoperative history, tear size, and condition of the long biceps tendon were found to have significant influence on results (P <.05). Thus, 20 patients with chronic, untreated tears of the long biceps tendon showed significantly worse results with a score of 81.8. Patients with curved or hooked acromion types (Bigliani II and III) showed significantly better results (P <.05) and patients with extensive tears had significantly worse results because of a residual strength deficit. The essential determinant was achievement of a stable tear closure with arthroscopic verification and documentation. Thus, 8 patients with a documented small gap between repaired cuff and bone showed a significantly worse rating in the Constant score, with 80.5 (P <.05). The complications encountered included development of seroma in one case and one case with frozen shoulder symptoms.
Conclusions:
Arthroscopically assisted repair of the rotator cuff was shown to be an effective procedure, guaranteeing good clinical results for medium- and large-sized tears with adequate mobility. Advantages include a primary stability comparable to that seen with open repair. Minimized trauma to soft tissue is associated with a lesser degree of postoperative pain and scarring and reduced hospitalization.
Level Of Evidence:
Level IV, case series.
Related Concept Videos
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...