Related Experiment Video
Updated: Aug 8, 2026

Diagnosis of Neoplasia in Barrett’s Esophagus using Vital-dye Enhanced Fluorescence Imaging
Published on: May 11, 2014
Detection of cardia intestinal metaplasia: do the biopsy number and location matter?
Prateek Sharma1, Christian McElhinney, Margarita Topalovski
1Divisions of Gastroenterology and Pathology, Department of Preventive Medicine and Public Health, Kansas Cancer Institute, University of Kansas School of Medicine, Kansas city, Missouri, USA.

Background And Aim:
Presence of intestinal metaplasia in the gastric cardia (cardia intestinal metaplasia, CIM) has been reported in 5-34% of patients undergoing upper endoscopy and is a topic of interest given the rising incidence of cancer in this location. The aim of this article is to determine the prevalence of CIM in biopsies obtained from two separate locations within the gastric cardia.
Methods:
Patients presenting to the endoscopy unit for upper endoscopy for any symptoms were invited to participate in the study. The biopsy protocol included: eight biopsies from the gastric cardia, four from upper cardia (forceps across the squamocolumnar junction), four from lower cardia (within 1 cm of upper cardia), and four each from the gastric body and antrum. All cardia biopsies were stained with hematoxylin and eosin (H&E) and alcian blue at pH 2.5 for the presence of goblet cells and the body/antrum biopsies were stained with Steiner silver stain for Helicobacter pylori detection. In patients testing negative for H. pylori by histology, a serology test was performed.
Results:
Sixty-five patients have been evaluated by this protocol; median age 54 yr (range: 34-81 yr), 63 males, 53 Caucasians, and 12 African Americans. The detection of CIM was as follows: upper cardia only, 7, both upper and lower cardia, 5, and lower cardia only, 7. Thus, CIM was detected in 12 patients (18%) in the upper cardia biopsies, in 12 patients (18%) in the lower cardia; overall prevalence of CIM was 29% (19 patients). Fifty-eight percent of CIM patients tested positive for H. pylori by either histology or serology. The addition of serology allowed for the detection of eight additional H. pylori-positive CIM patients.
Conclusions:
The prevalence of CIM in this study was similar (18%, four biopsies) at each location; however, if both locations were considered (eight biopsies), the prevalence increased to 29%. Thus, CIM prevalence may vary depending on the number of biopsies obtained as well as on the location of biopsies. Use of additional testing detects more patients who are H. pylori positive and should be performed if association of CIM with H. pylori is contemplated. Future endoscopic studies of the gastric cardia should specify the location of biopsies, the number of biopsies obtained, and the tests used to diagnose H. pylori.
More Related Videos
 07:05
Important Endpoints and Proliferative Markers to Assess Small Intestinal Injury and Adaptation using a Mouse Model of Chemotherapy-Induced Mucositis
Published on: May 12, 2019
 03:05
Establishment and Evaluation of a Risk Prediction Model for Pathological Escalation of Gastric Low-Grade Intraepithelial Neoplasia
Published on: February 16, 2024
Related Concept Videos
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:24
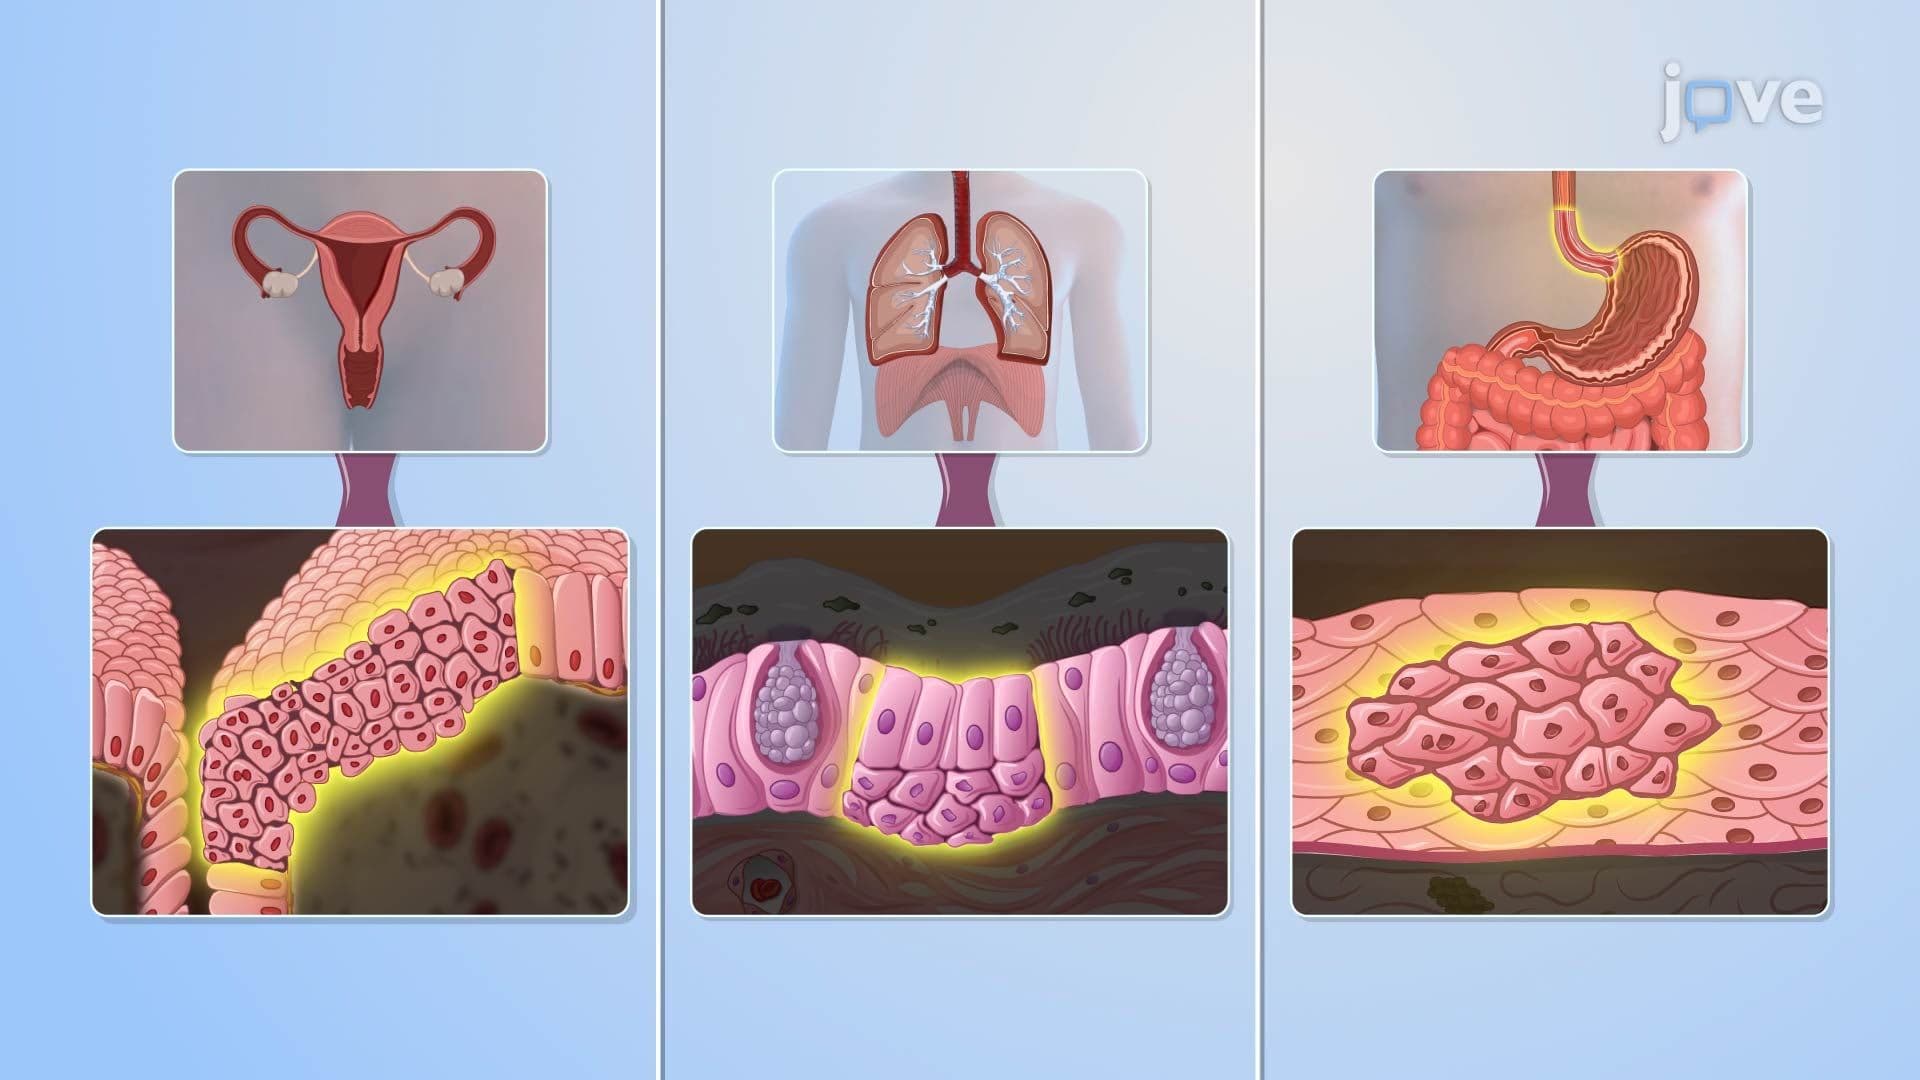
Cellular Adaptation IV: Dysplasia and Metaplasia