Related Experiment Video
Updated: Aug 18, 2026
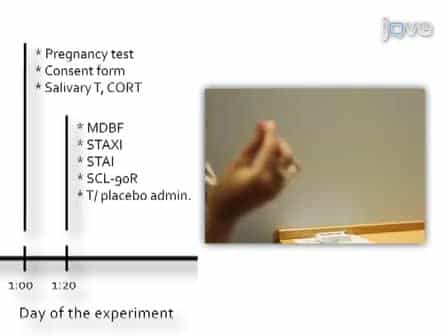

Combining Behavioral Endocrinology and Experimental Economics: Testosterone and Social Decision Making
Published on: March 2, 2011
Testosterone therapy--what, when and to whom?
1Department of Medicine, Evangelisches Krankenhaus Herne, Wiescherstrasse 24, 44623 Herne, Germany.

Abstract:
Testosterone therapy has been used for more than 60 years in the treatment of male hypogonadism. The classical forms of hypogonadism are comprised of primary testicular failure or insufficient testicular stimulation due to the lack of pituitary gonadotropins. Typical causes of primary hypogonadism are Klinefelter's syndrome, anorchia or acquired disturbances of testicular function. Secondary hypogonadism is characterized by insufficient production of pituitary gonadotropins, due either to pituitary failure or defects at the hypothalamic level. It is unequivocally accepted in clinical practice that any male with inadequately low testosterone production for his age will require androgen therapy. In addition to the classical forms of hypogonadism, the past decade of research has clearly demonstrated that, with increasing age, many men will suffer from decreasing testosterone production. About 15-25% of men over the age of 50 years will experience serum testosterone levels well below the threshold considered normal for men between 20 and 40 years of age. Studies substituting testosterone in elderly men with low serum testosterone have shown that men with clinical symptoms identical to the symptomatology of classical hypogonadism will benefit most from such therapy. Therefore, it is the general consensus to treat men with age-related hypogonadism only when clinical symptoms are present that can be potentially corrected by testosterone administration. Until recently, intramuscular injections of esters, such as testosterone enanthate, have been the mainstay of testosterone therapy. The introduction of testosterone patches has not challenged this approach, since many users of patches suffer from moderate to severe skin reactions. Some oral testosterone formulations have proven to be problematic, as absorption can be variable, bioavailability is frequently poor, due to the first-pass effect of the liver, and frequent administration is often required. Oral testosterone undecanoate avoids, at least partially, the first-pass effect of the liver. However, plasma testosterone levels generally undergo large fluctuations. The large fluctuations in serum testosterone levels caused by conventional intramuscular injections result in unsatisfactory shifts in mood and sexual function in some men, which, combined with the frequency of injections, make the intramuscular mode of delivery far from ideal. Recently, a hydroalcoholic gel containing 1% testosterone has proven to be as efficient as a testosterone patch, but with fewer side-effects and a higher grade of patient satisfaction. Doses of 50-100 mg gel applied once daily on the skin deliver sufficient amounts of testosterone to restore normal hormonal values and correct the signs and symptoms of hypogonadism. The gel has been shown to be effective and successful in patients in the United States, who have benefited from its availability for almost 3 years. In the near future, intramuscular injections of testosterone undecanoate will become commercially available. Such injections have a very favorable pharmacokinetic profile, with one injection every 3 months maintaining serum testosterone well within the normal range. In phase III studies, intramuscular testosterone undecanoate proved to be as efficient as testosterone enanthate, with only one-quarter of the number of injections required and more stable serum testosterone levels. Thus, the new application modes--hydroalcoholic gel (for example, Testogel, Schering AG, Germany) and intramuscular testosterone undecanoate (Nebido, Schering AG, Germany)--appear to be the methods of choice in the near future, one being very suitable for hormone therapy in elderly men, the other for long-term substitution in classical forms of hypogonadism.
Insights
Testosterone therapy effectively treats male hypogonadism, including age-related forms. Newer formulations like testosterone gel and long-acting injections offer improved efficacy and patient satisfaction compared to older methods.
Area of Science:
- Endocrinology
- Andrology
- Pharmacology
Background:
- Male hypogonadism, characterized by low testosterone, has classical and age-related forms.
- Increasing age leads to decreased testosterone production in many men, affecting 15-25% over 50.
- Testosterone therapy is indicated for hypogonadism when clinical symptoms are present.
Purpose of the Study:
- To review current and emerging testosterone therapy options for male hypogonadism.
- To compare the efficacy and patient satisfaction of different testosterone delivery systems.
- To highlight new formulations suitable for elderly men and classical hypogonadism.
Main Methods:
- Review of existing literature on testosterone therapy and hypogonadism.
- Analysis of clinical outcomes and side-effect profiles of various testosterone formulations.
- Evaluation of pharmacokinetic data for novel delivery systems.
Main Results:
- Testosterone gel offers efficient delivery with fewer side effects and higher patient satisfaction than patches.
- Intramuscular testosterone undecanoate provides stable serum testosterone levels with infrequent injections (every 3 months).
- Both testosterone gel and intramuscular testosterone undecanoate show promise as preferred future therapies.
Conclusions:
- Newer testosterone formulations, including hydroalcoholic gel and long-acting intramuscular injections, represent significant advancements.
- These novel methods offer improved efficacy, tolerability, and patient convenience for managing hypogonadism.
- Testosterone gel is suitable for elderly men, while intramuscular testosterone undecanoate is ideal for long-term substitution in classical hypogonadism.

Related Concept Videos
 01:20
Disorders of the Male Reproductive System
Prostate disorders are another major concern. These conditions can impair urinary flow due to the prostate's location around the urethra. Symptoms...
 01:30
Electroconvulsive Therapy
 01:28
Drug Therapy
Antianxiety Medications
 00:59
Gene Therapy
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:26
Group Therapy