Management of ruptured aneurysms combined with coexisting aneurysms
Related Experiment Video
Updated: Aug 16, 2026
Microsurgical Creation of Giant Bifurcation Aneurysms in Rabbits for the Evaluation of Endovascular Devices
Published on: September 8, 2023
1Department of Neurosurgery, University Hospital Zurich, Zurich, Switzerland. hgimhof@nch.unizh.ch

In patients suffering from subarachnoid haemorrhage (SAH) and presenting with multiple intracranial aneurysms (MIA) two questions have to be decided on: 1st when is the ideal moment to eliminate the ruptured aneurysm and 2nd when to treat the coexisting aneurysms. In our series we retrospectively analysed 124 SAH-patients presenting with a total of 323 aneurysms. In 57 patients the ruptured aneurysm and all coexisting aneurysms were clipped during the first operation, whereas in 9 patients only some of the coexisting aneurysms (group-A; age in median 55 years) were clipped besides the ruptured one. In 55 patients (group-B; age in median 55 years) the first operation was restricted to clipping the ruptured aneurysm, dealing with the coexisting aneurysm subsequently. Immediately after admission 3 patients passed away. One of the 64 patients waiting (average 60 days, median 14 days) for the subsequent clipping of the not yet secured aneurysms suffered a SAH. Six to 12 months after the initial SAH, 78% of the cases in both groups reached a Glasgow Outcome Score of 4 or 5. Even if in patients with coexisting unruptured intracranial aneurysms the elimination of each and every aneurysm is recommended, the advantages of an unstaged procedure versus the additional strain caused by the prolongation of the procedure, e.g. approach over the midline, 2 or more craniotomies, and the risk of additional ischemic damage to the brain, caused by increased manipulation of cerebral arteries and brain tissue, have to be carefully considered. This is of special importance in dealing with patients in higher Hunt and Hess grades.
In patients suffering from subarachnoid haemorrhage (SAH) and presenting with multiple intracranial aneurysms (MIA) two questions have to be decided on: 1st when is the ideal moment to eliminate the ruptured aneurysm and 2nd when to treat the coexisting aneurysms. In our series we retrospectively analysed 124 SAH-patients presenting with a total of 323 aneurysms. In 57 patients the ruptured aneurysm and all coexisting aneurysms were clipped during the first operation, whereas in 9 patients only some of the coexisting aneurysms (group-A; age in median 55 years) were clipped besides the ruptured one. In 55 patients (group-B; age in median 55 years) the first operation was restricted to clipping the ruptured aneurysm, dealing with the coexisting aneurysm subsequently. Immediately after admission 3 patients passed away. One of the 64 patients waiting (average 60 days, median 14 days) for the subsequent clipping of the not yet secured aneurysms suffered a SAH. Six to 12 months after the initial SAH, 78% of the cases in both groups reached a Glasgow Outcome Score of 4 or 5. Even if in patients with coexisting unruptured intracranial aneurysms the elimination of each and every aneurysm is recommended, the advantages of an unstaged procedure versus the additional strain caused by the prolongation of the procedure, e.g. approach over the midline, 2 or more craniotomies, and the risk of additional ischemic damage to the brain, caused by increased manipulation of cerebral arteries and brain tissue, have to be carefully considered. This is of special importance in dealing with patients in higher Hunt and Hess grades.
Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:30
Aneurysm I: Introduction
 01:25
Aortic Regurgitation III: Medical Management
 01:19
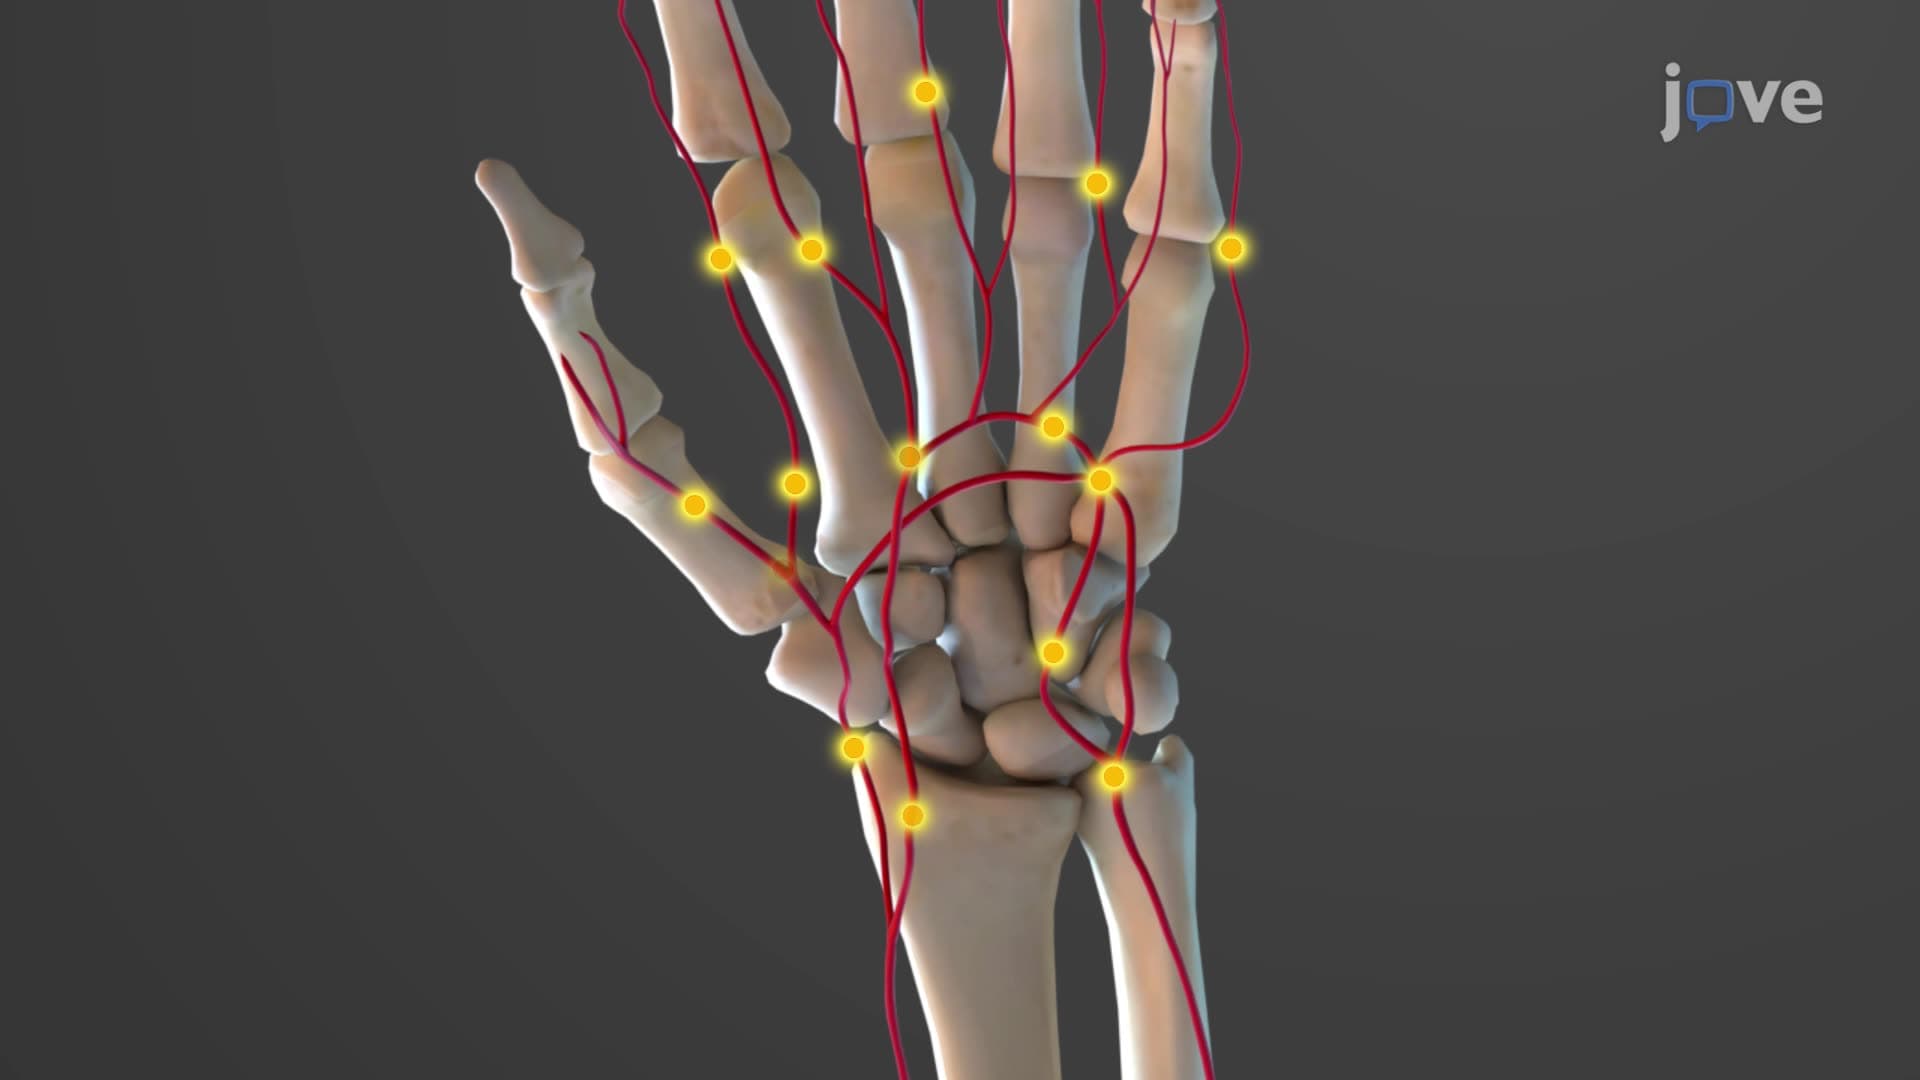
Anastomoses
Anastomoses can be formed at arterial, venous, and lymphatic vessels.
Arterial Anastomosis: These occur between arteries. They are most common in...