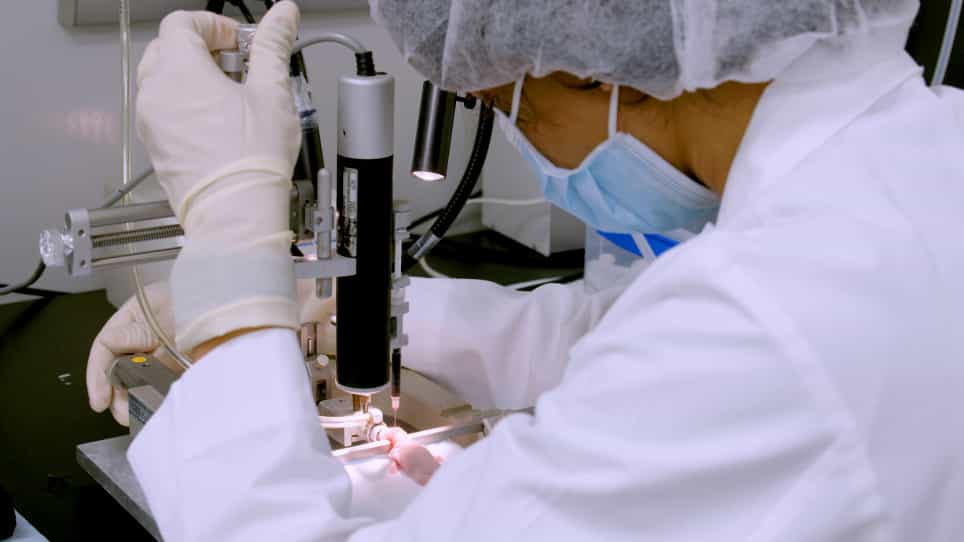
Related Experiment Video
Updated: Aug 16, 2026


Pre-Chiasmatic, Single Injection of Autologous Blood to Induce Experimental Subarachnoid Hemorrhage in a Rat Model
Published on: June 18, 2021
Glucose/insulin infusions in the treatment of subarachnoid haemorrhage: a feasibility study
1Department of Neurosurgery, Kings College Hospital, London, UK.

Hyperglycaemia following subarachnoid haemorrhage (SAH) is well recognized and has been shown to be associated with a worse prognosis. It is currently unclear whether this is a secondary phenomenon reflecting the magnitude of the stress response or whether it contributes directly to the pathophysiological disturbances within the brain. There is significant experimental work on ischaemic stroke to suggest that hyperglycaemia increases infarct volume. The authors propose that controlling blood glucose following SAH is safe and that it might improve outcome. All patients admitted with SAH were treated with insulin to control plasma glucose with a target range of 5.0-7.0 mmol/l. Episodes of hypoglycaemia were recorded. Outcome was assessed at 3 months using the Glasgow Outcome Scale. Fifty-five patients were recruited. 32/3389 (0.94%) of glucose readings fell below 3.5 mmol/l. All were treated with i.v. glucose without evidence of clinical deterioration. Insulin treatment for hyperglycaemia following SAH is feasible and safe. A randomised trial is required to assess any effect on outcome.
Hyperglycaemia following subarachnoid haemorrhage (SAH) is well recognized and has been shown to be associated with a worse prognosis. It is currently unclear whether this is a secondary phenomenon reflecting the magnitude of the stress response or whether it contributes directly to the pathophysiological disturbances within the brain. There is significant experimental work on ischaemic stroke to suggest that hyperglycaemia increases infarct volume. The authors propose that controlling blood glucose following SAH is safe and that it might improve outcome. All patients admitted with SAH were treated with insulin to control plasma glucose with a target range of 5.0-7.0 mmol/l. Episodes of hypoglycaemia were recorded. Outcome was assessed at 3 months using the Glasgow Outcome Scale. Fifty-five patients were recruited. 32/3389 (0.94%) of glucose readings fell below 3.5 mmol/l. All were treated with i.v. glucose without evidence of clinical deterioration. Insulin treatment for hyperglycaemia following SAH is feasible and safe. A randomised trial is required to assess any effect on outcome.