Related Experiment Video
Updated: Aug 13, 2026
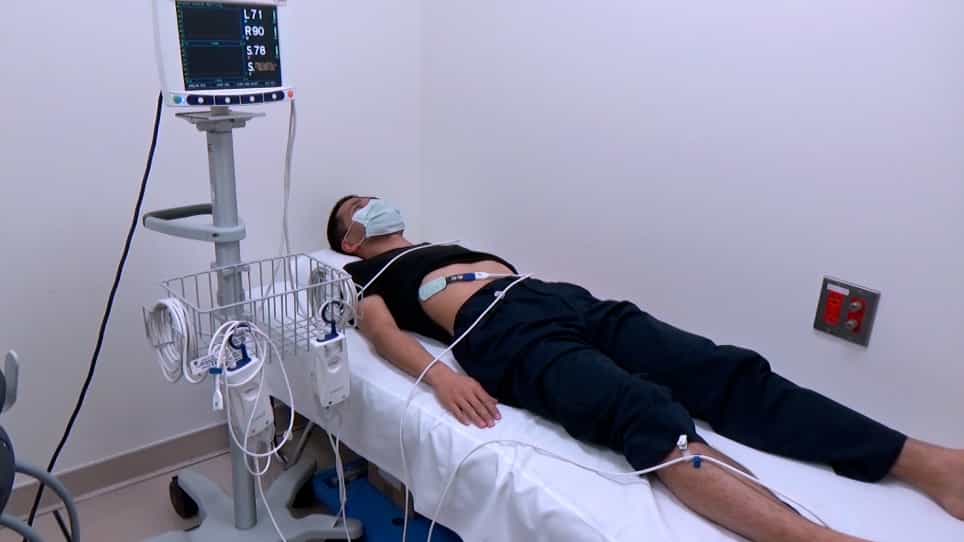

Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
[Monitoring hemodialysis dose with ionic dialisance in on-line hemodiafiltration]
F Maduell1, M J Puchades, V Navarro
1Servicio de Nefrología, Hospital General de Castellón, Castellón.

Until now, with the ionic dialysance measurement, it has been possible to determine hemodialysis dose in each session of hemodialysis (HD) and in the conventional hemofiltration (HDF) but not in the modality of on-line HDF. Recently it is possible with a new biosensor that allows to measure the dose in on-line HDF. The aim of this study was to evaluate the value of this biosensor in different dialysis situations comparing the dialysis dose measured in blood in comparison with the values obtained from the sensor. We have analysed 192 hemodialysis sessions performed in 24 patients, 15 male and 9 female, mean age of 70.2 +/- 12 years, included in on-line HDF. All treatments were done using 4008H (Fresenius) monitor equipped with on-line clearance monitoring (OCM), that measure, with non invasive monitoring, the effective ionic dialysance equivalent to urea clearance. Every patient received eight dialysis sessions: one with dialysate flow (Qd) 500 ml/min, two with HD and Qd 800 ml/min and five with on-line HDF. Other habitual haemodialysis parameters were no changed, dialysis time 200 +/- 63 min (135-300) and blood flow 421 +/- 29 ml/min (350-450). Initial and final ionic dialysance values (K), final Kt, Kt/V measured with OCM using V of Watson, and Kt/V determined in blood pre and postdialysis concentrations of urea (Daugirdas second generation), were measured. The mean of initial K was 251 +/- 21 ml/min and the final K was 234 +/- 24 ml/min. The Kt measured with OCM was 50.6 +/- 17 L, 51.2 +/- 17 in men and 49.7 +/- 16 in women. The V (Watson) was 34.5 +/- 6 L. The Kt/V measured with the Kt of OCM and V was 1,499 +/- 0.54 and Kt/V measured in blood samples was 1,742 +/- 0.58. The correlation between both values was 0.956. The Kt was different according to dialysis modality used: in HD and Qd 500 was 44.7 +/- 15 L, in HD and Qd 800 was 50.7 +/- 17 and in on-line HDF (22.1 +/- 7 L of reposition volume), was 51.8 +/- 17 L. The Kt/V from blood samples also shows variation: in HD and QD 500 was 1.60 +/- 0.55, in HD and Qd 800 was 1,726 +/- 0.56 and in on-line HDF was 1,776 +/- 0.59. In this study has been observed a close correlation between the new biosensor OCM with the measures obtained from the blood samples. For this reason this sensor it is useful in all modalities of dialysis treatment, included on-line HDF. The sensor was able to discriminate the efficacy of different dialysis modalities used in this study.
Until now, with the ionic dialysance measurement, it has been possible to determine hemodialysis dose in each session of hemodialysis (HD) and in the conventional hemofiltration (HDF) but not in the modality of on-line HDF. Recently it is possible with a new biosensor that allows to measure the dose in on-line HDF. The aim of this study was to evaluate the value of this biosensor in different dialysis situations comparing the dialysis dose measured in blood in comparison with the values obtained from the sensor. We have analysed 192 hemodialysis sessions performed in 24 patients, 15 male and 9 female, mean age of 70.2 +/- 12 years, included in on-line HDF. All treatments were done using 4008H (Fresenius) monitor equipped with on-line clearance monitoring (OCM), that measure, with non invasive monitoring, the effective ionic dialysance equivalent to urea clearance. Every patient received eight dialysis sessions: one with dialysate flow (Qd) 500 ml/min, two with HD and Qd 800 ml/min and five with on-line HDF. Other habitual haemodialysis parameters were no changed, dialysis time 200 +/- 63 min (135-300) and blood flow 421 +/- 29 ml/min (350-450). Initial and final ionic dialysance values (K), final Kt, Kt/V measured with OCM using V of Watson, and Kt/V determined in blood pre and postdialysis concentrations of urea (Daugirdas second generation), were measured. The mean of initial K was 251 +/- 21 ml/min and the final K was 234 +/- 24 ml/min. The Kt measured with OCM was 50.6 +/- 17 L, 51.2 +/- 17 in men and 49.7 +/- 16 in women. The V (Watson) was 34.5 +/- 6 L. The Kt/V measured with the Kt of OCM and V was 1,499 +/- 0.54 and Kt/V measured in blood samples was 1,742 +/- 0.58. The correlation between both values was 0.956. The Kt was different according to dialysis modality used: in HD and Qd 500 was 44.7 +/- 15 L, in HD and Qd 800 was 50.7 +/- 17 and in on-line HDF (22.1 +/- 7 L of reposition volume), was 51.8 +/- 17 L. The Kt/V from blood samples also shows variation: in HD and QD 500 was 1.60 +/- 0.55, in HD and Qd 800 was 1,726 +/- 0.56 and in on-line HDF was 1,776 +/- 0.59. In this study has been observed a close correlation between the new biosensor OCM with the measures obtained from the blood samples. For this reason this sensor it is useful in all modalities of dialysis treatment, included on-line HDF. The sensor was able to discriminate the efficacy of different dialysis modalities used in this study.
Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Hemodialysis I: Introduction
 01:15
Dialysis
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:30
Continuous Renal Replacement Therapy
 01:30
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis