Related Experiment Video
Updated: Aug 8, 2026

Robotic-assisted Lateral Pancreaticojejunostomy for Chronic Pancreatitis
Published on: September 5, 2025
Longitudinal pancreaticojejunostomy and selective biliary diversion for chronic pancreatitis in children
Bill Chiu1, John Lopoo, Riccardo A Superina
1Department of Surgery, Children's Memorial Hospital, Chicago, IL 60614, USA.

Insights
Longitudinal pancreaticojejunostomy (LPJ) is a safe and effective surgical option for children with chronic pancreatitis. This procedure minimizes complications and hospitalizations, offering a cost-effective solution for pediatric patients.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Pancreatic Diseases
Background:
- Chronic pancreatitis is uncommon in children and often requires surgical intervention.
- Longitudinal pancreaticojejunostomy (LPJ) is a surgical technique used for treating pediatric chronic pancreatitis.
Purpose of the Study:
- To review the experience and outcomes of treating pediatric chronic pancreatitis using LPJ.
Main Methods:
- Retrospective review of medical records for children who underwent LPJ between 1997 and 2003.
- Data collected included demographics, associated conditions, pre- and post-operative interventions, complications, and hospitalization costs and duration.
Main Results:
- Four pediatric patients (ages 3-16) underwent LPJ for chronic pancreatitis with various associated conditions.
- Post-LPJ, patients experienced no deaths, fistulas, or anastomotic leaks, with a median hospitalization of 8 days and reduced costs.
- All patients resumed normal diets, with no pancreatitis recurrence during 2-6 years of follow-up.
Conclusions:
- Longitudinal pancreaticojejunostomy (LPJ) is a safe and cost-effective treatment for pediatric chronic pancreatitis.
- The procedure is associated with minimal complications and effectively eliminates pancreatitis-related hospitalizations in children.
Background:
Chronic pancreatitis requiring surgery is rare in children. We review our experience in treating pediatric chronic pancreatitis with longitudinal pancreaticojejunostomy (LPJ).
Methods:
Records of children with chronic pancreatitis treated with LPJ between 1997 and 2003 were reviewed. Demographic data, associated conditions, endoscopic interventions, operative procedures, postoperative complications, length and costs of hospitalization, and long-term outcome were recorded.
Results:
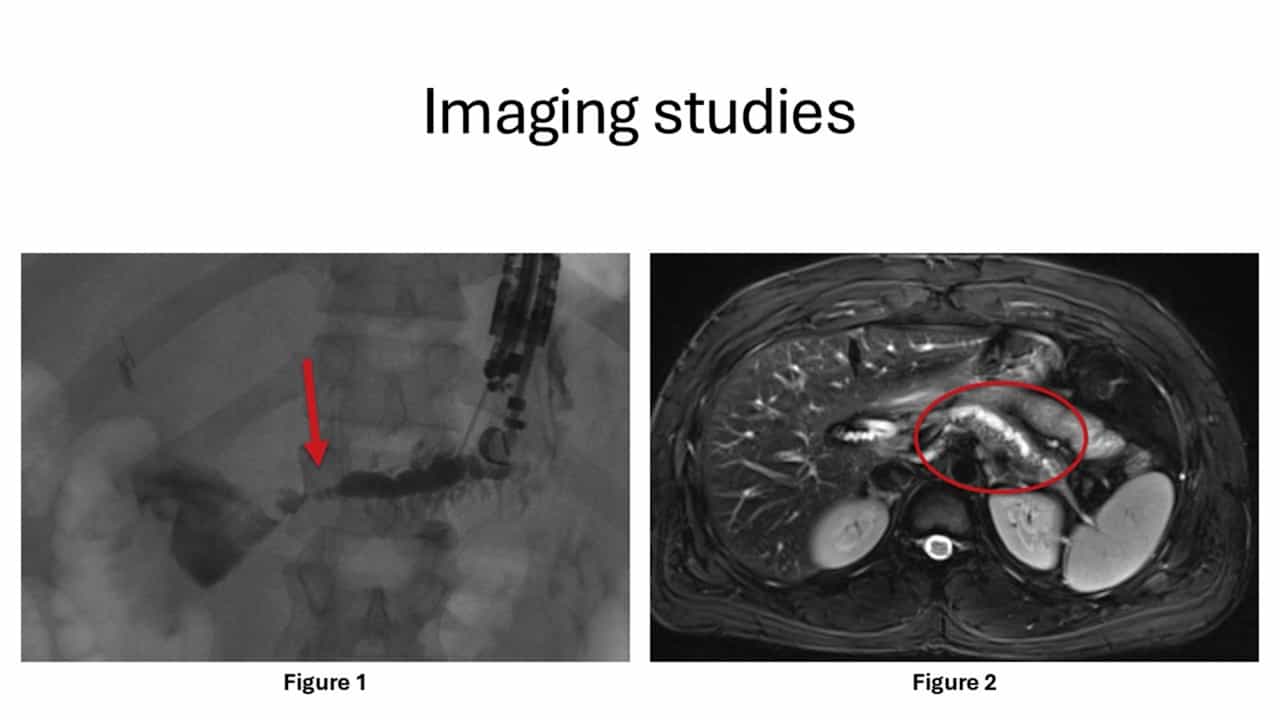
Four patients (one girl), 3 to 16 years old, underwent LPJ. Associated conditions included bile duct obstruction (2), single (1) or multiple (1) pancreatic duct strictures, recurrent familial pancreatitis (1), pseudocyst (1), Down's syndrome (1), and duodenal web (1). Preoperative endoscopic stenting was performed in two patients. All were on restricted diets, one on parenteral nutrition. Pre-LPJ, each child had 3 to 6 admissions for pancreatitis with mean total cost of 39,000 dollars, excluding diet charges. At surgery, two patients required biliary diversion for persistent biliary obstruction in addition to LPJ. Postoperatively, no patient developed fistulas or anastomotic leaks. There were no deaths. The median length of hospitalization post-LPJ was 8 days with mean cost of US37,000 dollars. All patients resumed a normal diet post-LPJ. There were no recurrences of pancreatitis with follow-ups between 2 and 6 years.
Conclusion:
Longitudinal pancreaticojejunostomy is safe and cost-effective for treating pediatric chronic pancreatitis. It has minimal complications and frees patients from pancreatitis-related hospitalizations.

