Related Experiment Video
Updated: Aug 12, 2026

Murine Prostate Micro-dissection and Surgical Castration
Published on: May 11, 2016
Androgen ablation and blockade in the treatment of benign prostatic hyperplasia
1University of Texas Southwestern Medical Center, Dallas.

Abstract:
Antiandrogen therapy appears to produce a 30 to 40 per cent decrease in the volume of the hyperplastic prostate after 3 to 6 months of therapy (Table 5). Longer treatment may result in further prostatic regression, although this remains to be seen. Biopsy studies suggest that epithelial regression occurs to a much more significant degree than does stromal regression, but this finding may simply reflect the relatively longer turnover of the stromal cell population. The significant placebo effect of oral medication in patients with BPH makes interpretation of clinical symptomatology and uro-flow data difficult. Analysis of symptom improvement is further complicated by the relatively slow improvement of patients on antiandrogen therapy, in contrast to surgery, in which relief is immediate. In addition to limited stromal involution and inadequate treatment duration, other biologic factors may limit the clinical efficacy of antiandrogen therapy. Most importantly, prostatic involution may not necessarily decrease urethral resistance. In addition, obstruction-induced detrusor dysfunction may persist after relief of outflow obstruction in some patients, as it does after surgery. Incomplete antiandrogen action of the compounds, as well as compliance issues, may likewise limit efficacy. Although there are no data to suggest that the 5 alpha-reductase inhibitor finasteride will be more effective than other antiandrogen compounds in the treatment of BPH, preliminary studies suggest that it has less toxicity. If long-term studies validate a modest but significant clinical response rate and preservation of sexual function, then finasteride therapy may well be acceptable to a subgroup of men presenting with the symptoms of BPH.(ABSTRACT TRUNCATED AT 250 WORDS)


Related Concept Videos
 01:31
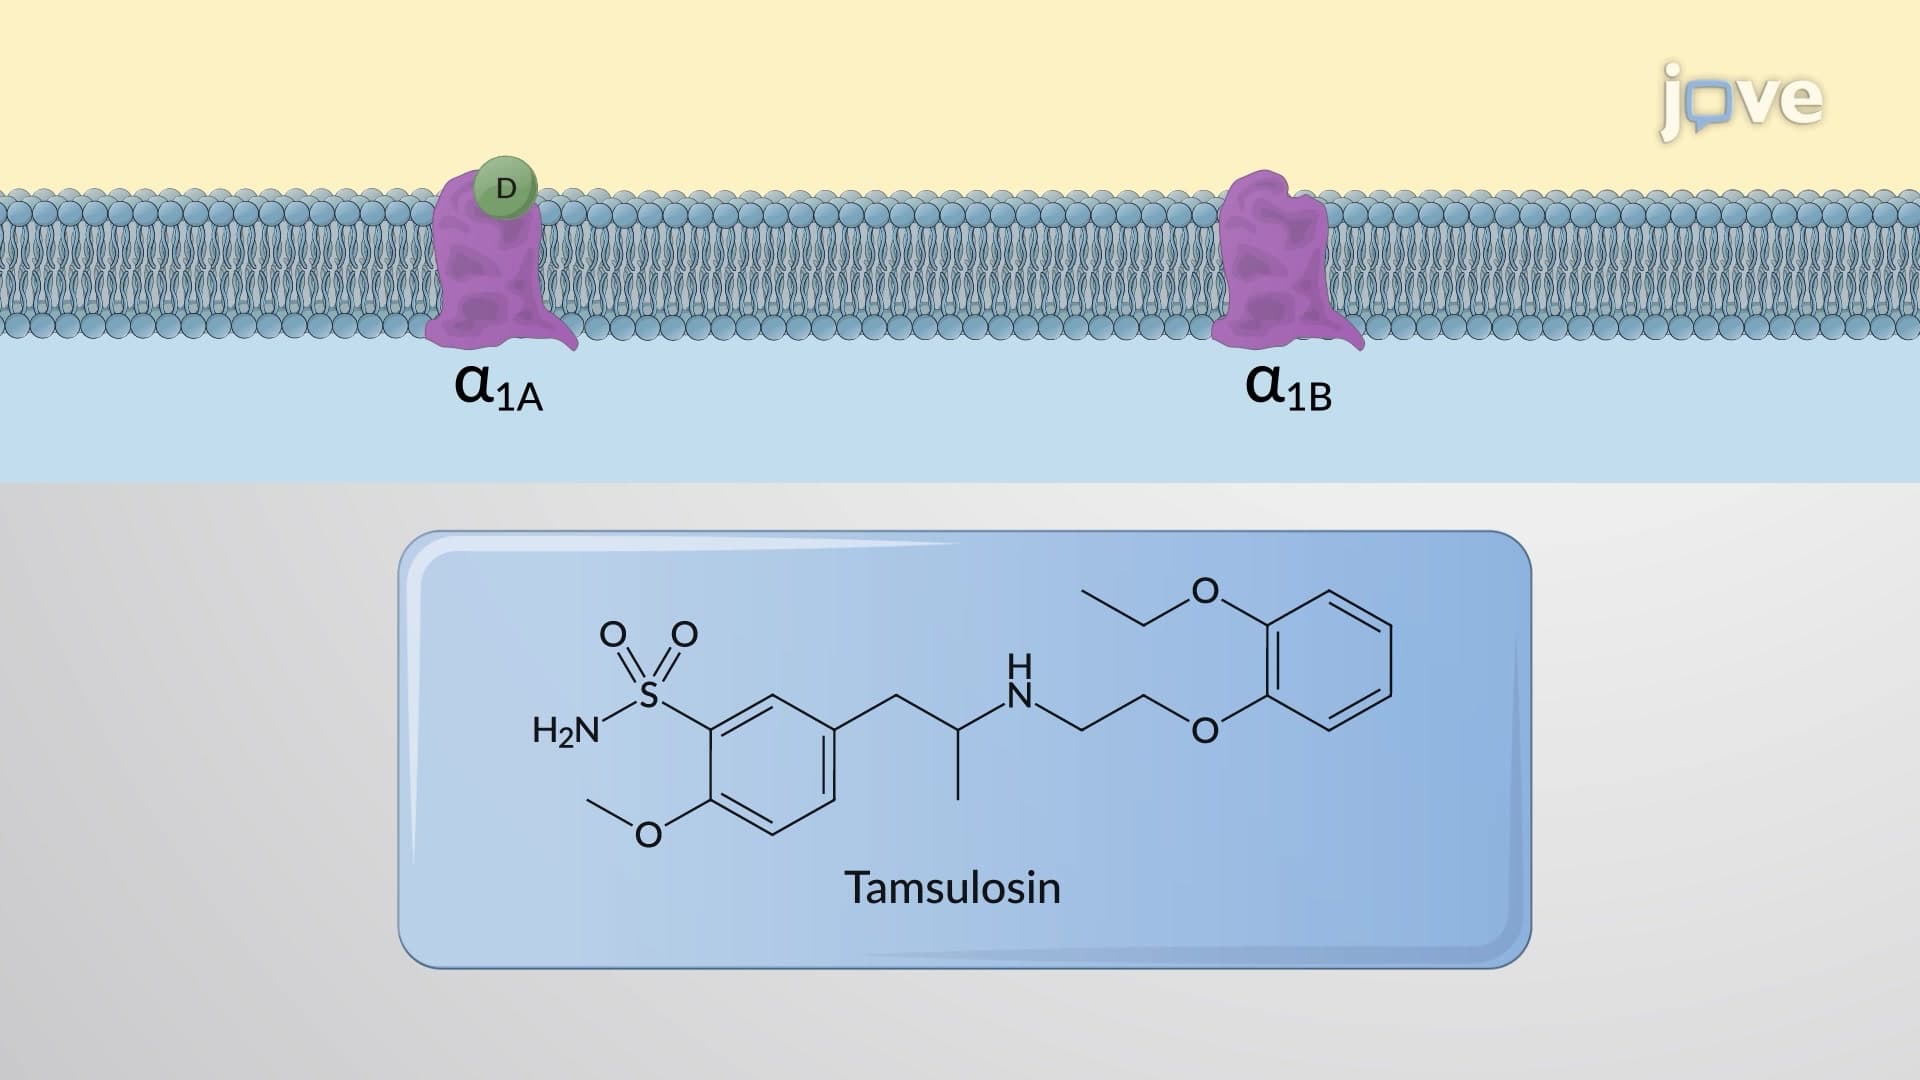
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:17
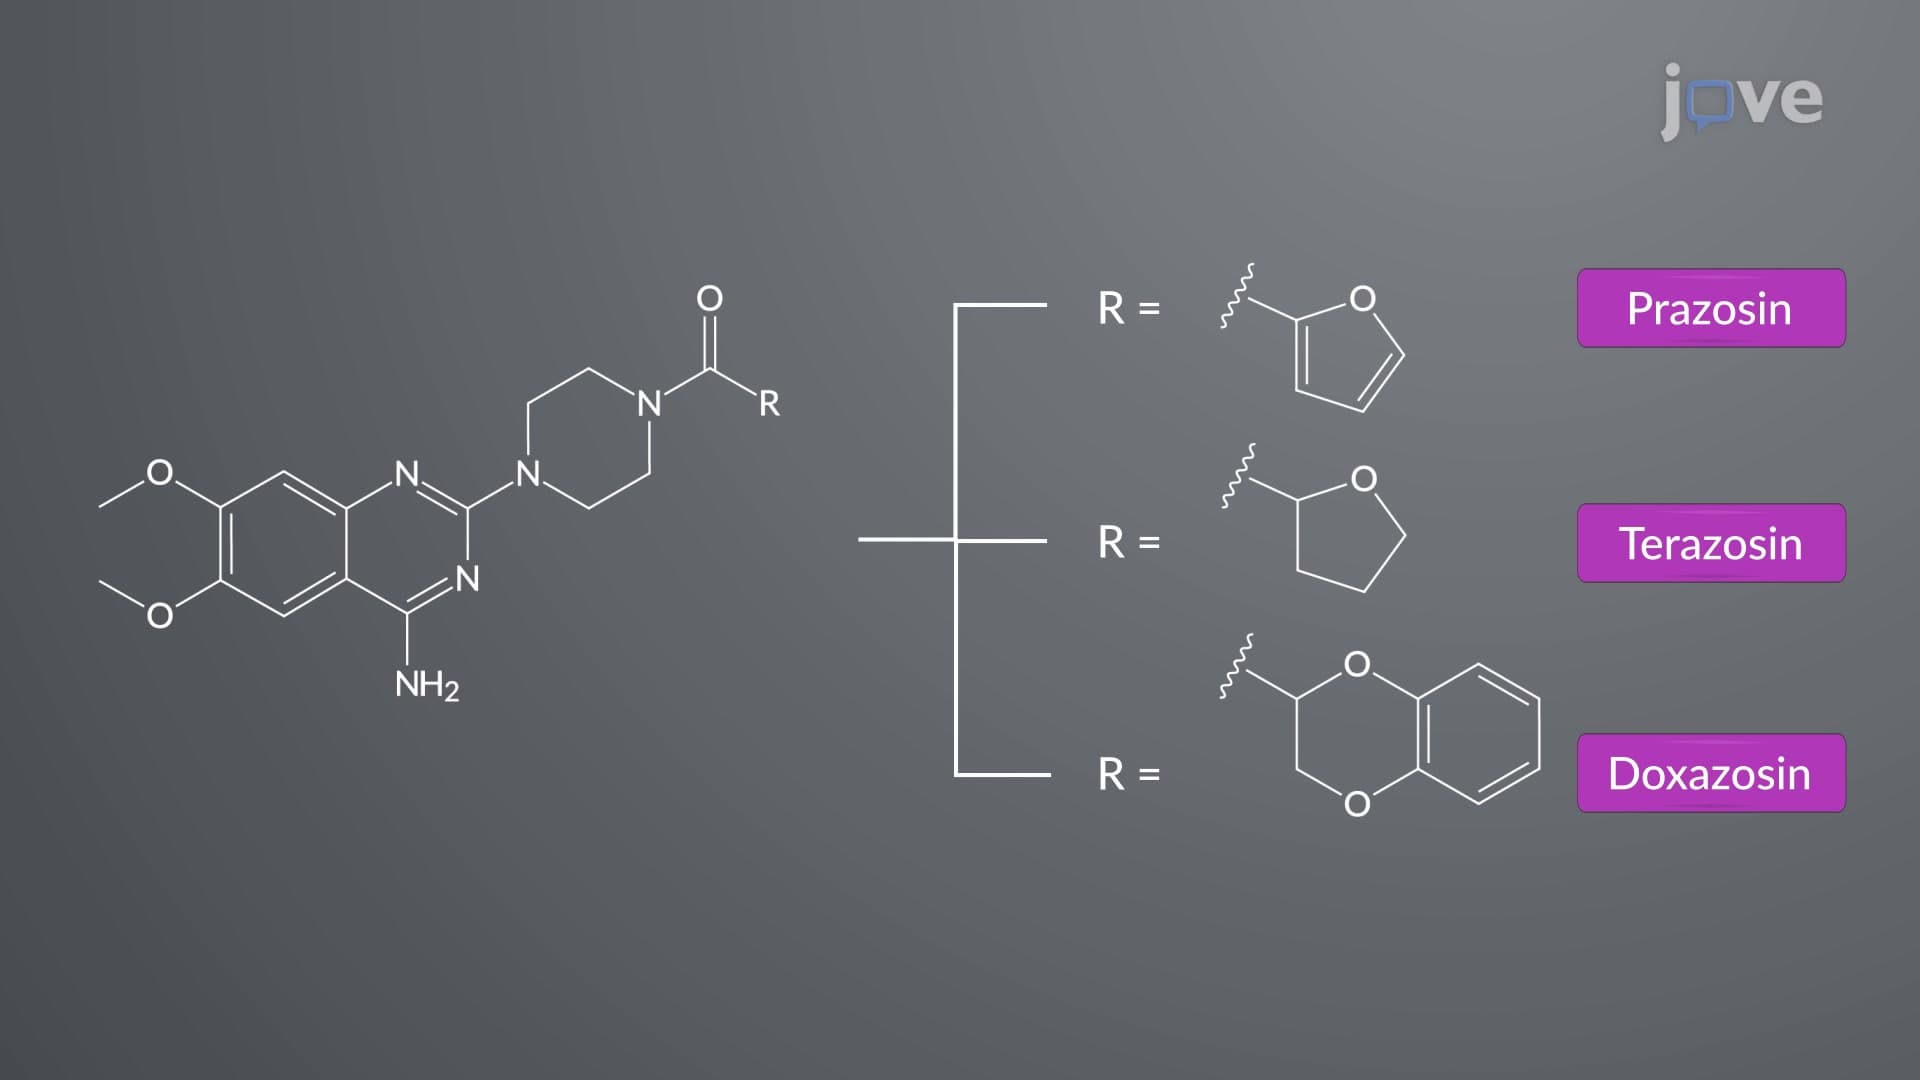
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme (ECE). Of...
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...