Related Experiment Videos
[Fever without a focus in children 0-36 months of age]
Svetlana Kuzmanović1, Nevenka Roncević, Aleksandra Stojadinović
1Institut za zdravstvenu zastitu dece i omladine, Novi Sad. cecak@neobee.net

Insights
Fever without a focus in young children requires careful evaluation for serious bacterial infections. Guidelines help manage febrile infants and children, distinguishing low-risk cases from those needing hospitalization and antibiotics.
Area of Science:
- Pediatrics
- Infectious Diseases
- Emergency Medicine
Context:
- Approximately 20% of childhood fevers lack an apparent cause, posing a diagnostic challenge.
- A subset of these febrile children may have serious bacterial infections, necessitating prompt and accurate management.
- Fever without a focus is defined as a rectal temperature of 38°C or higher in children younger than 36 months without localizing signs.
Purpose:
- To provide practical recommendations for the medical care of febrile children aged 0-36 months.
- To guide clinicians in assessing the risk of serious bacterial infection based on age, clinical presentation, and specific criteria.
- To outline diagnostic and therapeutic strategies for managing fever without a focus in pediatric patients.
Summary:
- Febrile neonates require immediate hospitalization, blood, urine, and spinal fluid cultures, and empirical antibiotic therapy.
- Febrile infants (28-90 days) should be assessed using the Rochester Criteria to identify those at low risk for serious bacterial infections.
- Febrile children aged 3-36 months who appear well and have temperatures below 39°C may be closely monitored without immediate laboratory tests or antibiotics, with re-examination in 2-3 days. Those with higher temperatures or concerning clinical signs require further evaluation and potential treatment.
Impact:
- Facilitates timely diagnosis and appropriate treatment of serious bacterial infections in febrile infants and children.
- Reduces unnecessary laboratory testing and antibiotic use in low-risk febrile children, optimizing resource utilization.
- Improves clinical outcomes for febrile children by providing evidence-based guidelines for management, particularly for fever without a focus.
Introduction:
About 20% of fevers in childhood have no apparent cause. A small, but significant number of these children may have a seroius bacterial infection. Fever without a focus of infection is an acute febrile illness with rectal temperature of 38 degrees C or higher in children younger than 36 months, without localizing signs or symptoms.
Practice Guidelines For Medical Care:
In this article, practical recommendations for medical care of febrile children 0-36 months of age are given, bearing in mind children's age, clinical presentation (toxic manifestations) and risk for serious bacterial infection (sepsis, meningitis, pneumonia, urinary tract infection...). Toxic appearance is a clinical presentation characterized by lethargy, poor perfusion, marked hypo/hyperventilation and cyanosis. All febrile children under 36 months of age, who are appearing toxic, require hospitalization, evaluation for sepsis and administration of empiricial antibiotic therapy. All febrile neonates, however, must be hospitalized; cultures of blood, urine and spinal fluid should be taken and empirical antibiotic therapy administered immediately. Febrile infants, 28 to 90 days of age, need to be evaluated in order to determine whether they are in the low-risk group for serious bacterial infections (Rochester Criteria). Yale Observation Scale is recommended to assess febrile children aged 3-36 months, and the risk of occult bacteriemia. Febrile children, 3-36 months of age who appear well, with temperature of less than 39 degrees C without focus, should be closely followed up without laboratory tests and antibiotics and 2-3 days later reexamined. In febrile children, 3-36 months old, with temperature of 39 degrees C and above, without toxic manifestations, blood culture should be taken and ceftriaxone 50 mg/kg/in a single dose should be given, if leukocyte count is 15000/mm3 or absolute neutrophil count is over 10.000/mm3.
Related Concept Videos
 01:25
Increased Body Temperature
 01:26
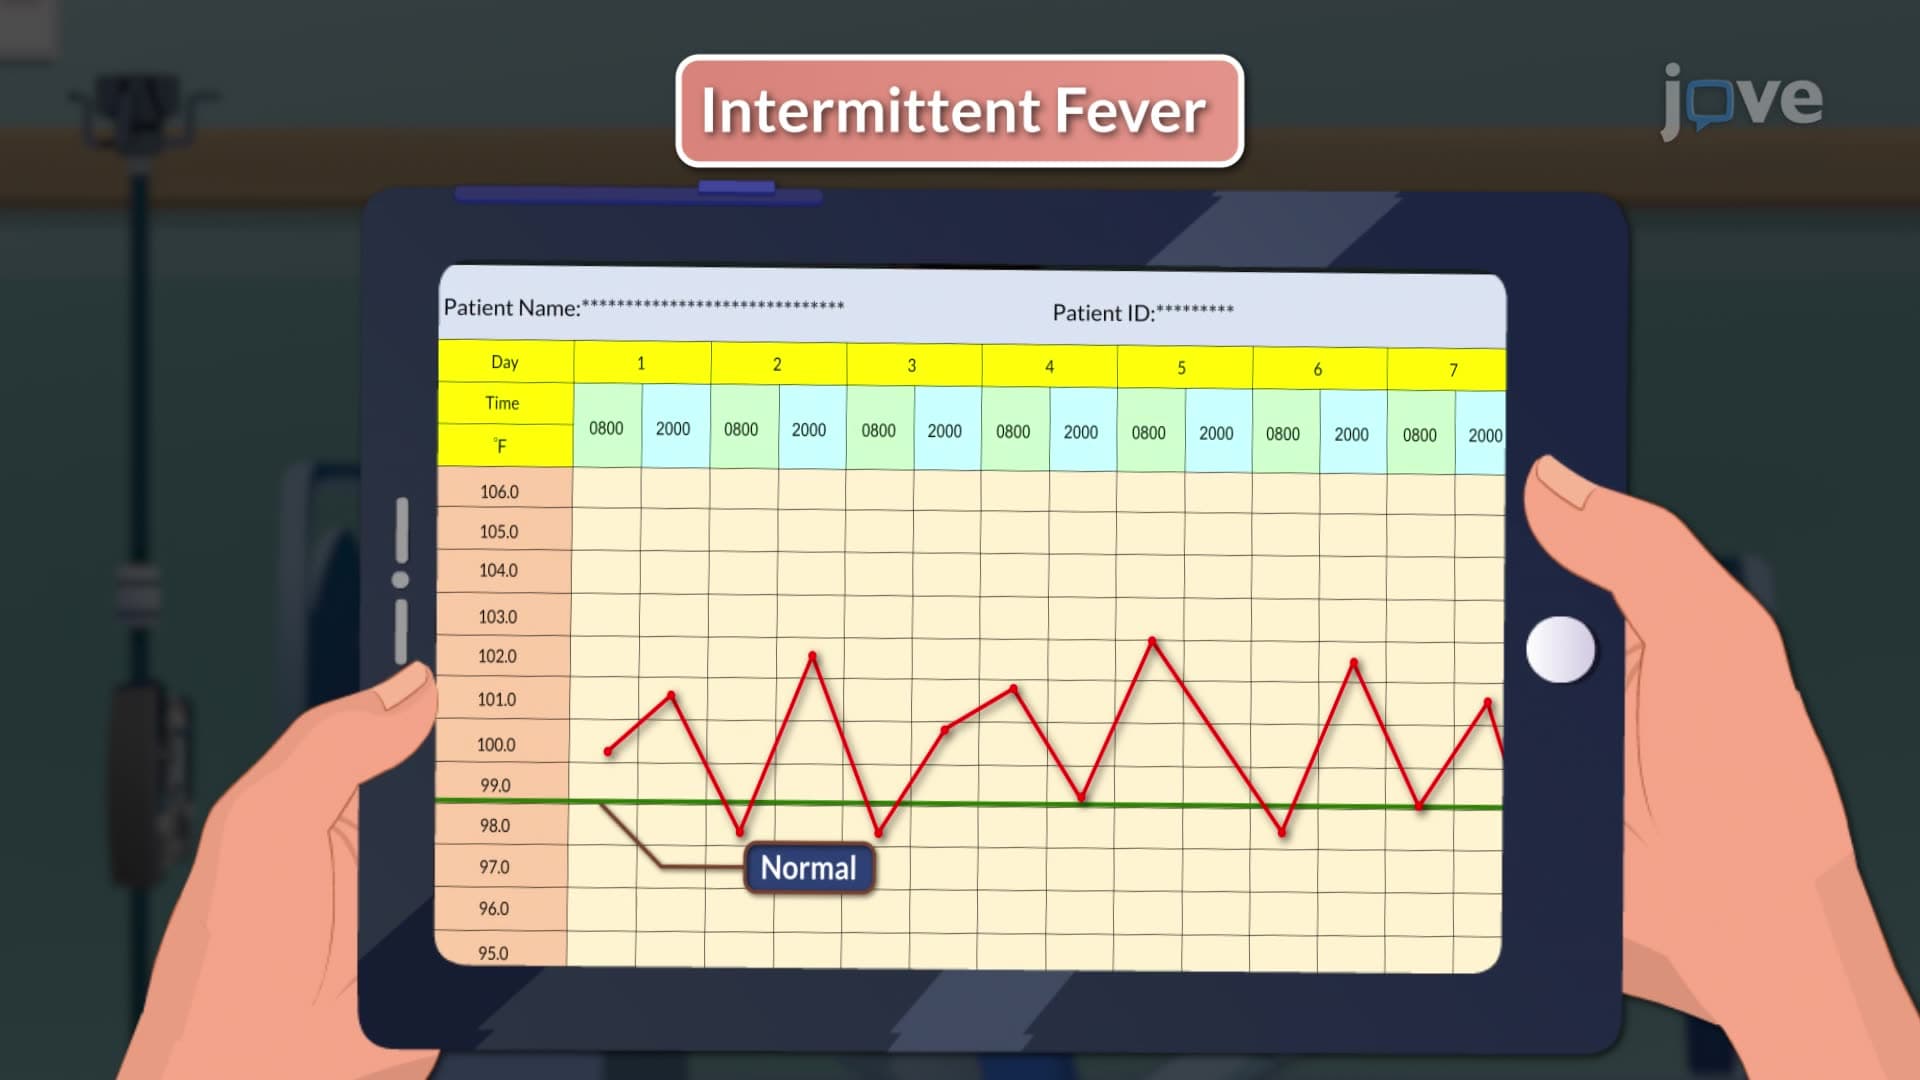
Patterns of Fever
 01:25
Types of Fever
Here are the different types of fever:
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:26
Rocky Mountain Spotted Fever
 01:18
Viral Meningitis