Related Experiment Video
Updated: Jul 7, 2026


Electrocardiogram Recordings in Anesthetized Mice using Lead II
Published on: June 20, 2020
Effects of presentation and electrocardiogram on time to treatment of hyperkalemia
Kalev Freeman1, James A Feldman, Patricia Mitchell
1Department of Surgery, University of Vermont College of Medicine, Burlington, VT, USA. kalev.freeman@uvm.edu

Insights
Severe hyperkalemia recognition is difficult, leading to delayed treatment initiation in emergency departments. Even with treatment, critical hyperkalemia poses risks, highlighting diagnostic and therapeutic challenges.
Area of Science:
- Emergency Medicine
- Cardiology
- Nephrology
Background:
- Hyperkalemia, characterized by elevated serum potassium levels (>6.0 mmol/L), is a critical condition that can lead to life-threatening cardiac arrhythmias.
- Prompt recognition and treatment are essential to prevent adverse outcomes, yet challenges in diagnosis and timely intervention persist in emergency settings.
Purpose of the Study:
- To evaluate the time to treatment for emergency department (ED) patients diagnosed with critical hyperkalemia.
- To identify clinical characteristics and electrocardiographic (ECG) abnormalities associated with the timing of hyperkalemia treatment.
Main Methods:
- A retrospective chart review was conducted on ED patients with laboratory-confirmed hyperkalemia (potassium > 6.0 mmol/L).
- Patients in cardiac arrest or undergoing dialysis were excluded. Data on treatment initiation, clinical factors, and ECG findings were collected.
Main Results:
- The median time from triage to treatment initiation for hyperkalemia was 117 minutes.
- Despite treatment in 96% of cases, 2 patients died from arrhythmias. Abnormal ECGs (83%) and hypotension did not consistently predict early treatment.
- Delays were noted in patients not transported by ambulance, those with syncope, or a history of hypertension.
Conclusions:
- Recognizing patients with severe hyperkalemia in the ED is challenging.
- The initiation of appropriate and timely therapy for hyperkalemia is frequently delayed, underscoring the need for improved diagnostic and treatment protocols.
Objectives:
To assess the time to treatment for emergency department (ED) patients with critical hyperkalemia and to determine whether the timing of treatment was associated with clinical characteristics or electrocardiographic abnormalities.
Methods:
The authors performed a retrospective chart review of ED patients with the laboratory diagnosis of hyperkalemia (potassium level > 6.0 mmol/L). Patients presenting in cardiac arrest or who were referred for hyperkalemia or dialysis were excluded. Patient charts were reviewed to find whether patients received specific treatment for hyperkalemia and, if so, what clinical attributes were associated with the time to initiation of treatment.
Results:
Of 175 ED visits that occurred over a 1-year time period, 168 (96%) received specific treatment for hyperkalemia. The median time from triage to initiation of treatment was 117 minutes (interquartile range [IQR] = 59 to 196 minutes). The 7 cases in which hyperkalemia was not treated include 4 cases in which the patient was discharged home, with a missed diagnosis of hyperkalemia. Despite initiation of specific therapy for hyperkalemia in 168 cases, 2 patients died of cardiac arrhythmias. Among the patients who received treatment, 15% had a documented systolic blood pressure (sBP) < 90 mmHg, and 30% of treated patients were admitted to intensive care units. The median potassium value was 6.5 mmol/L (IQR = 6.3 to 7.1 mmol/L). The predominant complaints were dyspnea (20%) and weakness (19%). Thirty-six percent of patients were taking angiotensin-converting enzyme (ACE) inhibitors. Initial electrocardiograms (ECGs) were abnormal in 83% of patient visits, including 24% of ECGs with nonspecific ST abnormalities. Findings of peaked T-wave morphology (34%), first-degree atrioventricular block (17%), and interventricular conduction delay (12%) did not lead to early treatment. Vital sign abnormalities, including hypotension (sBP < 90 mmHg), were not associated with early treatment. The chief complaint of "unresponsive" was most likely to lead to early treatment; treatment delays occurred in patients not transported by ambulance, those with a chief complaint of syncope and those with a history of hypertension.
Conclusions:
Recognition of patients with severe hyperkalemia is challenging, and the initiation of appropriate therapy for this disorder is frequently delayed.
More Related Videos


Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:30
Cardiac Action Potential
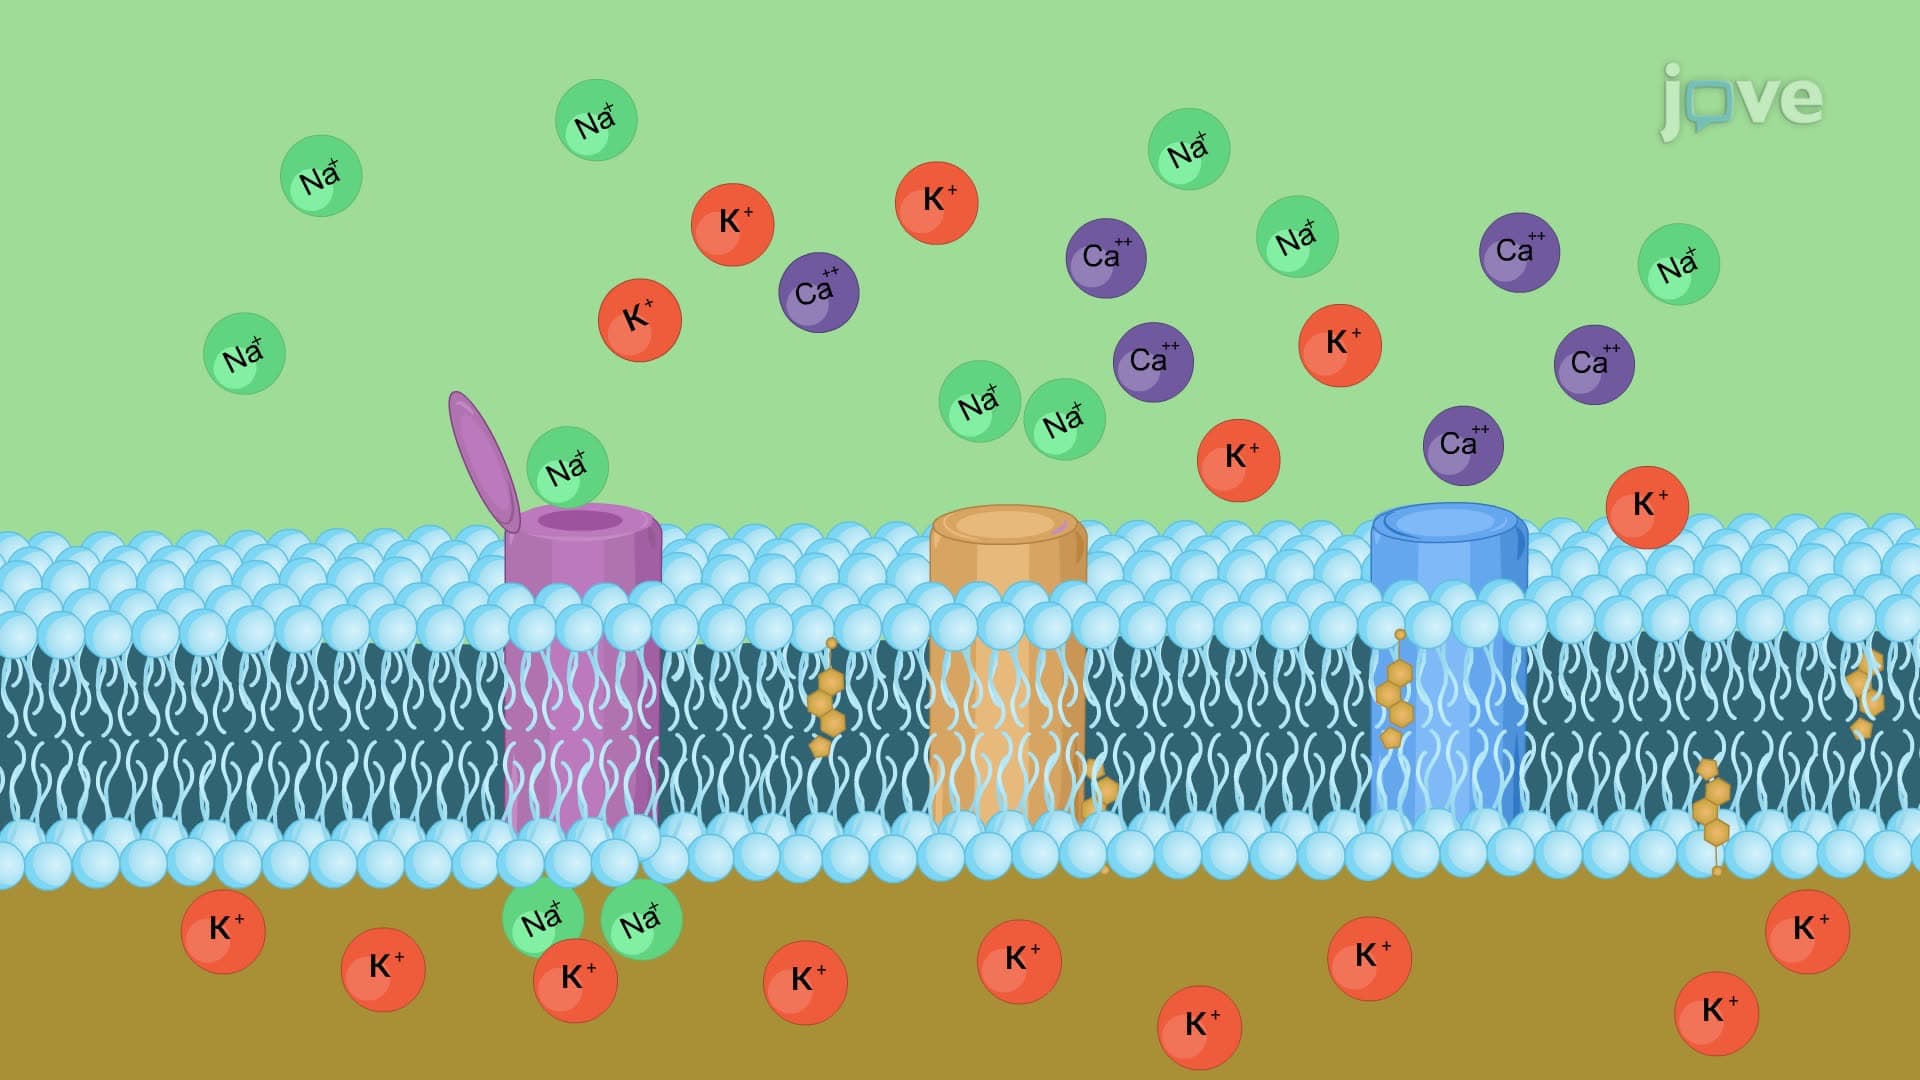
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:29
Electrocardiogram
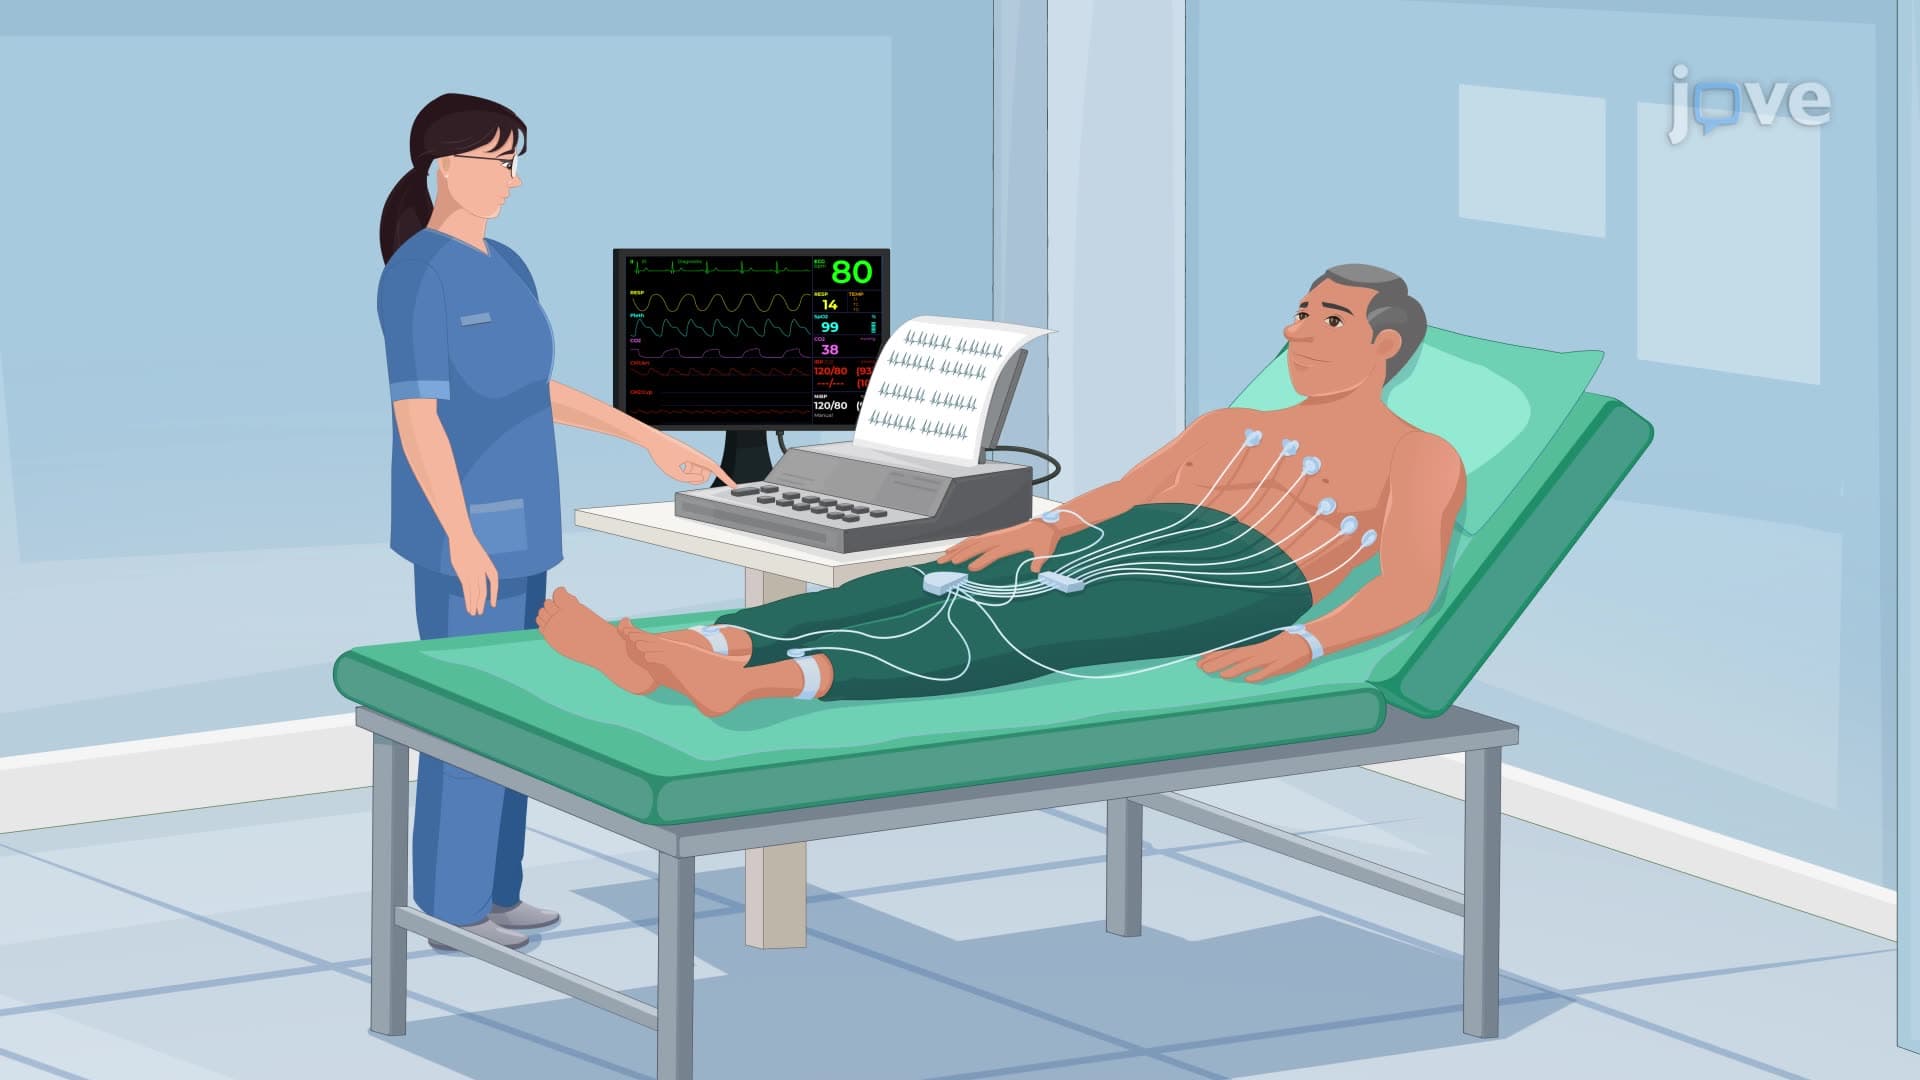
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers