Related Experiment Video
Updated: Jul 1, 2026


Videomorphometric Analysis of Hypoxic Pulmonary Vasoconstriction of Intra-pulmonary Arteries Using Murine Precision Cut Lung Slices
Published on: January 14, 2014
Ventilatory effects of low-dose paraoxon result from central muscarinic effects
Pascal Houze1, Laetita Pronzola, Maya Kayouka
1Toxicology Laboratory, Faculty of Pharmacy, 75006 Paris, France.

Abstract:
Paraoxon induces respiratory toxicity. Atropine completely reversed parathion- and paraoxon-induced respiratory toxicity. The aim of this study was to assess the peripheral or central origin of ventilatory effects of low-dose paraoxon. Male Sprague-Dawley rats were given paraoxon 0.215 mg/kg subcutaneously and treated with either atropine (10 mg/kg sc) or ascending doses of methylatropine of 5.42 (equimolar to that of atropine), 54.2, and 542 mg/kg administered subcutaneously 30 min after paraoxon. Ventilation at rest was assessed using whole-body plethysmography and rat temperature using infra-red telemetry. Results are expressed as mean+/-SE. Statistical analysis used two-way ANOVA for repeated measurements. Paraoxon induced a significant decrease in temperature 30 min after injection lasting the 90 min of the study period. This effect was partially corrected by atropine, but not by methylatropine whatever the dose. Paraoxon induced a decrease in respiratory rate resulting from an increase in expiratory time associated with an increase in tidal volume. Atropine completely reversed the ventilatory effects of low-dose paraoxon while the equimolar dose of methylatropine had no significant effects. The 54.2 and 542 mg/kg doses of methylatropine had no significant effects. Atropine crosses the blood-brain barrier and reverses peripheral and central muscarinic effects. In contrast, methylatropine does not cross the blood-brain barrier. Atropine completely reversed the ventilatory effects of low-dose paraoxon, while methylatropine had no significant effects at doses up to 100-fold the equimolar dose of atropine. We conclude that the ventilatory effects of low-dose paraoxon are mediated by disrupted muscarinic signaling in the central nervous system.
Insights
Low-dose paraoxon causes respiratory toxicity by affecting the central nervous system. Atropine, which crosses the blood-brain barrier, reversed these effects, indicating a central origin for paraoxon
Area of Science:
- Toxicology
- Neuroscience
- Respiratory Physiology
Background:
- Paraoxon is an organophosphate pesticide known to induce respiratory toxicity.
- Atropine effectively reverses parathion and paraoxon-induced respiratory toxicity.
- The precise origin (peripheral or central) of paraoxon's ventilatory effects requires further investigation.
Purpose of the Study:
- To determine whether the ventilatory effects of low-dose paraoxon originate in the peripheral or central nervous system.
- To investigate the role of muscarinic signaling in paraoxon-induced respiratory toxicity.
Main Methods:
- Male Sprague-Dawley rats were administered low-dose paraoxon (0.215 mg/kg).
- Animals were treated with atropine (10 mg/kg) or escalating doses of methylatropine (5.42 to 542 mg/kg).
- Ventilation was assessed using whole-body plethysmography, and body temperature was monitored via infra-red telemetry.
Main Results:
- Paraoxon induced hypothermia, partially reversed by atropine but not methylatropine.
- Paraoxon decreased respiratory rate by increasing expiratory time and tidal volume.
- Atropine completely reversed paraoxon's ventilatory effects, while methylatropine showed no significant effect even at high doses.
Conclusions:
- The ventilatory effects of low-dose paraoxon are primarily mediated by the central nervous system.
- Disrupted muscarinic signaling within the central nervous system is the likely mechanism of paraoxon-induced respiratory toxicity.
- Atropine's ability to reverse these effects highlights its efficacy in counteracting central neurotoxic effects of organophosphates.
More Related Videos
 07:15
Preoxygenation Techniques for Tracheal Intubation in Critically Ill Adults Utilizing Oxygen Mask and Noninvasive Ventilation
Published on: December 5, 2025
 08:35
Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Related Concept Videos
 00:59
Direct-Acting Cholinergic Agonists: Pharmacological Actions
 01:28
Cholinergic Antagonists: Pharmacological Actions
Gastrointestinal Effects: Antimuscarinics reduce gut contractions, increase gastric emptying, and slow intestinal transit. They partly inhibit gastric acid secretion...
 01:31
Chemical Factors Affecting Respiration Centers
CO2 has a potent influence on respiration and is strictly regulated. Under...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
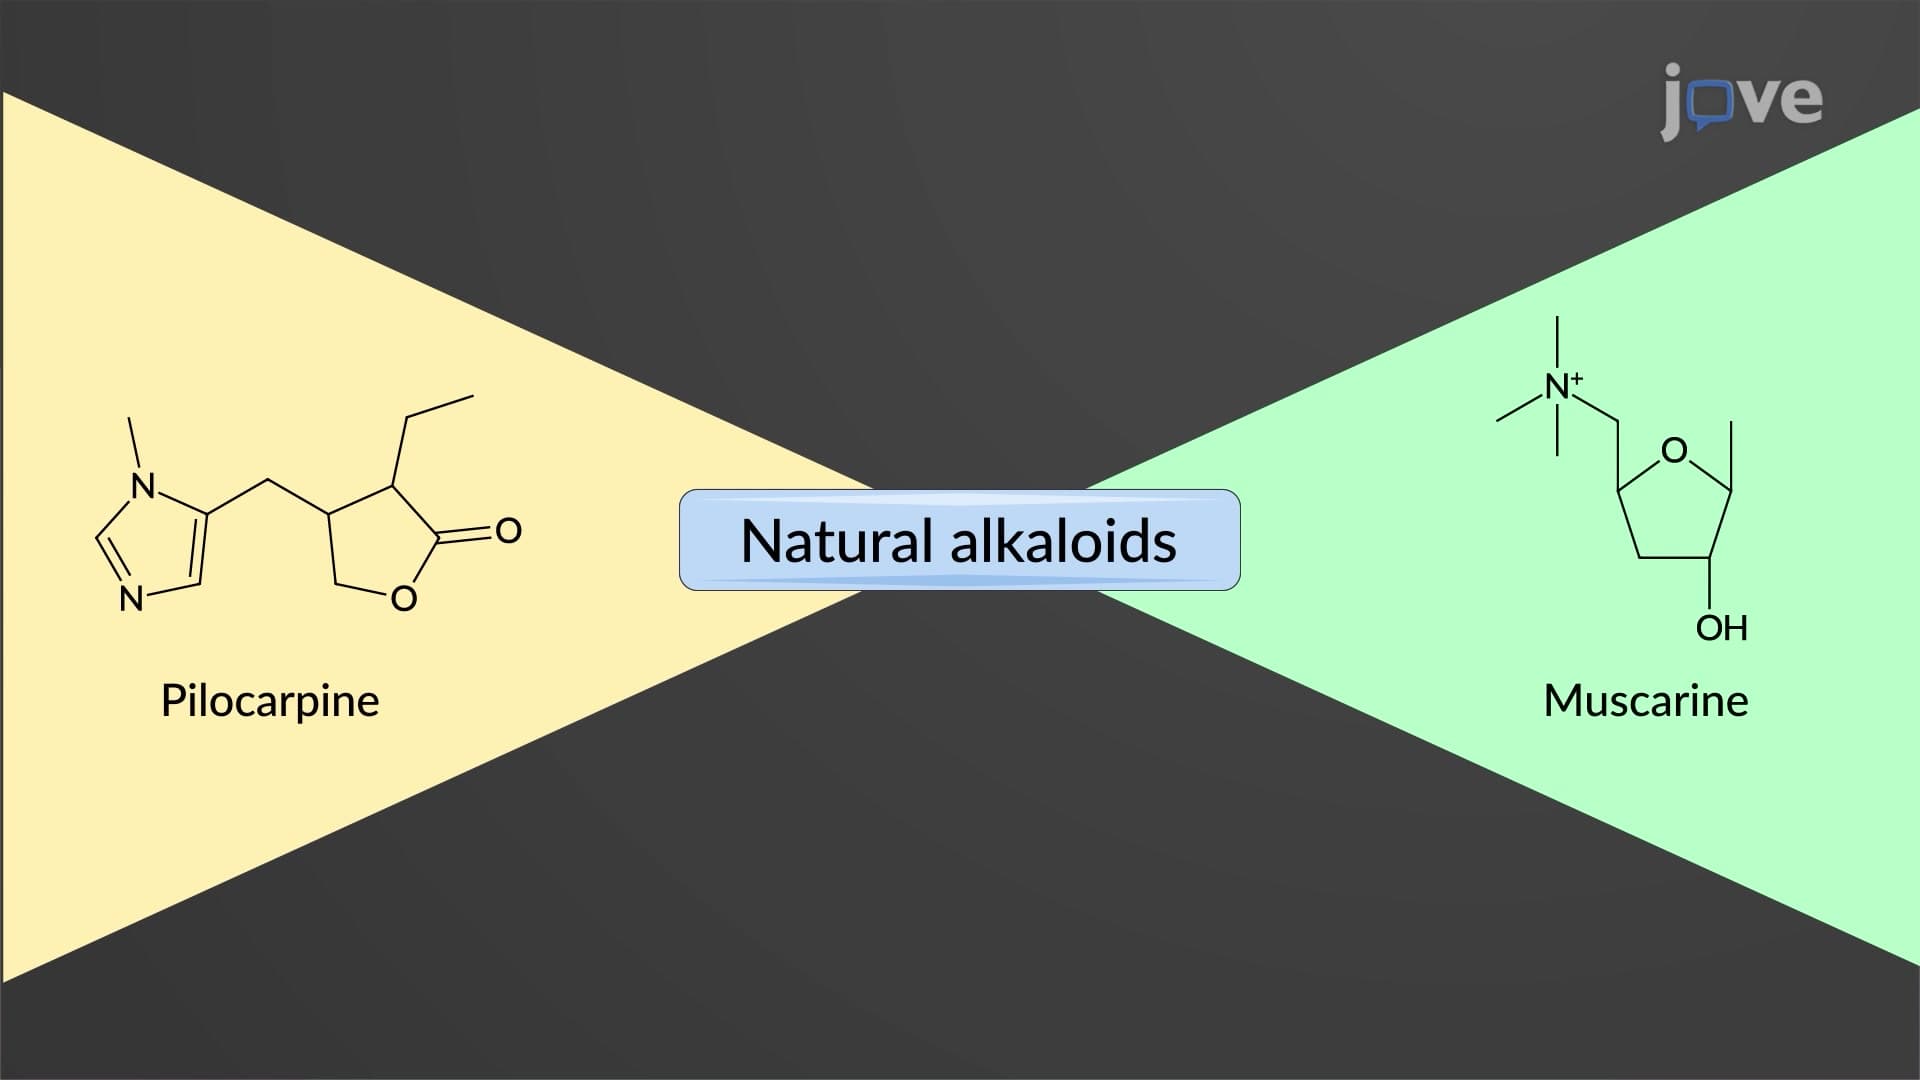 01:22
Direct-Acting Cholinergic Agonists: Chemistry and Structure-Activity Relationship
The direct-acting...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...