Related Experiment Video
Updated: Jun 30, 2026
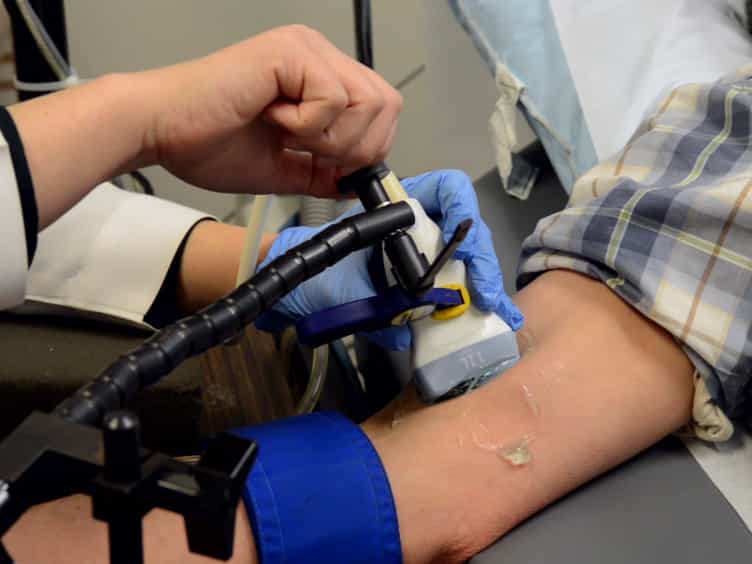

Ultrasound Assessment of Endothelial Function: A Technical Guideline of the Flow-mediated Dilation Test
Published on: April 27, 2016
Circulating oxidized LDL: determinants and association with brachial flow-mediated dilation
Leonard P van der Zwan1, Tom Teerlink, Jacqueline M Dekker
1Metabolic Laboratory, Department of Clinical Chemistry, VU University Medical Center, Amsterdam, The Netherlands.

Insights
The ratio of oxidized LDL to apolipoprotein-B100 is a better indicator of cardiovascular risk than oxidized LDL alone. Adjusting oxidized LDL for LDL particle number may improve its clinical use.
Area of Science:
- Cardiovascular Research
- Biochemistry
- Clinical Medicine
Background:
- Circulating oxidized LDL (oxLDL) is linked to cardiovascular risk, but its independent contribution is unclear due to strong correlations with LDL-cholesterol (LDL-c) and apolipoprotein-B100 (apoB100).
- Disentangling the specific roles of oxLDL, LDL-c, and apoB100 in atherosclerosis is crucial for accurate risk assessment.
Purpose of the Study:
- To investigate the determinants of oxLDL levels.
- To explore the relationship between oxLDL and brachial artery flow-mediated dilation (FMD), a functional measure of atherosclerosis.
- To determine if oxLDL/LDL-c and oxLDL/apoB100 ratios offer greater insight into cardiovascular risk than individual markers.
Main Methods:
- Cross-sectional analysis of 624 participants (aged 50-87) from a population-based cohort study.
- Measurement of plasma oxLDL, LDL-c, apoB100, and brachial artery FMD.
- Statistical analysis to identify determinants of oxLDL and its association with FMD, adjusting for relevant covariates.
Main Results:
- OxLDL strongly correlated with apoB100 (r=0.82) and LDL-c (r=0.67).
- Independent determinants of oxLDL included sex, HDL-cholesterol, and LDL particle size.
- LDL-c and apoB100 levels were not significantly associated with FMD.
- The oxLDL/apoB100 ratio showed a significant negative association with FMD (P=0.017) after adjustments, while the oxLDL/LDL-c ratio showed a weaker association (P=0.062), and oxLDL alone showed no association (P=0.27).
Conclusions:
- The oxLDL/apoB100 ratio, and to a lesser extent the oxLDL/LDL-c ratio, are associated with a functional measure of atherosclerosis (FMD), unlike oxLDL levels alone.
- Correcting oxLDL for LDL particle number (apoB100) may enhance the clinical utility of oxLDL measurements in assessing cardiovascular risk.
Abstract:
Circulating oxidized LDL (oxLDL) levels are strongly correlated to LDL-cholesterol (LDL-c) and apolipoprotein-B100 (apoB100), making it difficult to disentangle their independent contributions to cardiovascular risk. We explored the determinants of oxLDL and the relation between oxLDL and flow-mediated dilation (FMD) of the brachial artery to investigate whether the oxLDL/LDL-c and oxLDL/apoB100 ratios are more informative than the separate variables. FMD of the brachial artery and plasma concentrations of oxLDL, LDL-cholesterol, and apoB100 were measured in 624 men and women (age range 50 to 87 years), participating in a population-based cohort study. OxLDL was strongly correlated with apoB100 (r = 0.82, P < 0.001) and LDL-c (r = 0.67, P < 0.001). Other major independent determinants of oxLDL were sex, HDL-cholesterol, and LDL particle size. LDL-c and apoB100 concentrations were not significantly associated with FMD. After adjustment for age, sex, glucose tolerance status, and Framingham risk score, the oxLDL/apoB100 ratio was negatively related to FMD (P = 0.017). This association was weaker for the oxLDL/ LDL-c ratio (P = 0.062) and absent for oxLDL level (P = 0.27). In contrast to oxLDL, the oxLDL/apoB100 ratio, and to a lesser extent the oxLDL/LDL-c ratio, are related to a functional measure of atherosclerosis. Therefore correction of oxLDL for LDL particle number may improve the clinical usefulness of oxLDL measurement.
More Related Videos
 08:42
Ultrasound Assessment of Endothelial-Dependent Flow-Mediated Vasodilation of the Brachial Artery in Clinical Research
Published on: October 22, 2014
 06:04
Pulse-Wave Velocity, Flow-Mediated Dilation, and Carotid Intima-Media Thickness to Assess Cardiovascular Risk in Population with Metabolic Syndrome
Published on: September 27, 2024
Related Concept Videos
 01:30
Coronary Artery Disease I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology
 01:30
Atherosclerosis I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:30
Peripheral Artery Disease I: Introduction
 01:26
Atherosclerosis III: Management