Related Experiment Video
Updated: Jun 21, 2026
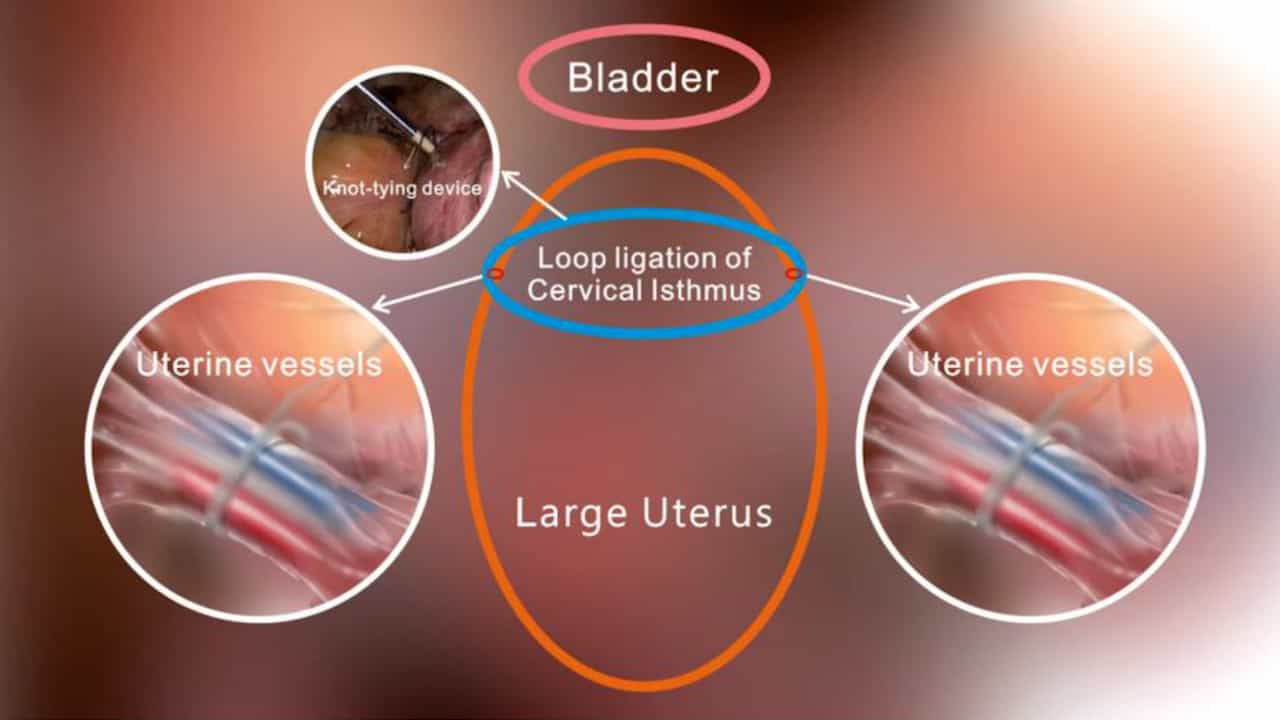

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Surgical approach to hysterectomy for benign gynaecological disease
Theodoor E Nieboer1, Neil Johnson, Anne Lethaby
1Obstetrics and Gynaecology, Radboud University Nijmegen Medical Centre, Johan de Wittlaan, Arnhem, Netherlands, 80 6828 WJ.

Insights
Vaginal hysterectomy (VH) offers faster recovery and shorter hospital stays compared to abdominal hysterectomy (AH). Laparoscopic hysterectomy (LH) also shows benefits over AH, but VH is preferred when possible for benign gynecological conditions.
Area of Science:
- Gynaecology
- Surgical Oncology
- Evidence-Based Medicine
Background:
- Hysterectomy is a common surgical procedure for benign gynecological conditions.
- Abdominal hysterectomy (AH), vaginal hysterectomy (VH), and laparoscopic hysterectomy (LH) are the primary surgical approaches.
- Laparoscopic hysterectomy encompasses several techniques based on the extent of laparoscopic involvement.
Purpose of the Study:
- To determine the most beneficial and least harmful surgical approach for hysterectomy in women with benign gynecological conditions.
- To compare the outcomes of abdominal, vaginal, and laparoscopic hysterectomy.
Main Methods:
- Systematic review and meta-analysis of randomized controlled trials (RCTs).
- Searched multiple databases including Cochrane, CENTRAL, MEDLINE, and EMBASE up to August 2008.
- Included 34 RCTs involving 4495 women comparing different hysterectomy approaches.
Main Results:
- Vaginal hysterectomy (VH) demonstrated faster return to normal activities, shorter hospital stays, and fewer infections compared to abdominal hysterectomy (AH).
- Laparoscopic hysterectomy (LH) showed advantages over AH in recovery time, blood loss, and wound infections, but with increased urinary tract injuries and longer operation times.
- Laparoscopic assisted vaginal hysterectomy (LAVH) was associated with fewer infections and shorter operation times than total laparoscopic hysterectomy (TLH).
Conclusions:
- Vaginal hysterectomy (VH) is recommended over abdominal hysterectomy (AH) due to superior outcomes.
- Laparoscopic hysterectomy (LH) can be an alternative to AH when VH is not feasible, though longer procedures may increase with laparoscopic extent.
- The choice of hysterectomy approach should be a shared decision between patient and surgeon, considering individual benefits and risks.
Background:
The three approaches to hysterectomy for benign disease are abdominal hysterectomy (AH), vaginal hysterectomy (VH), and laparoscopic hysterectomy (LH). Laparoscopic hysterectomy has three further subdivisions depending on the part of the procedure performed laparoscopically.
Objectives:
To assess the most beneficial and least harmful surgical approach to hysterectomy for women with benign gynaecological conditions.
Search Strategy:
We searched the Cochrane Menstrual Disorders and Subfertility Group Specialised Register of controlled trials (15 August 2008), CENTRAL (The Cochrane Library 2008, Issue 3), MEDLINE (1950 to August 2008), EMBASE (1980 to August 2008), Biological Abstracts (1969 to August 2008), the National Research Register, and relevant citation lists.
Selection Criteria:
Only randomised controlled trials comparing one surgical approach to hysterectomy with another were included.
Data Collection And Analysis:
Independent selection of trials and data extraction were employed following Cochrane guidelines.
Main Results:
There were 34 included studies with 4495 women. The benefits of VH versus AH were speedier return to normal activities (mean difference (MD) 9.5 days), fewer febrile episodes or unspecified infections (odds ratio (OR) 0.42), and shorter duration of hospital stay (MD 1.1 days). The benefits of LH versus AH were speedier return to normal activities (MD 13.6 days), lower intraoperative blood loss (MD 45 cc), a smaller drop in haemoglobin (MD 0.55 g/dl), shorter hospital stay (MD 2.0 days), and fewer wound or abdominal wall infections (OR 0.31) at the cost of more urinary tract (bladder or ureter) injuries (OR 2.41) and longer operation time (MD 20.3 minutes). The benefits of LAVH versus TLH were fewer febrile episodes or unspecified infection (OR 3.77) and shorter operation time (MD 25.3 minutes). There was no evidence of benefits of LH versus VH and the operation time (MD 39.3 minutes) as well as substantial bleeding (OR 2.76) were increased in LH. For some important outcomes, the analyses were underpowered to detect important differences or they were simply not reported in trials. Data were absent for many important long-term outcome measures.
Authors' Conclusions:
Because of equal or significantly better outcomes on all parameters, VH should be performed in preference to AH where possible. Where VH is not possible, LH may avoid the need for AH however the length of the surgery increases as the extent of the surgery performed laparoscopically increases. The surgical approach to hysterectomy should be decided by the woman in discussion with her surgeon in light of the relative benefits and hazards.
