Related Experiment Video
Updated: Jun 20, 2026


An Immunohistopathologic Study to Profile the Folate Receptor Beta Macrophage and Vascular Immune Microenvironment in Giant Cell Arteritis
Published on: February 8, 2019
Symptomatic lower extremity vasculitis in giant cell arteritis: a case series
Tanaz A Kermani1, Eric L Matteson, Gene G Hunder
1Division of Rheumatology, Department of Medicine, Mayo Clinic, 200 First Street SW, Rochester, MN 55901, USA.

Insights
Giant cell arteritis (GCA) with lower extremity (LE) vasculitis is rare but causes significant morbidity. Prompt diagnosis and treatment are essential for managing this condition and preventing severe outcomes.
Area of Science:
- Rheumatology
- Vascular Medicine
- Internal Medicine
Background:
- Giant cell arteritis (GCA) is a systemic vasculitis primarily affecting large and medium arteries.
- Lower extremity (LE) involvement in GCA is uncommon but can lead to severe complications.
Observation:
- This study reviewed 19 patients with GCA and symptomatic LE vasculitis.
- The majority of patients were women, with a mean age of 70 years at GCA diagnosis.
- LE symptoms often preceded GCA diagnosis, and cranial symptoms were frequently absent.
Findings:
- Elevated erythrocyte sedimentation rate (ESR) was common, and imaging revealed stenotic, occlusive, or aneurysmal disease in LE arteries.
- Hypertension was the most frequent cardiovascular risk factor.
- While most patients improved with glucocorticoid therapy, some required revascularization surgery or amputation.
Implications:
- Symptomatic LE vasculitis in GCA is a rare but serious condition.
- Early recognition of LE symptoms and prompt initiation of treatment are crucial for improving patient outcomes.
- Further research may elucidate optimal management strategies for this rare presentation of GCA.
Objective:
To describe the clinical features and outcomes of 19 patients with giant cell arteritis (GCA) and symptomatic lower extremity (LE) vasculitis.
Methods:
We reviewed medical records of all patients diagnosed with GCA and symptomatic LE involvement between January 1, 1983, and June 30, 2007, for clinical features, laboratory and radiographic findings, and outcomes.
Results:
From 6212 people evaluated for GCA at our institution between 1983 and 2007, we identified 19 cases of GCA with LE vasculitis, all women. Mean age at GCA diagnosis was 70 years (+/- standard deviation 7.99). Sixteen patients (84.2%) had LE symptoms preceding the diagnosis of GCA, median interval 3 months (range 1-48). Three patients (15.8%) had GCA prior to developing LE claudication, median interval 16 months (range 9-34). Cranial symptoms were absent in 42.1%. No patient had permanent visual loss. Erythrocyte sedimentation rate (ESR) was elevated in 16 patients (84.2%), with median ESR 42.5 mm/h (range 8-103). Imaging studies revealed stenotic, occlusive, or aneurysmal disease that was frequently bilateral and consistent with vasculitis. The superficial femoral arteries were most commonly affected. Five patients (26.3%) had upper extremity involvement. Hypertension was the most common cardiovascular risk factor. All patients received glucocorticoid therapy, with clinical improvement in 15 patients (79%). Median length of followup was 41 months (range 11-180 mo). Five patients (26.3%) underwent LE revascularization surgery. Two patients required LE amputation and 1 patient underwent toe amputation. Five patients received additional immunosuppressive therapy.
Conclusion:
Symptomatic LE vasculitis from GCA is rare. Patients typically present with rapidly progressive LE claudication and elevated inflammatory markers, while cranial symptoms may be absent. GCA with LE involvement is associated with significant morbidity; prompt diagnosis and treatment is essential.
Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:20
Arteries of Lower Limbs
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:16
Vascular Spasm
 01:15
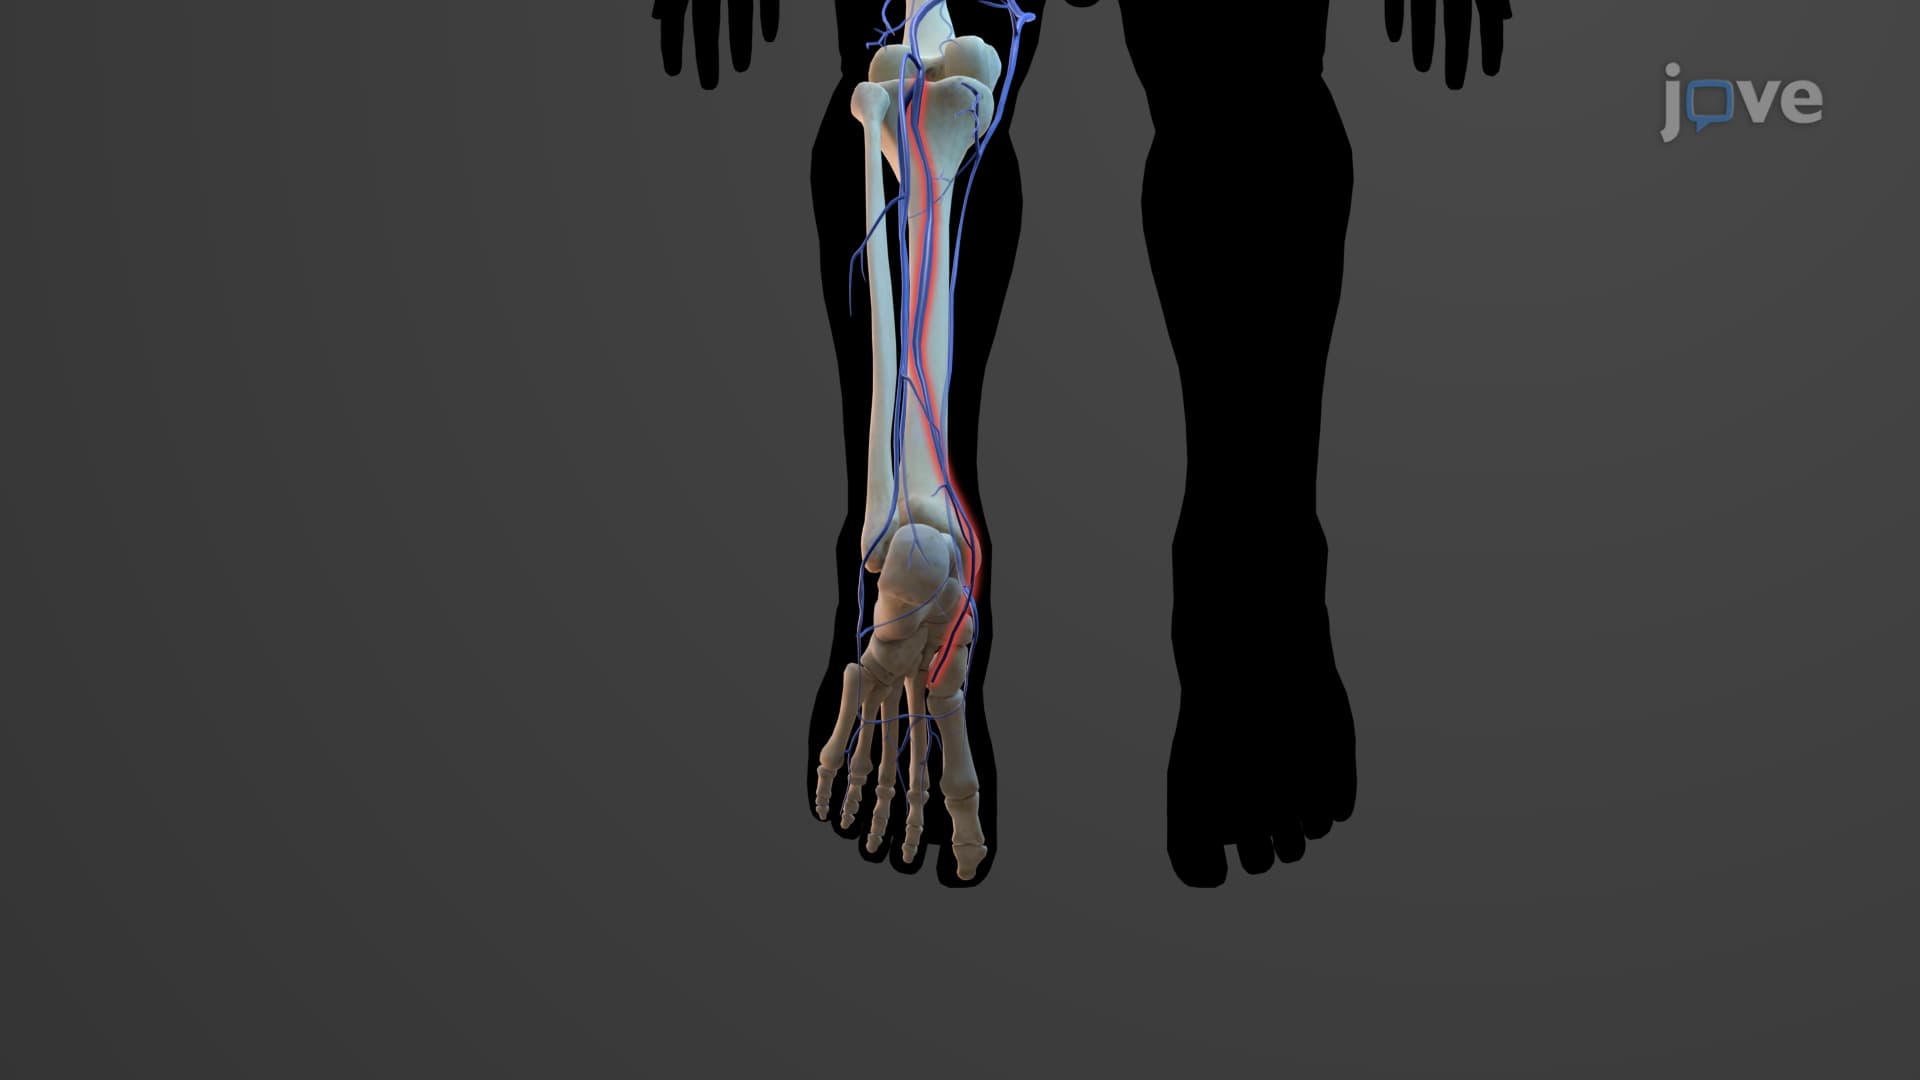
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the knee,...