Related Experiment Video
Updated: Jun 20, 2026
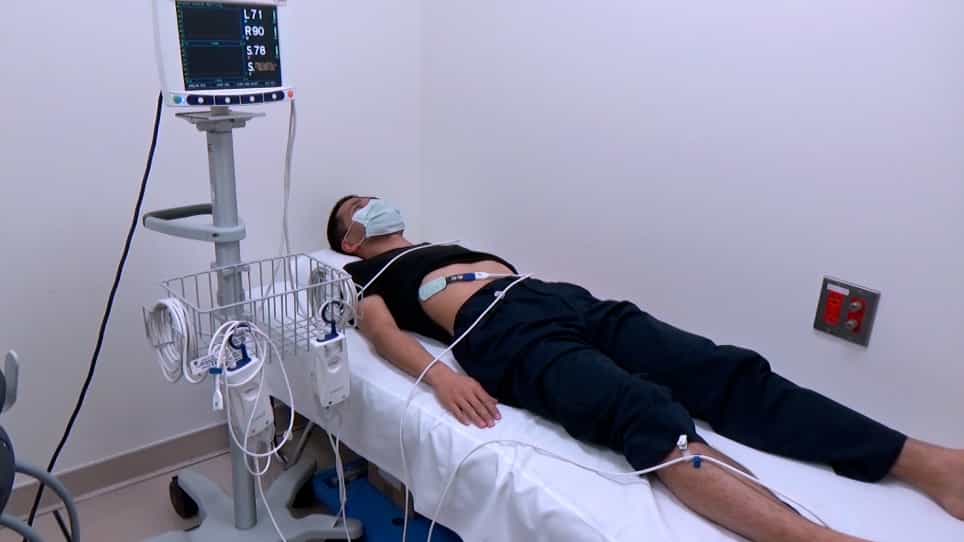

Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Spontaneous erythrocytosis in a patient on chronic hemodialysis
Muniru Adeniyi1, Yijuan Sun, Karen S Servilla
1Section of Nephrology, Raymond G. Murphy VA Medical Center, University of New Mexico School of Medicine, Albuquerque, New Mexico 87108, USA.

While anemia is common in patients on chronic hemodialysis (HD), spontaneous erythrocytosis is rare and can be caused by either the same conditions causing erythrocytosis in the general population or any condition specific to chronic renal failure. We present a patient illustrating this latter circumstance. A 53-year-old man with diabetic nephropathy, with no known disease causing hypoxemia started HD in April 2001. Blood hemoglobin (Hgb) level was 13.7 +/- 2.8 g/dL while his kidney function was normal (1993-1996) and after 1997, with the development of chronic kidney disease, decreased progressively to a low of 10.2 g/dL in March 2001 when erythropoietin (EPO) injections were started. Erythropoietin requirements progressively decreased because of rising Hgb. Erythropoietin was discontinued in mid-2005. Blood hemoglobin continued to rise, however, to a high value of 17.6 g/dL in February 2006. At the same time, endogenous blood EPO level was 3.6 mIU/mL, a value consistent with primary polycythemia. White blood cell and platelet counts were normal. Several small renal cysts, including 1 complex cyst, were detected by ultrasonography and computer tomography in April 2006. He refused surgical treatment. He was treated with small phlebotomies (not returning the blood in the dialyzer at the end of dialysis) and monitoring of Hgb, which decreased toward the desired range. Repeated computer tomographic scans showed a slow increase in the size of the complex cyst and several other cysts. In late 2007 Hgb started rising again, and in February 2008, while the Hgb level was 16.4 g/dL, the endogenous serum EPO level was 726 mIU/mL (upper normal limit 31.5 mIU/mL). Intermittent phlebotomies were reinstituted. He subsequently developed multiple vascular catastrophes and expired from ischemic bowel disease in September 2008. Acquired cystic disease of the kidneys should be considered in HD patients who develop spontaneous erythrocytosis. The risks of acquired cystic disease include, in addition to the development of malignancy, vascular events from elevated Hgb.
While anemia is common in patients on chronic hemodialysis (HD), spontaneous erythrocytosis is rare and can be caused by either the same conditions causing erythrocytosis in the general population or any condition specific to chronic renal failure. We present a patient illustrating this latter circumstance. A 53-year-old man with diabetic nephropathy, with no known disease causing hypoxemia started HD in April 2001. Blood hemoglobin (Hgb) level was 13.7 +/- 2.8 g/dL while his kidney function was normal (1993-1996) and after 1997, with the development of chronic kidney disease, decreased progressively to a low of 10.2 g/dL in March 2001 when erythropoietin (EPO) injections were started. Erythropoietin requirements progressively decreased because of rising Hgb. Erythropoietin was discontinued in mid-2005. Blood hemoglobin continued to rise, however, to a high value of 17.6 g/dL in February 2006. At the same time, endogenous blood EPO level was 3.6 mIU/mL, a value consistent with primary polycythemia. White blood cell and platelet counts were normal. Several small renal cysts, including 1 complex cyst, were detected by ultrasonography and computer tomography in April 2006. He refused surgical treatment. He was treated with small phlebotomies (not returning the blood in the dialyzer at the end of dialysis) and monitoring of Hgb, which decreased toward the desired range. Repeated computer tomographic scans showed a slow increase in the size of the complex cyst and several other cysts. In late 2007 Hgb started rising again, and in February 2008, while the Hgb level was 16.4 g/dL, the endogenous serum EPO level was 726 mIU/mL (upper normal limit 31.5 mIU/mL). Intermittent phlebotomies were reinstituted. He subsequently developed multiple vascular catastrophes and expired from ischemic bowel disease in September 2008. Acquired cystic disease of the kidneys should be considered in HD patients who develop spontaneous erythrocytosis. The risks of acquired cystic disease include, in addition to the development of malignancy, vascular events from elevated Hgb.
More Related Videos


Related Concept Videos
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:24
Factors Affecting Erythropoiesis
Several factors influence the erythrocyte production rate, with tissue oxygen level being among the most critical. Intense exercise or high altitudes can cause tissue hypoxia, which triggers the kidneys to release more erythropoietin (EPO) into the bloodstream.
EPO then...
 01:24
Hemodialysis II: Procedure and Complications
 01:14
Erythropoiesis
01:14Erythropoiesis
 01:25
Hemodialysis I: Introduction