Related Experiment Video
Updated: Jun 20, 2026


Analysis of Beta-cell Function Using Single-cell Resolution Calcium Imaging in Zebrafish Islets
Published on: July 3, 2018
How to make beta cells?
Malgorzata Borowiak1, Douglas A Melton
1Harvard Stem Cell Institute, Department of Stem Cell and Regeneration Biology, Harvard University, Cambridge, MA 02138, USA. mborowiak@mcb.harvard.edu

Abstract:
Insulin-producing beta cells are lost or insufficient in diabetic patients, presenting the medical challenge for new beta cells. Currently, there are three strategies that offer promise. One involves the generation of beta cells de novo by directing the differentiation of either embryonic stem cells or induced pluripotent cells to the beta cell lineage. The second is based on the conversion of another terminally differentiated cell to beta cells in a process called reprogramming. The third approach is to promote the replication of existing beta cells either in vivo or in vitro. Significant progress is evident for each strategy, but it remains unclear which approach will ultimately prove successful.
Insights
Diabetic patients need new insulin-producing beta cells. Current strategies include stem cell differentiation, cell reprogramming, and beta cell replication, but the most effective method remains uncertain.
Area of Science:
- Regenerative Medicine
- Endocrinology
- Cell Biology
Background:
- Diabetes mellitus is characterized by the loss or insufficiency of insulin-producing beta cells.
- This deficiency poses a significant challenge for effective diabetes management and treatment.
- The need for novel therapeutic strategies to restore beta cell function is critical.
Purpose of the Study:
- To review and summarize the current promising strategies for generating new beta cells to address diabetes.
- To evaluate the progress and potential of different approaches in beta cell replacement therapy.
- To highlight the ongoing challenges and future directions in the field of beta cell regeneration.
Main Methods:
- Review of current scientific literature on beta cell generation and regeneration.
- Analysis of three primary strategies: de novo differentiation, cell reprogramming, and beta cell replication.
- Assessment of progress and limitations for each therapeutic approach.
Main Results:
- Significant advancements have been made in generating beta cells from embryonic stem cells and induced pluripotent stem cells.
- Cellular reprogramming shows potential for converting existing cell types into functional beta cells.
- Methods to promote existing beta cell replication in vivo and in vitro are also under active investigation.
- Each strategy demonstrates progress, yet none has definitively emerged as the optimal solution.
Conclusions:
- Multiple promising avenues exist for generating new beta cells to treat diabetes.
- Further research is essential to determine the most effective and clinically viable strategy.
- The ultimate success of beta cell replacement therapy will depend on continued innovation and comparative analysis of these approaches.

Related Concept Videos
 01:25
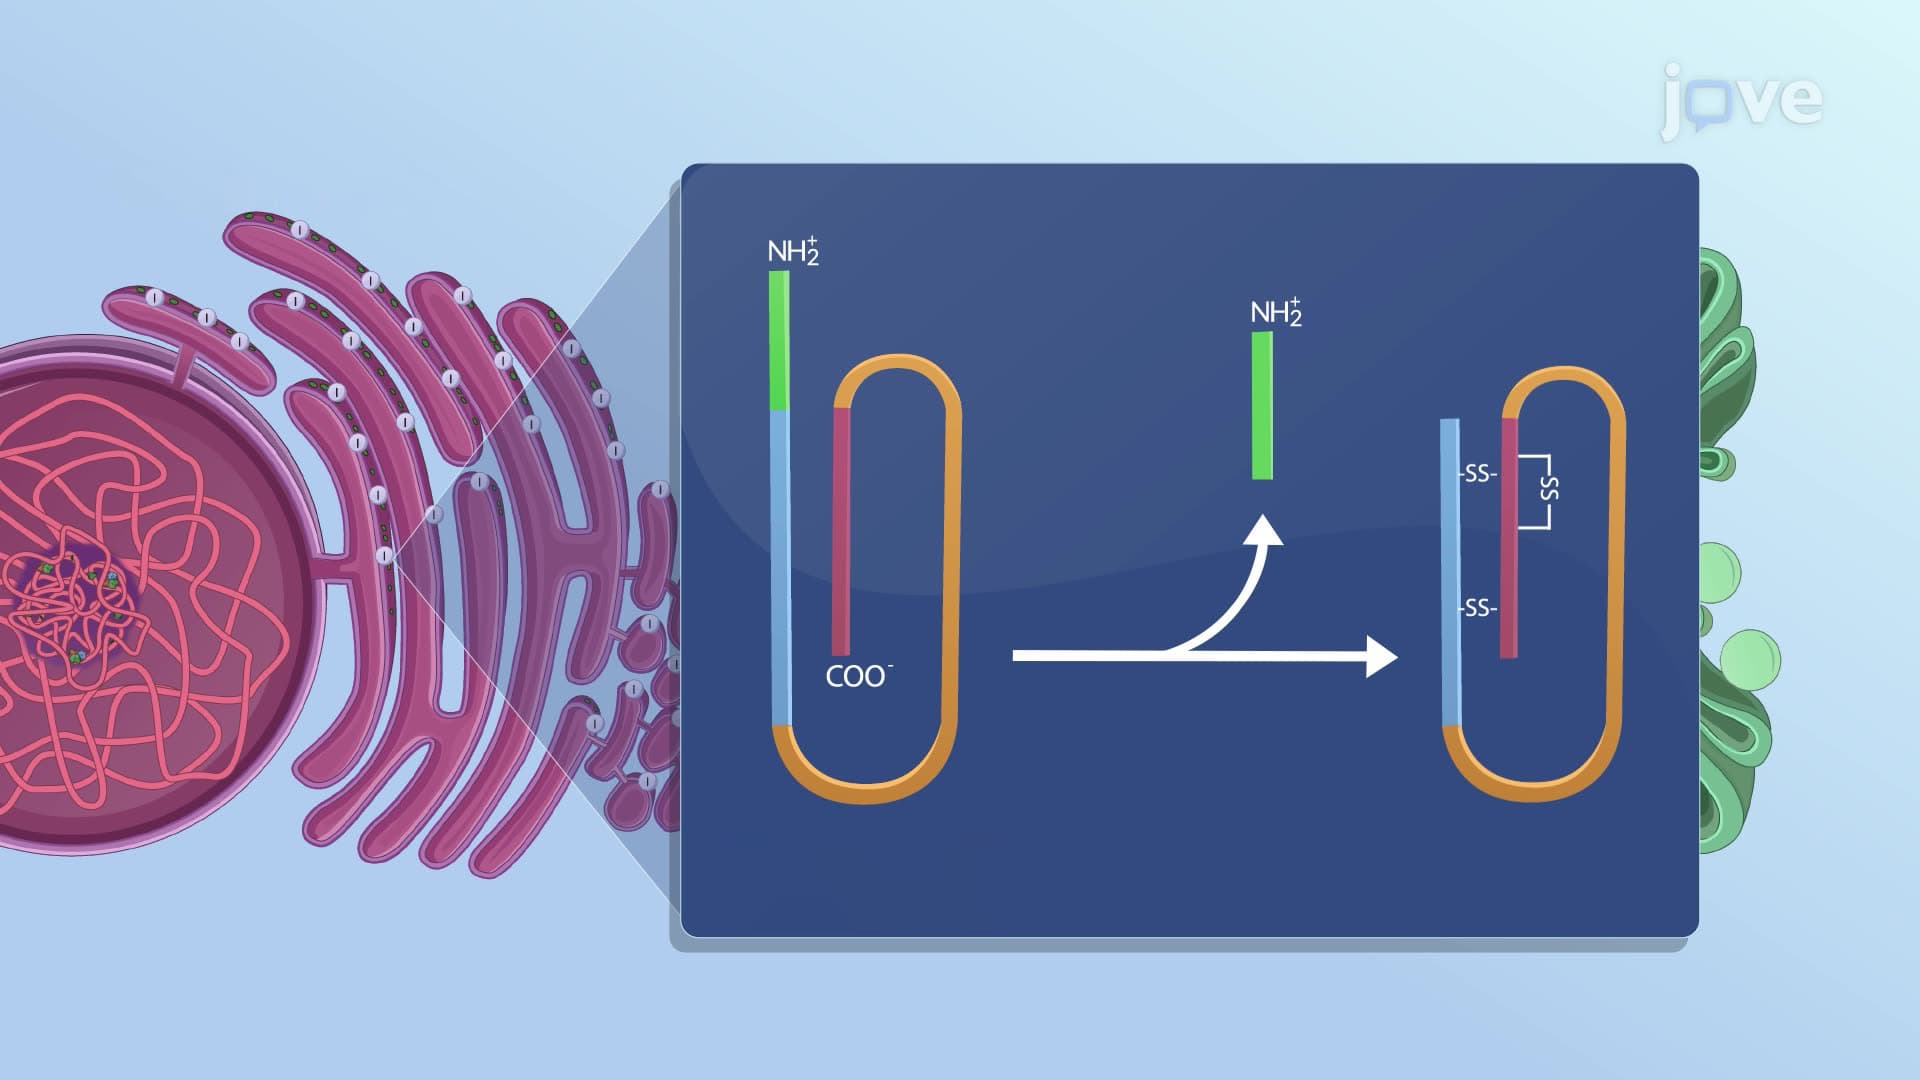
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:05
Insulin Secretory Vesicles
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:26
Type I Diabetes II: Pathophysiology
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...
 01:16
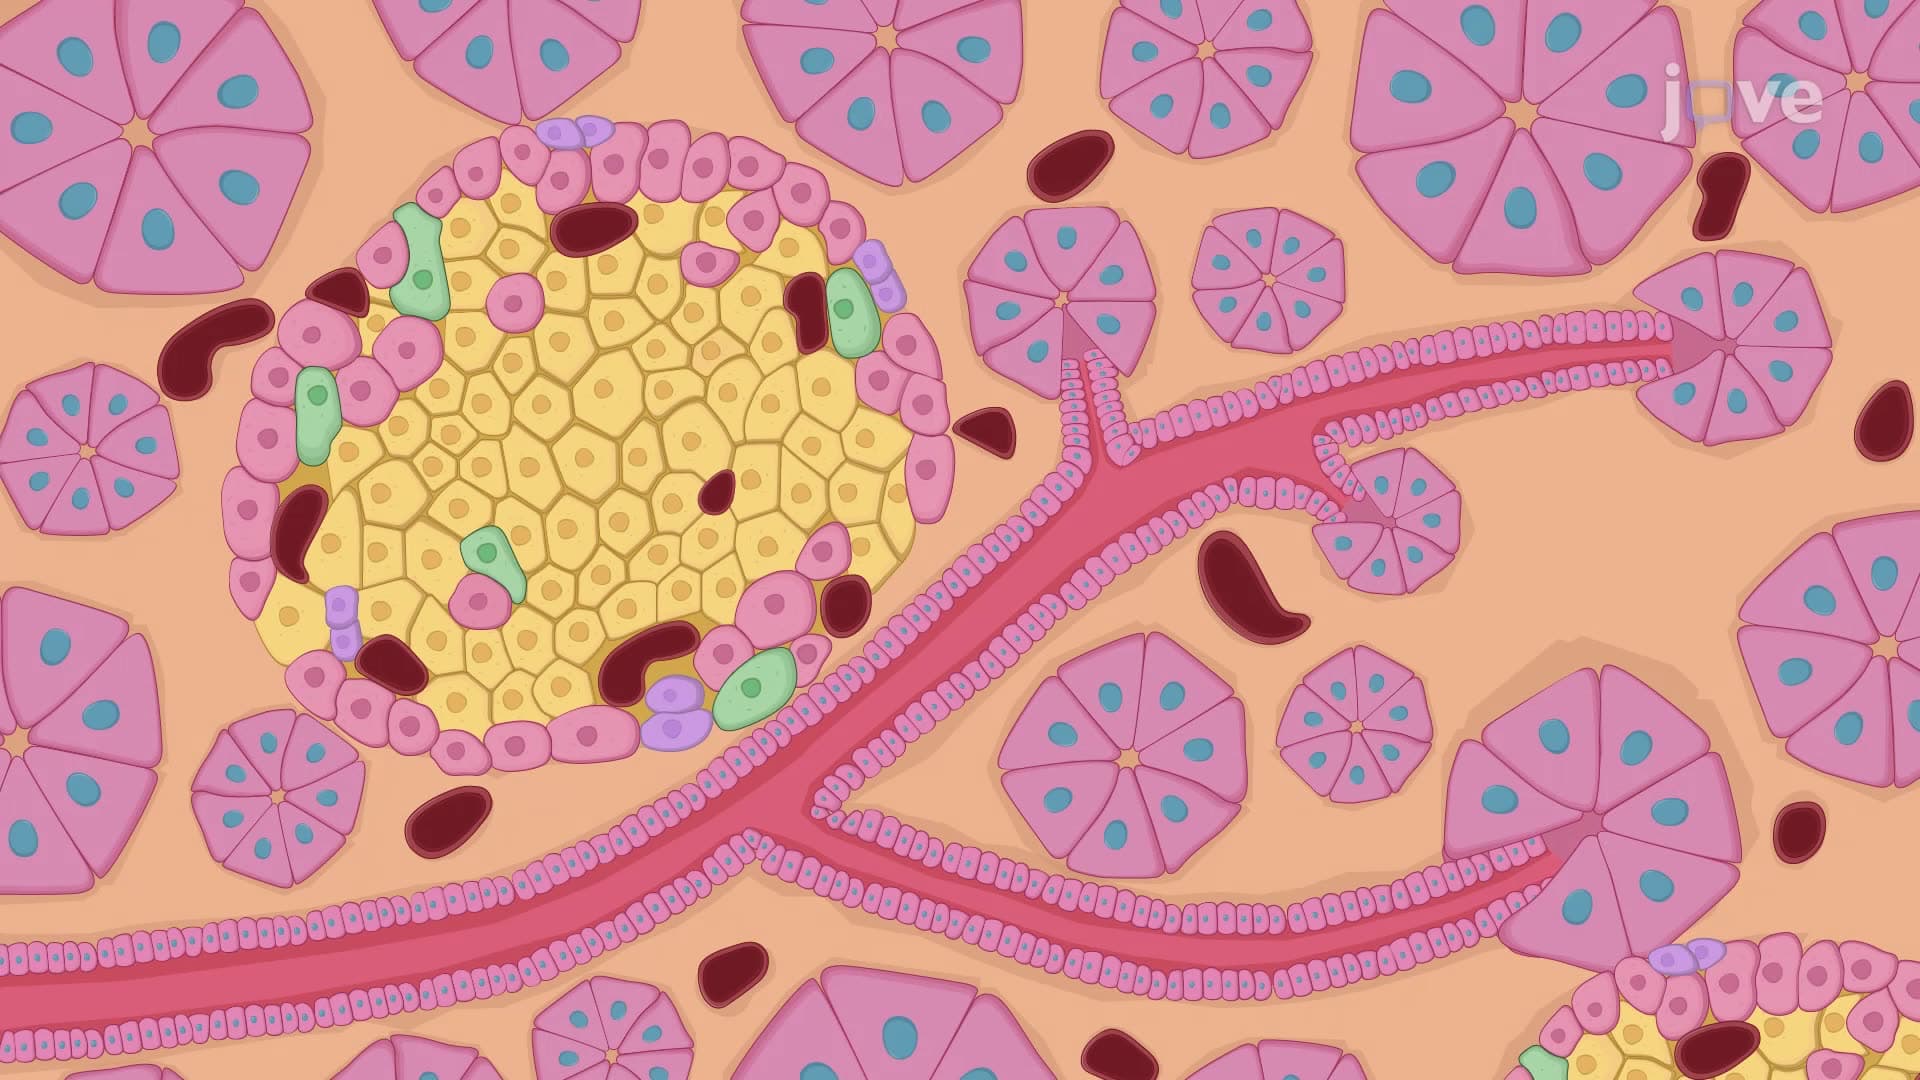
Cells and Secretions of the Pancreas
Exocrine function is carried out by acinar cells, organized into clusters known as acini. These cells contribute to digestion by releasing substantial quantities of enzyme-rich, alkaline digestive juices.
Concurrently, the dispersed clusters of endocrine cells throughout the...