Related Experiment Video
Updated: Jun 19, 2026

The Antihypertensive Effects and Mechanisms of Huotan Jiedu Tongluo Decoction in Rats with H-Type Hypertension
Published on: May 17, 2024
Chronic hypertension aggravates heat stress-induced brain damage: possible neuroprotection by cerebrolysin
Dafin Fior Muresanu1, Sibilla Zimmermann-Meinzingen, Hari Shanker Sharma
1Department of Neurology, University of Medicine and Pharmacy Iuliu Hatieganu, Cluj-Napoca, Romania.

Abstract:
Whole body hyperthermia (WBH) aggravates brain edema formation and cell damage in chronic hypertensive rats compared with normotensive animals. In this investigation, we examined the influence of cerebrolysin on WBH-induced edema formation and brain pathology in hypertensive and normotensive rats. Rats subjected to 4 h WBH at 38 degrees C in a biological oxygen demand (BOD) incubator showed breakdown of the blood-brain barrier (BBB), reduced cerebral blood flow (CBF), edema formation and cell injuries in several parts of the brain. These effects were further aggravated in chronic hypertensive rats (two-kidney one clip model (2K1C), for 4 weeks) subjected to WBH. Pretreatment with cerebrolysin (5 mL/kg, 24 h and 30 min before heat stress) markedly attenuated the BBB dysfunction and brain pathology in normal animals. However, in hypertensive animals, a high dose of cerebrolysin (10 mL/kg, 24 h and 30 min before heat stress) was needed to attenuate WBH-induced BBB dysfunction and brain pathology. These observations indicate that heat stress could affect differently in normal and hypertensive conditions. Furthermore, our results suggest that patients suffering from various chronic cardiovascular diseases may respond differently to hyperthermia and to neuroprotective drugs, e.g., cerebrolysin not reported earlier.
Related Concept Videos
 01:22
Cerebral Edema ll: Pathophysiology
 01:29
Increased Intracranial Pressure ll: Pathophysiology
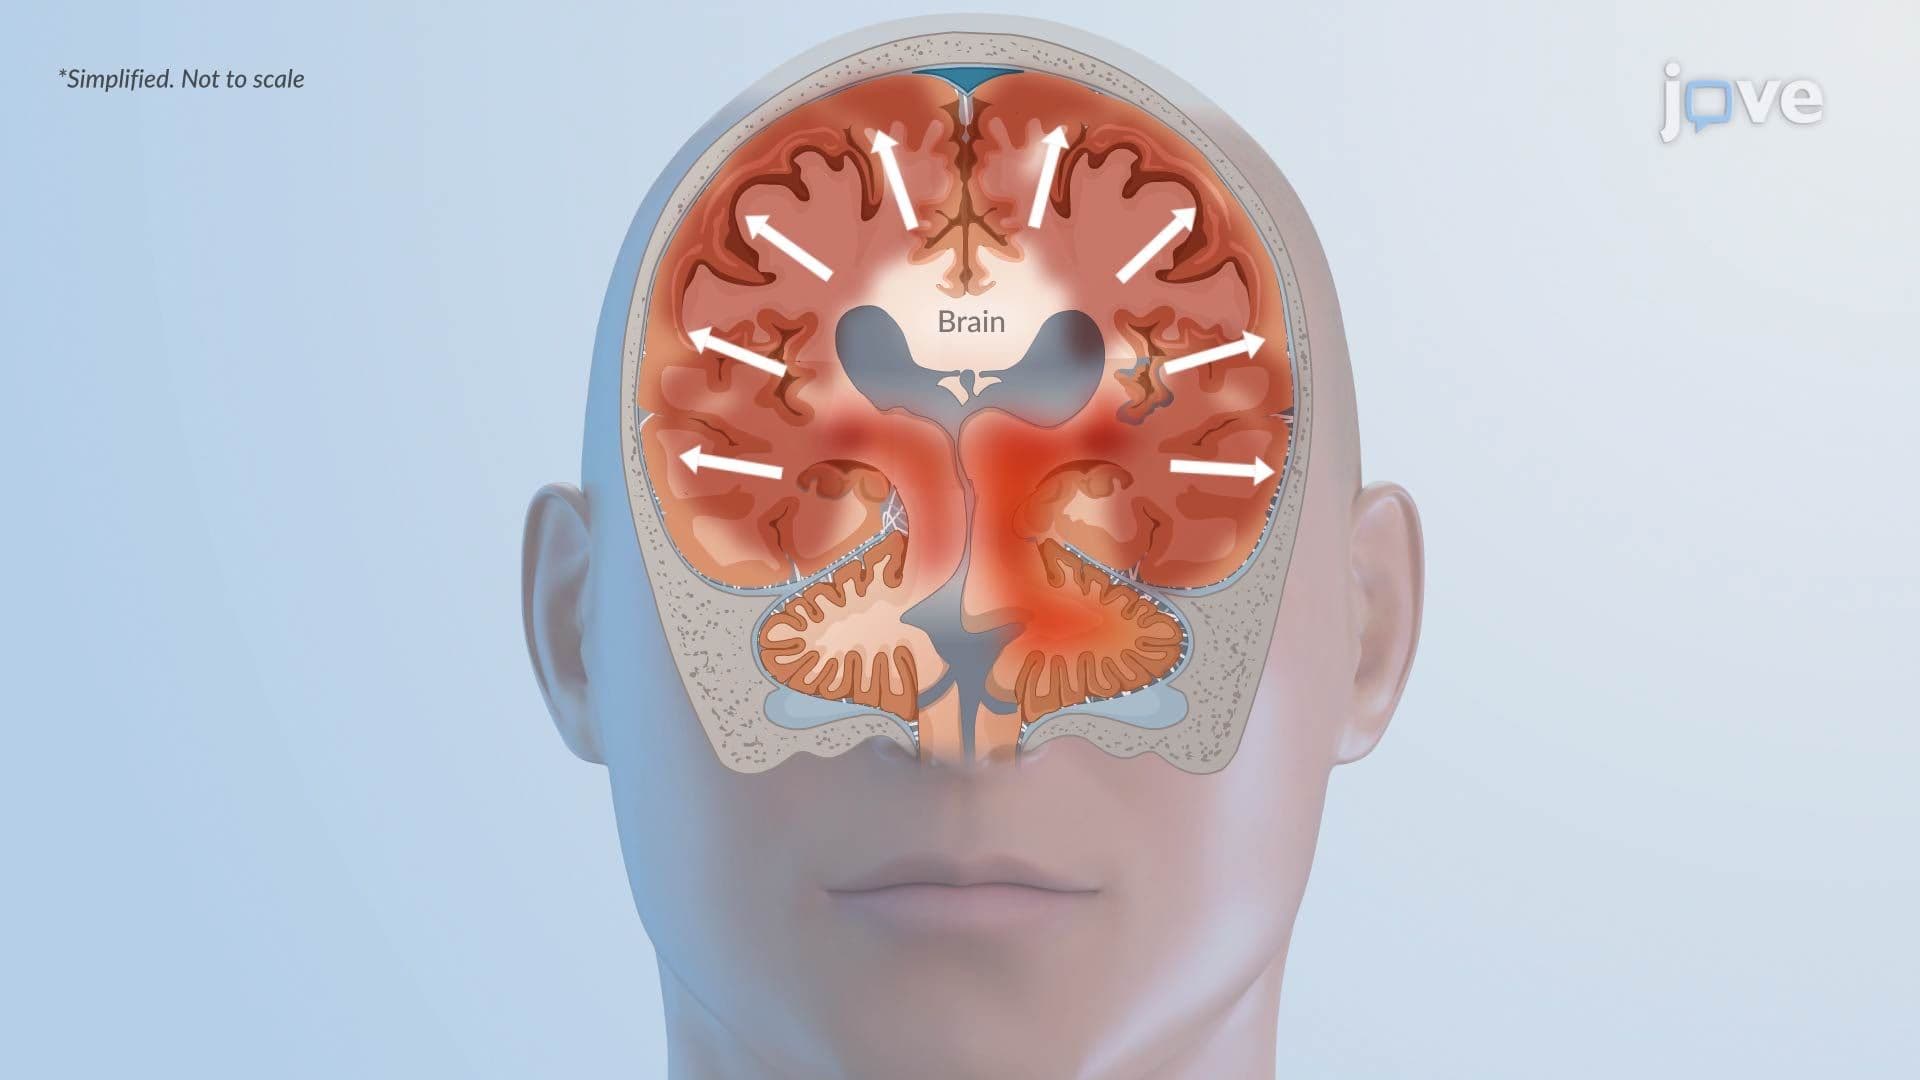 01:21
Cytotoxic Edema: Pathophysiology
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:18
Hypertension and Regulation of Blood Pressure
 01:29
Hepatic Encephalopathy