Related Experiment Video
Updated: Jun 16, 2026
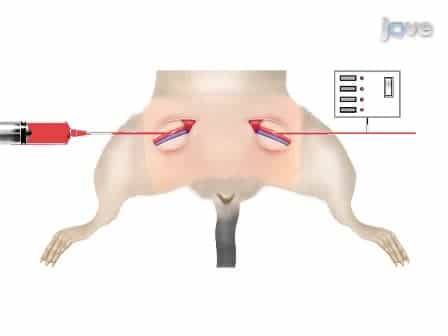

Fixed Volume or Fixed Pressure: A Murine Model of Hemorrhagic Shock
Published on: June 6, 2011
Resuscitation with fresh whole blood ameliorates the inflammatory response after hemorrhagic shock
Amy T Makley1, Michael D Goodman, Lou Ann W Friend
1Department of Surgery, University of Cincinnati, Cincinnati, Ohio, USA.

Background:
Hemorrhagic shock is the leading cause of potentially preventable death after traumatic injury. Hemorrhage and subsequent resuscitation may result in a dysfunctional systemic inflammatory response and multisystem organ failure, leading to delayed mortality. Clinical evidence supports improved survival and reduced morbidity when fresh blood products are used as resuscitation strategies. We hypothesized that the transfusion of fresh whole blood (FWB) attenuates systemic inflammation and reduces organ injury when compared with conventional crystalloid resuscitation after hemorrhagic shock.
Methods:
Male mice underwent femoral artery cannulation and hemorrhage to a systolic blood pressure of 25 mm Hg +/- 5 mm Hg. After 60 minutes, the mice were resuscitated with either FWB or lactated Ringer's solution (LR). Mice were decannulated and killed at intervals for tissue histology, serum cytokine analysis, and vascular permeability studies. Separate groups of mice were followed for survival studies.
Results:
When compared with FWB, mice resuscitated with LR required increased resuscitation fluid volume to reach goal systolic blood pressure. When compared with sham or FWB-resuscitated mice, LR resuscitation resulted in increased serum cytokine levels of macrophage inflammatory protein-1alpha, interleukin-6, interleukin-10, macrophage-derived chemokine, KC, and granulocyte macrophage colony stimulating factor as well as increased lung injury and pulmonary capillary permeability. No survival differences were seen between animals resuscitated with LR or FWB.
Conclusions:
Resuscitation with LR results in increased systemic inflammation, vascular permeability, and lung injury after hemorrhagic shock. Resuscitation with FWB attenuates the inflammation and lung injury seen with crystalloid resuscitation. These findings suggest that resuscitation strategies using fresh blood products potentially reduce systemic inflammation and organ injury after hemorrhagic shock.


Related Concept Videos
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized, and...
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:24
Inflammatory Response II: Inflammatory Exudate and Tissue Repair
The typical wound exudate is odorless, transparent, straw-colored, thin, and watery. Exudate, however, can differ depending on the state of wound healing. Likewise, the exudate's...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:25
Acute Inflammation III: Local and Systemic Effects