Related Experiment Videos
Increasing supplemental thyroid hormone use among premature infants born at 23 to 32 weeks' gestation
Megan Linn1, Bradley A Yoder, Reese H Clark
1Department of Pediatrics, University of Utah, Salt Lake City, Utah 84158-1289, USA.

Insights
Thyroid hormone therapy (levo-thyroxine) increased significantly in very premature infants over a decade, especially for those born earliest. Current treatment patterns lack evidence from randomized trials, necessitating new research.
Area of Science:
- Neonatalogy
- Pediatric Endocrinology
- Clinical Pharmacy
Background:
- Thyroid hormone deficiency is a concern in preterm infants.
- Levothyroxine (l-thyroxine) is used to treat hypothyroidism.
- Evidence supporting routine thyroid supplementation in preterm infants is limited.
Purpose of the Study:
- To assess trends in levo-thyroxine (l-thyroxine) therapy among very premature newborns over a 10-year period.
- To analyze l-thyroxine use based on gestational age and birth year.
- To compare current treatment patterns with existing clinical trial protocols.
Main Methods:
- Retrospective analysis of an electronic database from a large private neonatal practice group.
- Inclusion of 96,813 neonates with gestational ages between 23 and 32 weeks, managed between 1997 and 2006.
- Analysis of l-thyroxine use by birth year and gestational age.
Main Results:
- L-thyroxine use increased with decreasing gestational age, peaking at 8.4% for 24-week infants.
- Overall l-thyroxine supplementation increased 2.6-fold for infants ≤26 weeks' GA from 1997-1999 to 2004-2006.
- The highest treatment rate (12.8%) was observed in 24-week GA infants in 2006; treatment initiation was typically around 23 days of life.
Conclusions:
- L-thyroxine treatment for very preterm infants has significantly increased over the past decade.
- Treatment patterns are not consistent with protocols from published randomized trials.
- Further focused randomized controlled trials are needed to guide l-thyroxine supplementation in this population.
Abstract:
We assessed the pattern of levo-thyroxine (l-thyroxine) therapy in very premature newborns over a 10-year period. We analyzed the electronic database of a large private neonatal practice group (Pediatrix, Ft. Lauderdale, FL) for 23- to 32-week gestation neonates ( N = 96,813) managed during 1997 to 2006. L-thyroxine use was analyzed by birth year and by gestational age (GA). L-thyroxine use increased with decreasing GA (nadir 0.3% at 32 weeks, peak 8.4% at 24 weeks). L-thyroxine supplementation increased 2.6-fold over time among infants ≤26 weeks' GA (3.4% in 1997 to 1999 to 8.7% in 2004 to 2006), but did not change among infants born at ≥29 weeks' GA. The highest rate of l-thyroxine supplementation (12.8%) occurred among 24-week GA infants in 2006. Median age at start of l-thyroxine was 23 days (25 to 75%, 15 to 38 days). Only 2% of treated infants were started on day of life 1. Despite no clear evidence from randomized trials supporting thyroid supplementation, l-thyroxine treatment of very preterm infants has significantly increased over the past decade. As l-thyroxine treatment was not consistent with protocols from published randomized trials, new focused randomized controlled trials are needed.
Related Concept Videos
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:20
Synthesis and Regulation of Thyroid Hormones
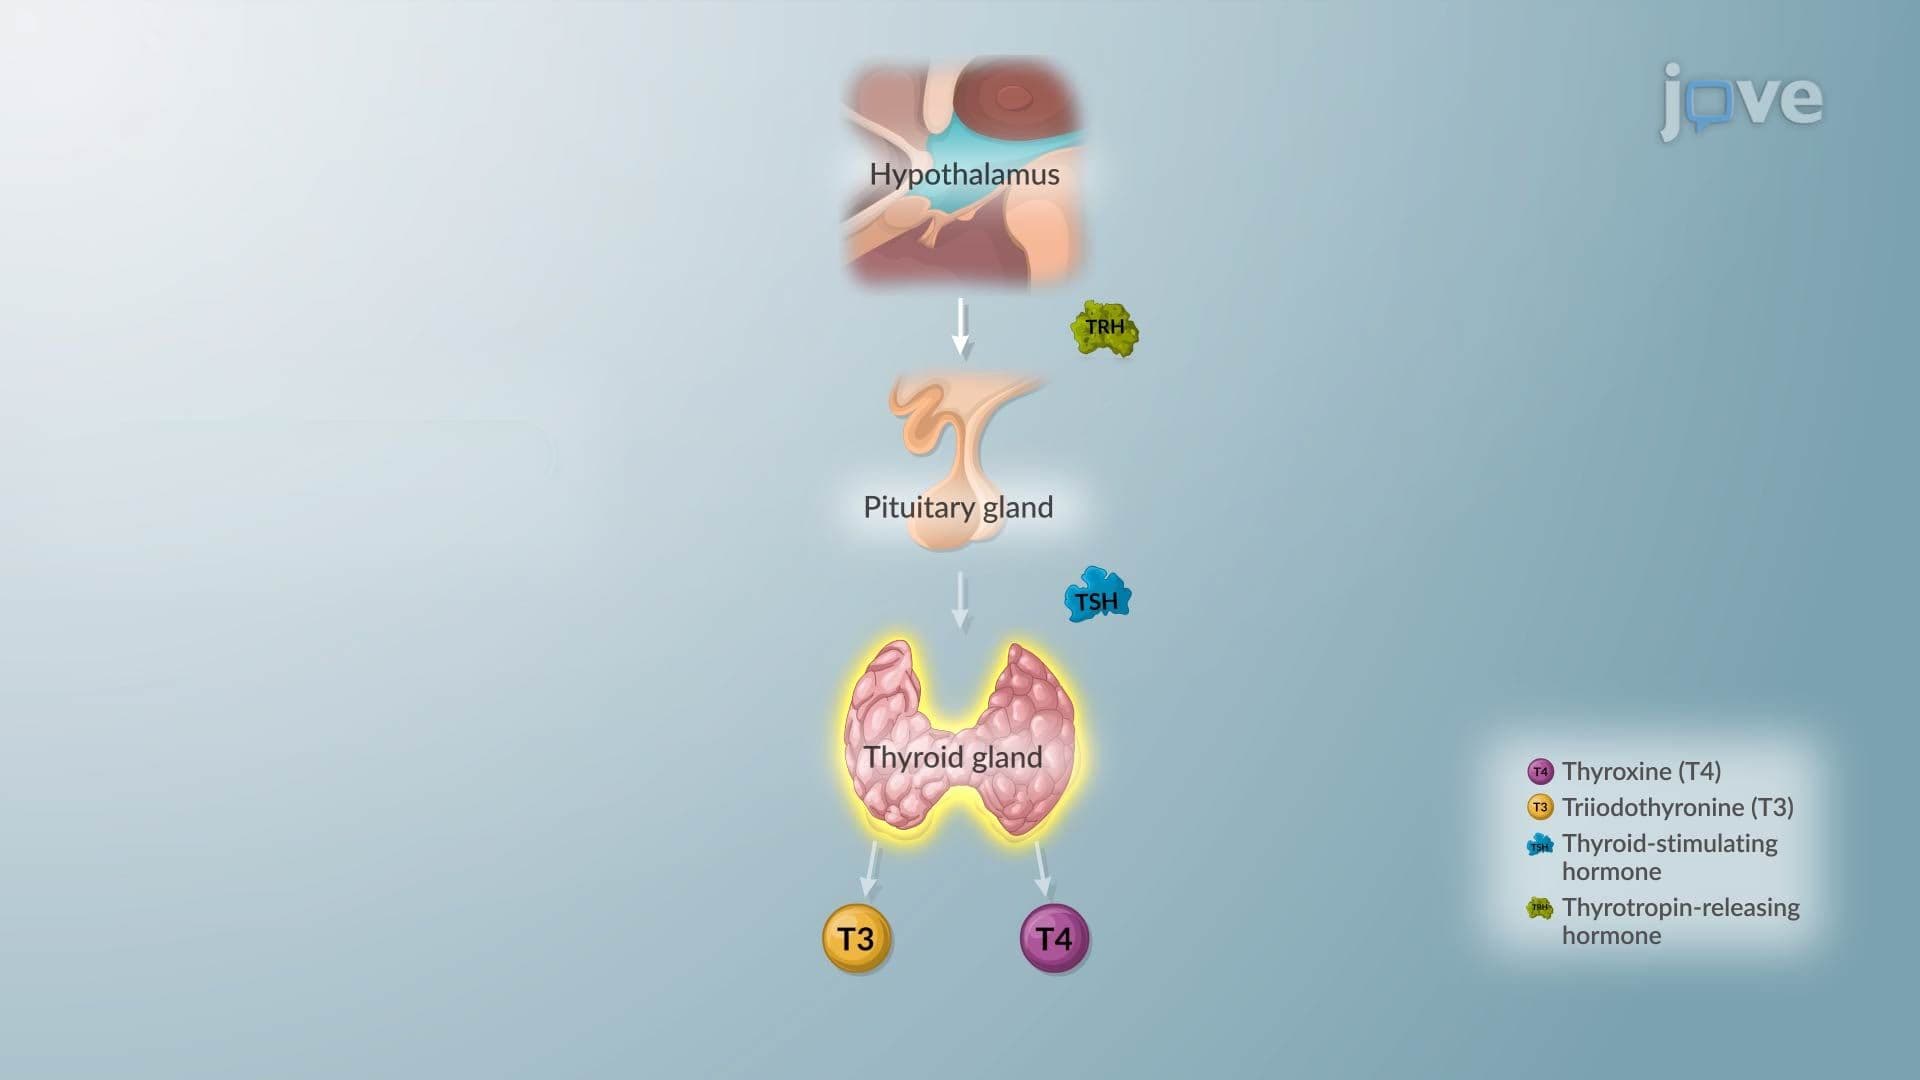
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:27
Goiter
 01:23
Hypothyroidism II: Pathophysiology