Related Experiment Video
Updated: Jun 13, 2026


Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
Are analogue insulins superior to human insulin in clinical practice?
1Division of Endocrinology of the Department of Internal Medicine, Division of Endocrinology and Metabolism, Philadelphia College of Osteopathic Medicine, Suite 324, Philadelphia, PA 19131-1626, USA. jeffreyfreemando@aol.com

Abstract:
Insulin analogues were designed to provide more physiologic pharmacokinetic and pharmacodynamic properties compared with human insulin. This article examines the literature over a 2-year period, focusing on studies directly comparing analogue and human insulin in controlled clinical trials and large observational studies documenting the introduction of, or change to, analogue insulin in clinical practice. Findings indicate that analogues provide objective benefits that include improved glycemic control, lower risk of hypoglycemia, lower glucose variability, and (for insulin detemir) reduced weight gain. Recent data with analogues also explore their safety and efficacy in special patient groups such as children and adolescents. These data complement increasing evidence that analogues offer improved acceptability and accessibility to people with diabetes.

Related Concept Videos
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...
 01:25
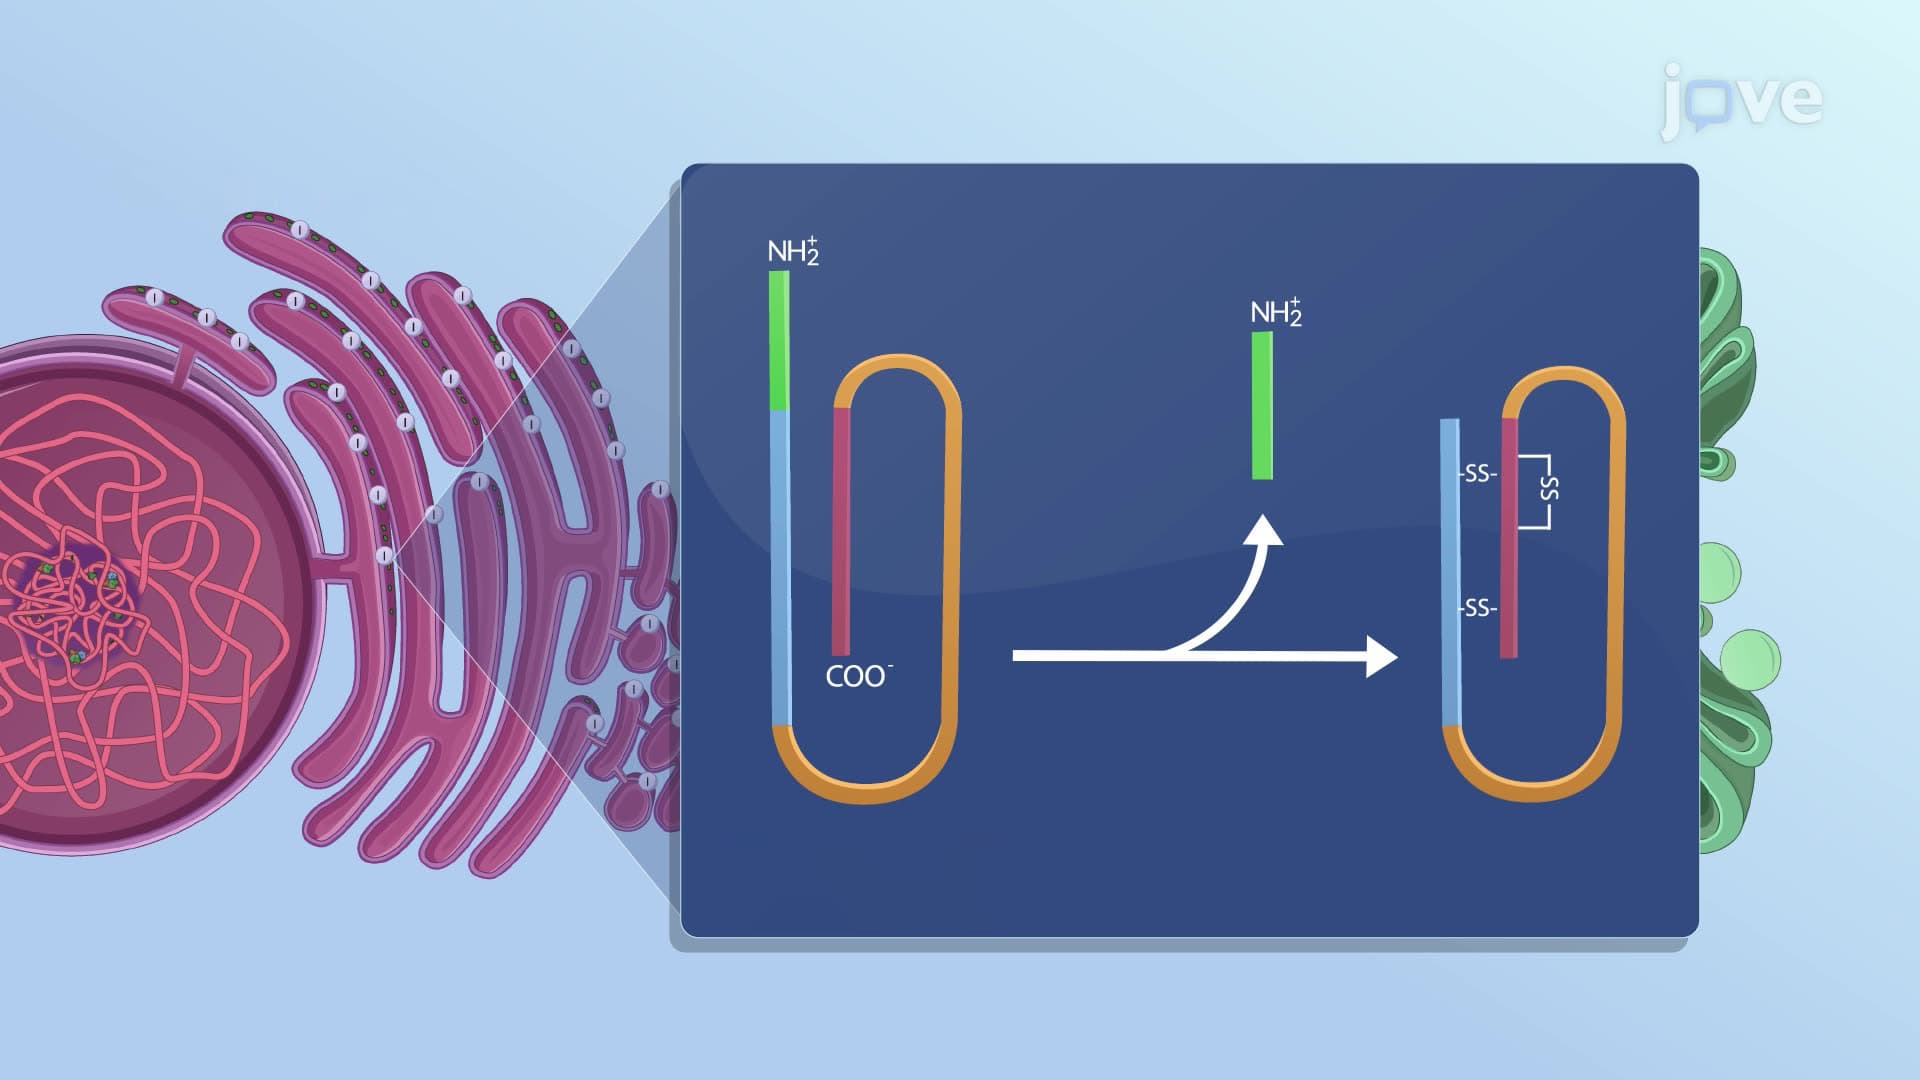
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:30
Production of Pharmaceuticals
 01:17
Oral Hypoglycemic Agents: Sulfonylureas
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...