Related Experiment Video
Updated: Jun 11, 2026
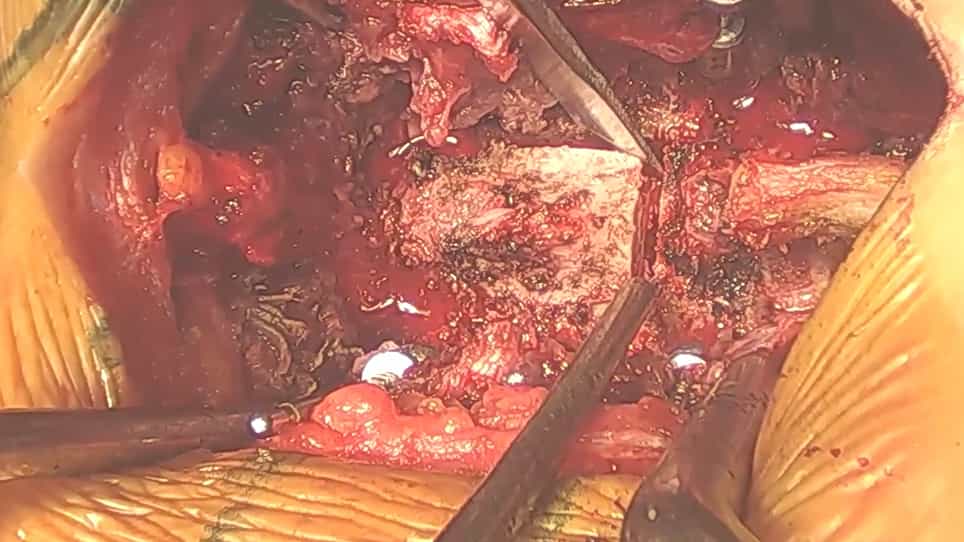

Laminectomy for the Removal of Thoracic Ossification of the Ligamentum Flavum (TOLF) Using Ultrasonic and Conventional Osteotomes
Published on: April 21, 2023
Clinical analysis of thoracic ossified ligamentum flavum without ventral compressive lesion
Sang Hoon Yoon1, Wook Ha Kim, Sang-Bong Chung
1Department of Neurosurgery, Seoul National University Bundang Hospital, Seoul National University College of Medicine, Seongnam-si, Gyeonggi-do, South Korea.

Abstract:
The aim of this study was to analyze the clinical characteristics of thoracic ossified ligamentum flavum (OLF) and to elucidate prognostic factors as well as effective surgical treatment modality. The authors analyzed 106 thoracic OLF cases retrospectively from January 1999 to December 2008. The operative (n = 40) and the non-operative group (n = 66) were diagnosed by magnetic resonance imaging (MRI) and/or computed tomography (CT) imaging. We excluded cases exhibiting ventral compressive lesions causing subarachnoid space effacement in thoracic vertebrae as well as those with a coexisting cervical compressive myelopathy. Those in the operative group were treated with decompressive laminectomy as well as resection of OLF. The preoperative neurologic status and postoperative outcomes of patients, as indicated by their modified Japanese Orthopedic Association (mJOA) scores and recovery rate (RR), Modic changes, the axial (fused or non-fused) and sagittal (omega or beak) configurations of OLF, and the ratios of the cross-sectional area (CSA) and anteroposterior diameter (APD) of the most compressed level were studied. The most commonly affected segment was the T10-11 vertebral body level (n = 49, 27.1%) and the least affected segment was the T7-8 level (n = 1, 0.6%). The ratios of the CSA in non-fused and fused types were 77.3 and 59.3% (p < 0.001). When Modic changes were present with OLF, initial mJOA score was found to be significantly lower than those without Modic change (7.62 vs. 9.09, p = 0.033). Neurological status improved after decompressive laminectomy without fusion (preoperative vs. last mJOA; 7.1 ± 2.01 vs. 8.57 ± 1.91, p < 0.001). However, one patient exhibited transient deterioration of her neurological status after surgery. In the axial configuration, fused-type OLF revealed a significant risk for a decreased postoperative mJOA score (0-7, severe and moderate) (Odds ratio: 5.54, χ (2) = 4.41, p = 0.036, 95% CI: 1.014-30.256). The results indicated that the new categorization of axial-type of OLF is a helpful predictor of postoperative patient outcome and fused type was related with poor prognosis. In OLF cases free from ventral lesions compressing the spinal cord, decompressive laminectomy is enough for successful surgical outcome. Therefore, early surgical treatment will be considered in cases with fused-type OLF compressing spinal cord even though they do not have myelopathic symptoms.
Related Concept Videos
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:15
Thoracic Aorta
 01:08
Pneumothorax II: Pathophysiology
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:20
The Thoracic Cage: Ribs
Parts of a Typical Rib
A typical rib has a head, neck, and body. The posterior end of the rib is called the head, followed by a narrow neck. The head articulates primarily with the costal facet...