Related Experiment Video
Updated: Jun 6, 2026


ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
Endoscopic resection and ablation versus esophagectomy for high-grade dysplasia and intramucosal adenocarcinoma
Jörg Zehetner1, Steven R DeMeester, Jeffrey A Hagen
1Department of Surgery, Keck School of Medicine, University of Southern California, Los Angeles, Calif 90033, USA.

Background:
Esophagectomy has been the traditional therapy for high-grade dysplasia and intramucosal adenocarcinoma. New endoscopic approaches allow treatment of these lesions with esophageal preservation. The aim of this study was to compare the outcome of endoscopic therapy with esophagectomy for high-grade dysplasia and intramucosal cancer.
Methods:
A retrospective review was performed of all patients treated for high-grade dysplasia or intramucosal adenocarcinoma from 2001 to April 2010.
Results:
Endoscopic therapy was performed in 40 patients (high-grade dysplasia = 22, intramucosal cancer = 18) and esophagectomy in 61 patients (high-grade dysplasia = 13, intramucosal cancer = 48). Endotherapy consisted of 102 endoscopic resections and 79 mucosal ablations (median 3 interventions per patient). In the endotherapy group, intramucosal cancer was completely resected in all patients. At last assessment, 10 patients have been converted to intestinal metaplasia without dysplasia and 21 to no residual intestinal metaplasia. Five patients have follow-up biopsy procedures pending after recent ablation, and esophagectomy was performed in 3 patients for failed endotherapy. A laparoscopic Nissen fundoplication has been performed in 8 patients after eradication of intestinal metaplasia. Esophagectomy resected the mucosal disease with negative margins in all patients. Compared with esophagectomy, endotherapy was associated with significantly lower morbidity (39% vs 0; P < .0001) and similar survival (94% at 3 years in both groups; median follow-up 34 months after esophagectomy vs 17 months after endotherapy; P = .0026).
Conclusions:
Endoscopic therapy for high-grade dysplasia or intramucosal cancer has lower morbidity than an esophagectomy and similar survival during short-term follow-up, but required multiple procedures in most patients. Both therapies are appropriate options, but preservation of the esophagus allows the option of a fundoplication for reflux control, perhaps further improving long-term quality of life.
Related Concept Videos
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:24
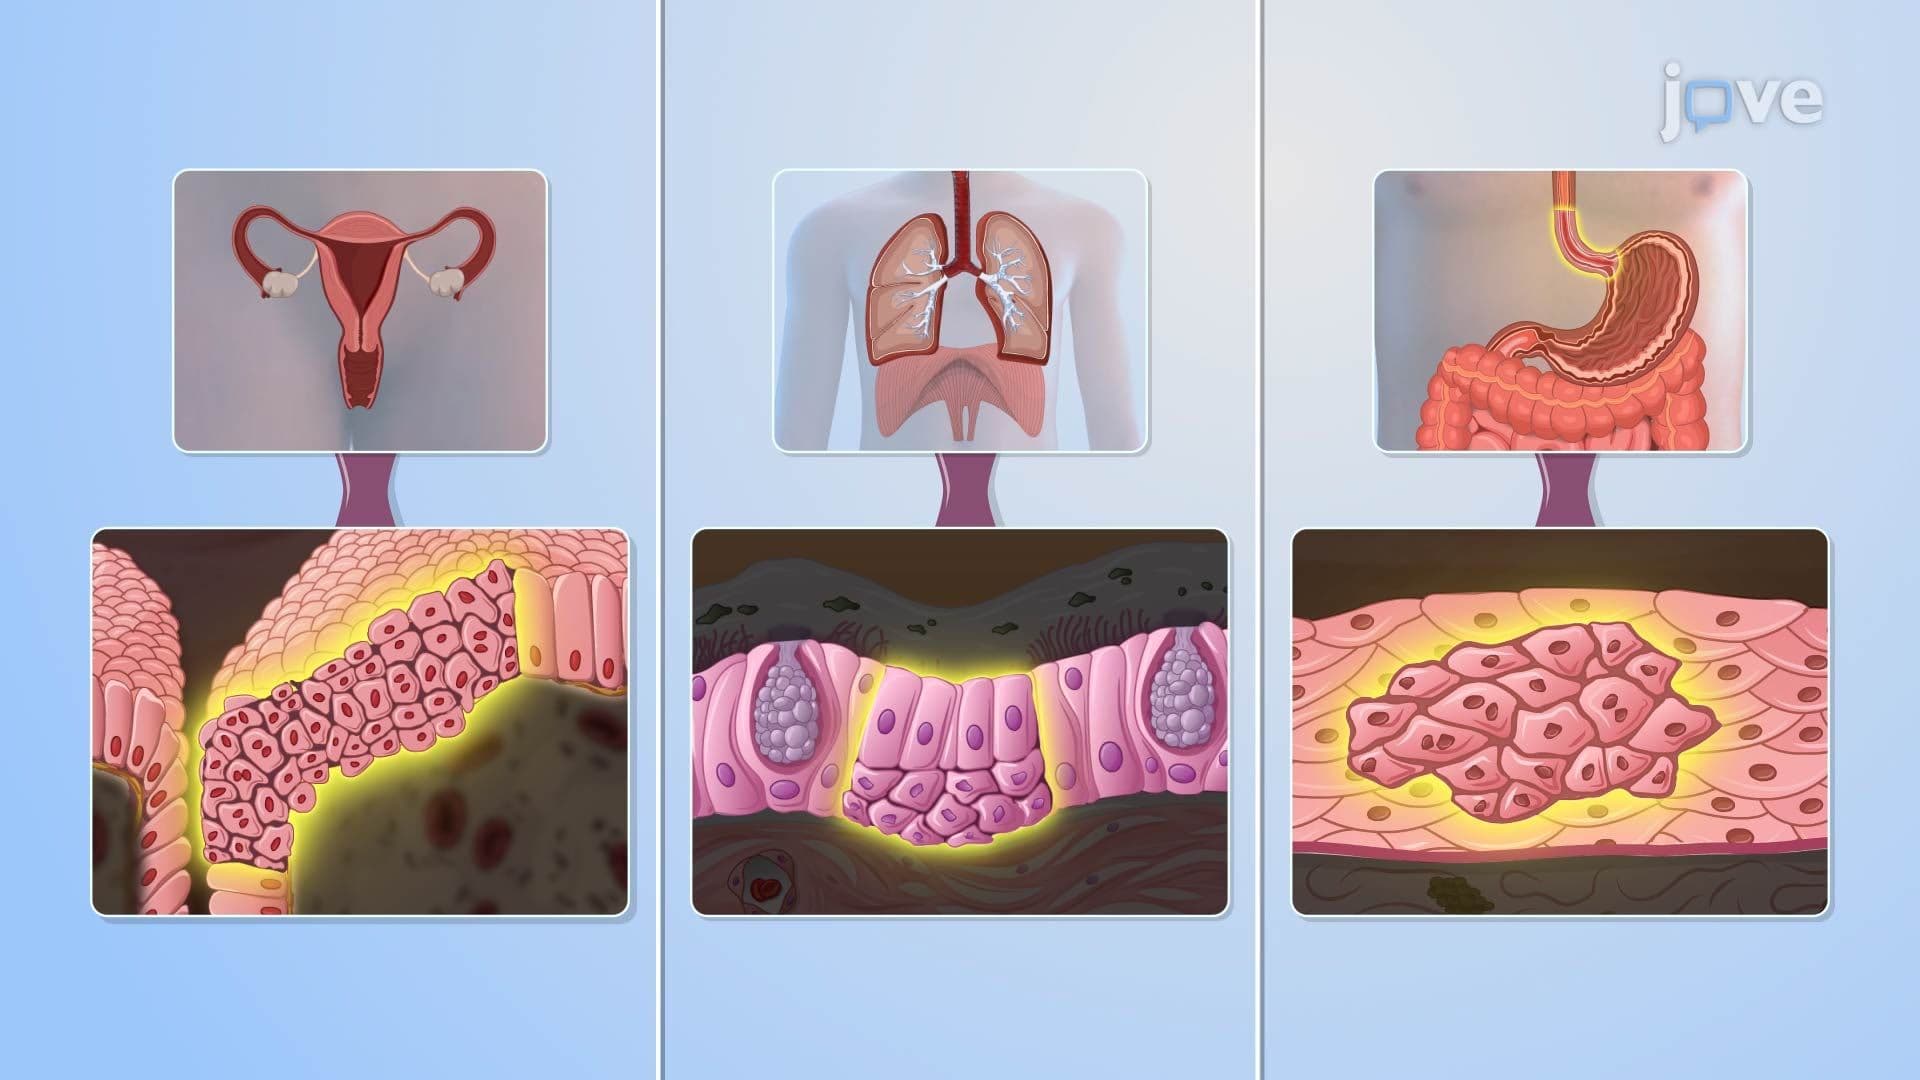
Cellular Adaptation IV: Dysplasia and Metaplasia