Related Experiment Video
Updated: Jun 5, 2026
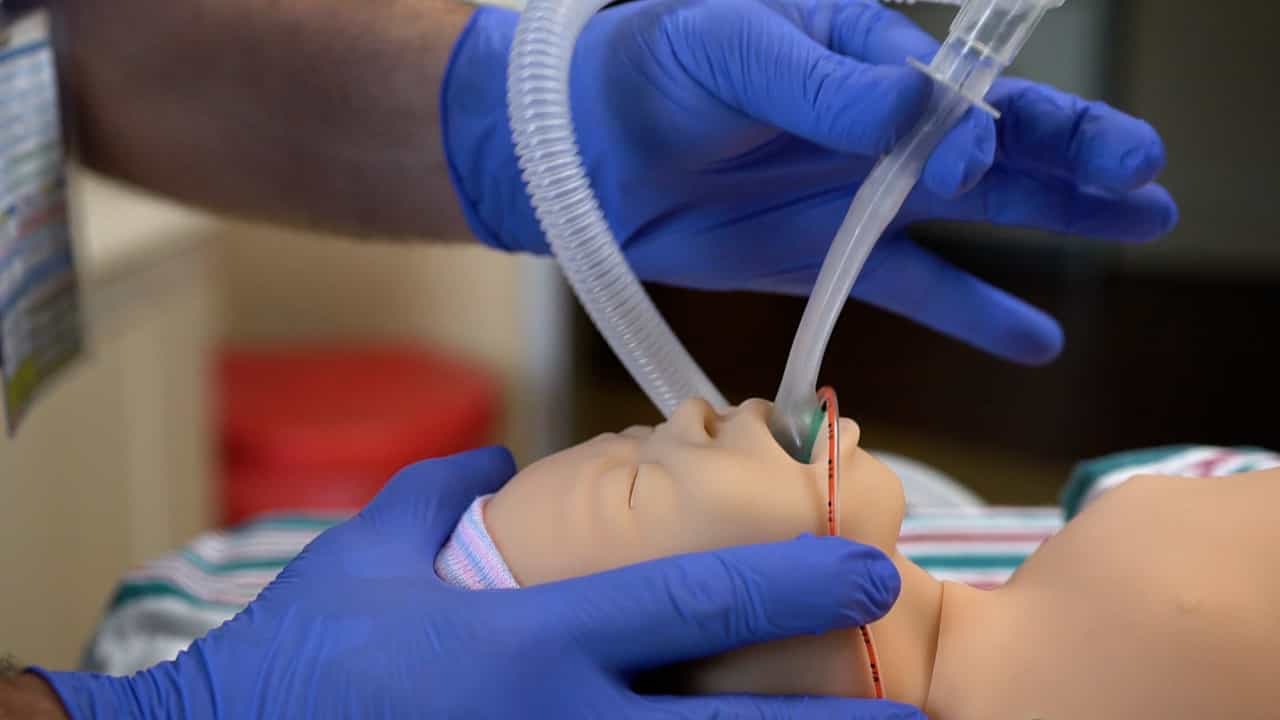

Laryngeal Mask Airway (LMA) Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway (SGA)
Published on: July 14, 2023
Use of laryngeal mask airway in pediatric adenotonsillectomy
Angela Peng1, Kelley M Dodson, Leroy R Thacker
1Department of Otolaryngology–Head and Neck Surgery, Virginia Commonwealth University, Richmond, USA.

Insights
Flexible laryngeal mask airway (LMA) is an effective alternative to endotracheal tube (ETT) for pediatric adenotonsillectomy, with similar laryngospasm rates. LMA use resulted in significantly shorter extubation times, though visualization and kinking require further study.
Area of Science:
- Anesthesiology
- Pediatric Surgery
- Airway Management
Background:
- Adenotonsillectomy is a common pediatric surgical procedure.
- Airway management during pediatric adenotonsillectomy typically involves either a laryngeal mask airway (LMA) or an endotracheal tube (ETT).
- Choosing the appropriate airway device is crucial for patient safety and procedural efficiency.
Purpose of the Study:
- To compare the efficacy and safety of flexible laryngeal mask airway (LMA) versus endotracheal tube (ETT) in pediatric adenotonsillectomy.
- To evaluate the incidence of laryngospasm and assess anesthesia, operative, and recovery times for both airway devices.
Main Methods:
- A prospective randomized trial was conducted with 131 children aged 2-12 years undergoing adenotonsillectomy.
- Participants were randomized to either LMA or ETT group, with a standardized anesthesia protocol.
- Primary outcome was laryngospasm; secondary outcomes included various time measurements.
Main Results:
- No significant difference in laryngospasm rates between LMA (12.5%) and ETT (9.6%) groups.
- Mean surgical times were comparable (33.35 min for LMA vs. 37.76 min for ETT).
- Time to extubation was significantly shorter with LMA (P = .01), but 10 cases required LMA to ETT conversion due to kinking or visualization issues.
Conclusions:
- Flexible LMA is an efficient alternative to ETT for pediatric adenotonsillectomy with comparable laryngospasm rates.
- LMA offers a significant advantage with shorter extubation times.
- Further research is necessary to address potential visualization and kinking challenges with LMAs in this population.
Objective:
To compare the use of flexible laryngeal mask airway (LMA) and endotracheal tube (ETT) in pediatric adenotonsillectomy.
Design:
Prospective randomized trial.
Setting:
Tertiary care hospital.
Patients:
One hundred thirty-one children (aged 2-12 years). Exclusion criteria were body mass index (calculated as the weight in kilograms divided by the height in meters squared) greater than 35 and craniofacial anomalies. Obstructive sleep apnea was the most common indication for surgery.
Intervention:
Children undergoing adenotonsillectomy were randomized to use of an LMA or ETT. A standardized anesthesia protocol was used.
Main Outcome Measures:
Primary outcome measure was laryngospasm. Secondary measures included anesthesia, operative, and recovery times.
Results:
Sixty children were randomized to the LMA group and 71 to the ETT group. There was no difference between groups with regard to age (P = .76), ethnicity (P = .75), body mass index (P = .99), or American Society of Anesthesiologists grade (P = .46). Incidence of postoperative laryngospasm between LMA (12.5%) and ETT (9.6%) was similar (P = .77). In 10 patients, the LMA was changed to ETT intraoperatively owing to tube kinking or difficulty with visualization. Mean (SD) surgical times for LMA and ETT groups were 33.35 (13.39) and 37.76 (18.26) minutes, respectively (P = .15). Time from surgery end to extubation was significantly shorter in patients who used LMA (P = .01) by 4.06 minutes. There were no differences (P = .49) in postanesthesia care unit recovery times.
Conclusions:
An LMA is an efficient alternative to ETT in pediatric adenotonsillectomy. When comparing LMA and ETT, there is no difference in rates of laryngospasm. Time to extubation is significantly shorter in patients using LMA. Before adopting the routine use of LMA in pediatric adenotonsillectomy, further study is needed to address visualization and kinking issues associated with this device.

Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:25
Suctioning the Oropharyngeal Airway
After assembling the equipment, the nurse should practice hand hygiene and don appropriate PPE according to infection control guidelines to avoid the...
 01:29
Suctioning the Nasopharyngeal Airway
Equipment Required
 01:23
Tracheostomy Suctioning II: Procedure
 01:26
Tracheostomy Suctioning I: Pre-Procedural Steps
Equipment Required
First, gather all necessary equipment: a sterile suction catheter, a sterile disposable container, sterile gloves, a towel or...