Related Experiment Video
Updated: Jun 1, 2026
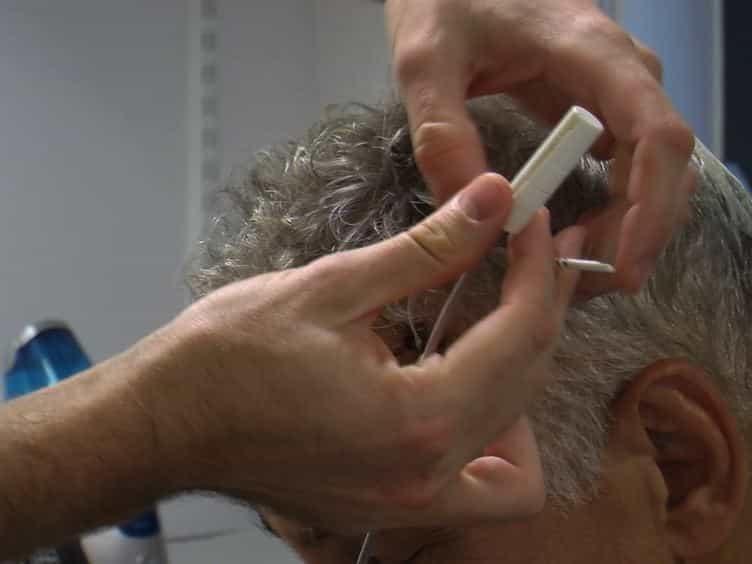
Controlling Parkinson's Disease With Adaptive Deep Brain Stimulation
Published on: July 16, 2014
Motor features and response to oral levodopa in patients with Parkinson's disease under continuous dopaminergic
A E Elia1, C Dollenz, P Soliveri
1Istituto Neurologico Carlo Besta, Milan, Italy.

Background:
Subthalamic nucleus deep brain stimulation (STN DBS) and continuous dopaminergic infusions (jejunal levodopa or subcutaneous apomorphine) are indicated in complicated Parkinson's disease (PD), although it remains unsettled how they compare to each other.
Methods:
We investigated the daytime motor condition in patients with advanced PD under monotherapy with jejunal levodopa, subcutaneous apomorphine, or STN DBS and also measured the motor changes produced by an additional standard morning dose of levodopa. Motor performance was assessed with the UPDRS-III, hand taps, the AIMS dyskinesia score and patients' diaries. Outcome measures were time to best motor 'on' after start of morning treatment, daytime variability of motor condition, motor scores.
Results:
The time to 'on' was longest in the jejunal levodopa group. DBS and jejunal levodopa treatments produced stable motor conditions without appreciable 'off' episodes. Continuous apomorphine infusion was associated with the worst motor scores (UPDRS-III and taps) and the most frequent off-states. Jejunal levodopa infusion was associated with the highest AIMS scores. Addition of a levodopa dose produced shortening of time to 'on' and a transient motor improvement in the jejunal levodopa group without increase in dyskinesias; in the DBS and apomorphine groups, there was an increase in dyskinesias without changes in UPDRS-III or taps.
Conclusions:
STN DBS provided adequate trade-off between motor improvement and dyskinesia control, although dyskinesias could be elicited by adding oral levodopa. Jejunal levodopa infusion produced adequate motor improvement with slow time to 'on' and moderate dyskinesias. Apomorphine infusion produced insufficient motor control and negligible dyskinesias.
More Related Videos


Related Concept Videos
 01:24
Parkinson's Disease: Treatment
Parkinson's Disease is primarily a result of the loss of dopaminergic neurons in the substantia nigra pars compacta. The cornerstone of its...
 01:15
Parkinson's Disease: Overview
 01:20
Motor Unit Stimulation
The latent period of contraction marks the onset of excitation-contraction coupling, when the action potential propagates across the sarcolemma, preparing the muscle fibers for contraction. As the fibers enter the contraction phase, the...
 01:24
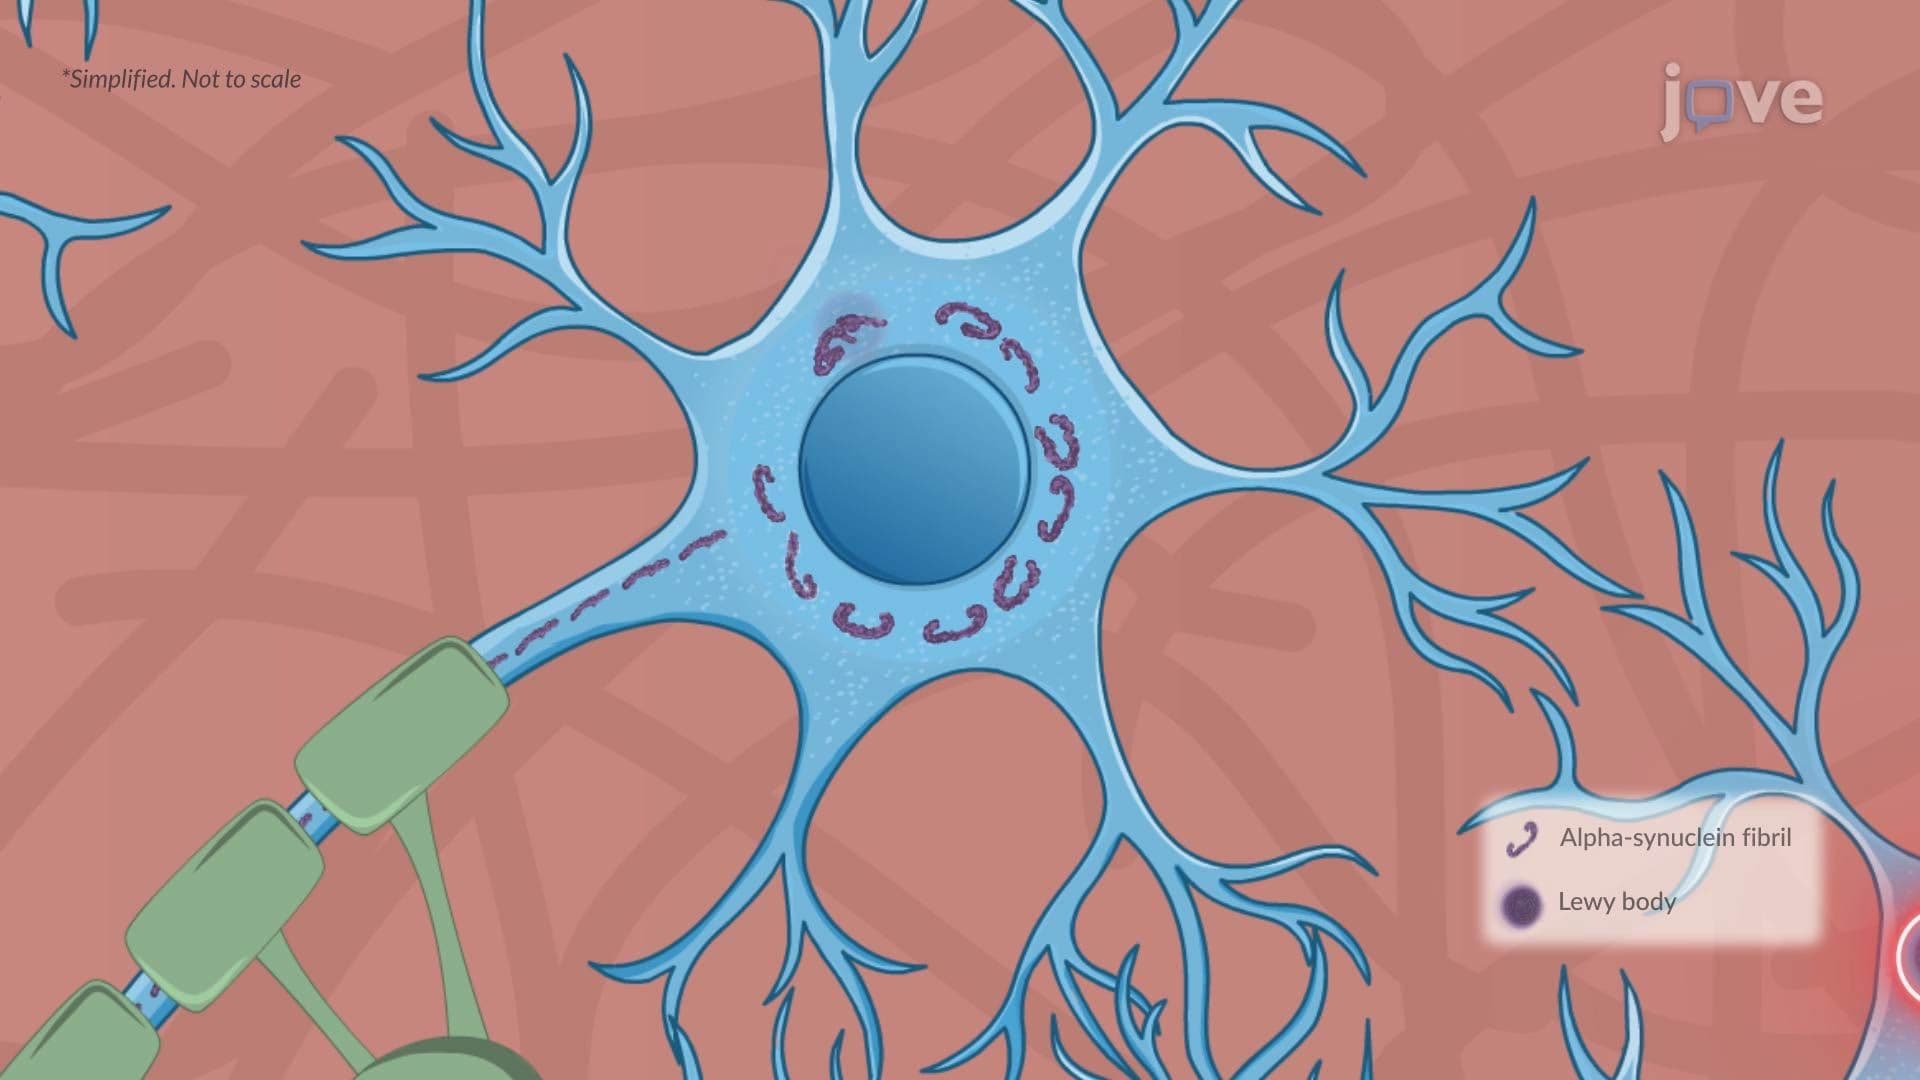
Parkinson Disease ll: Pathophysiology
 01:24
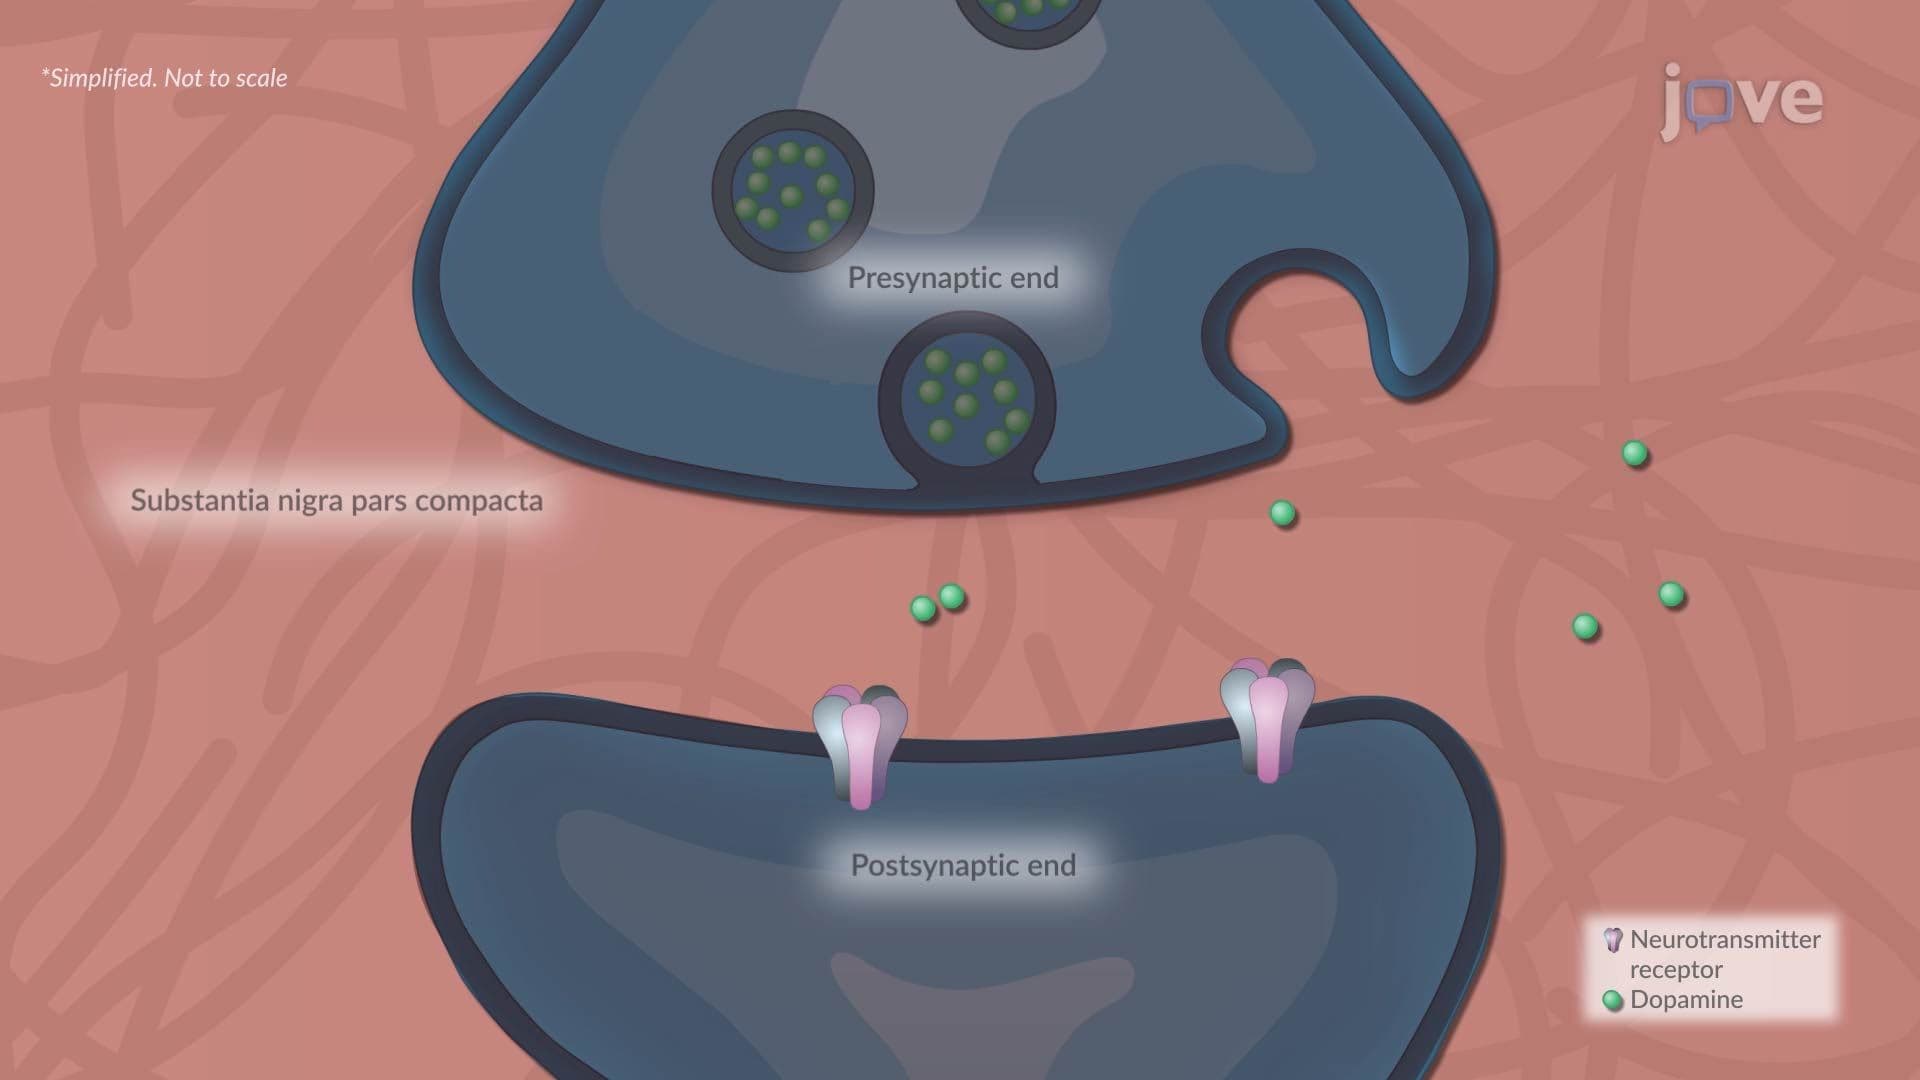
Parkinson Disease l: Introduction
 01:11
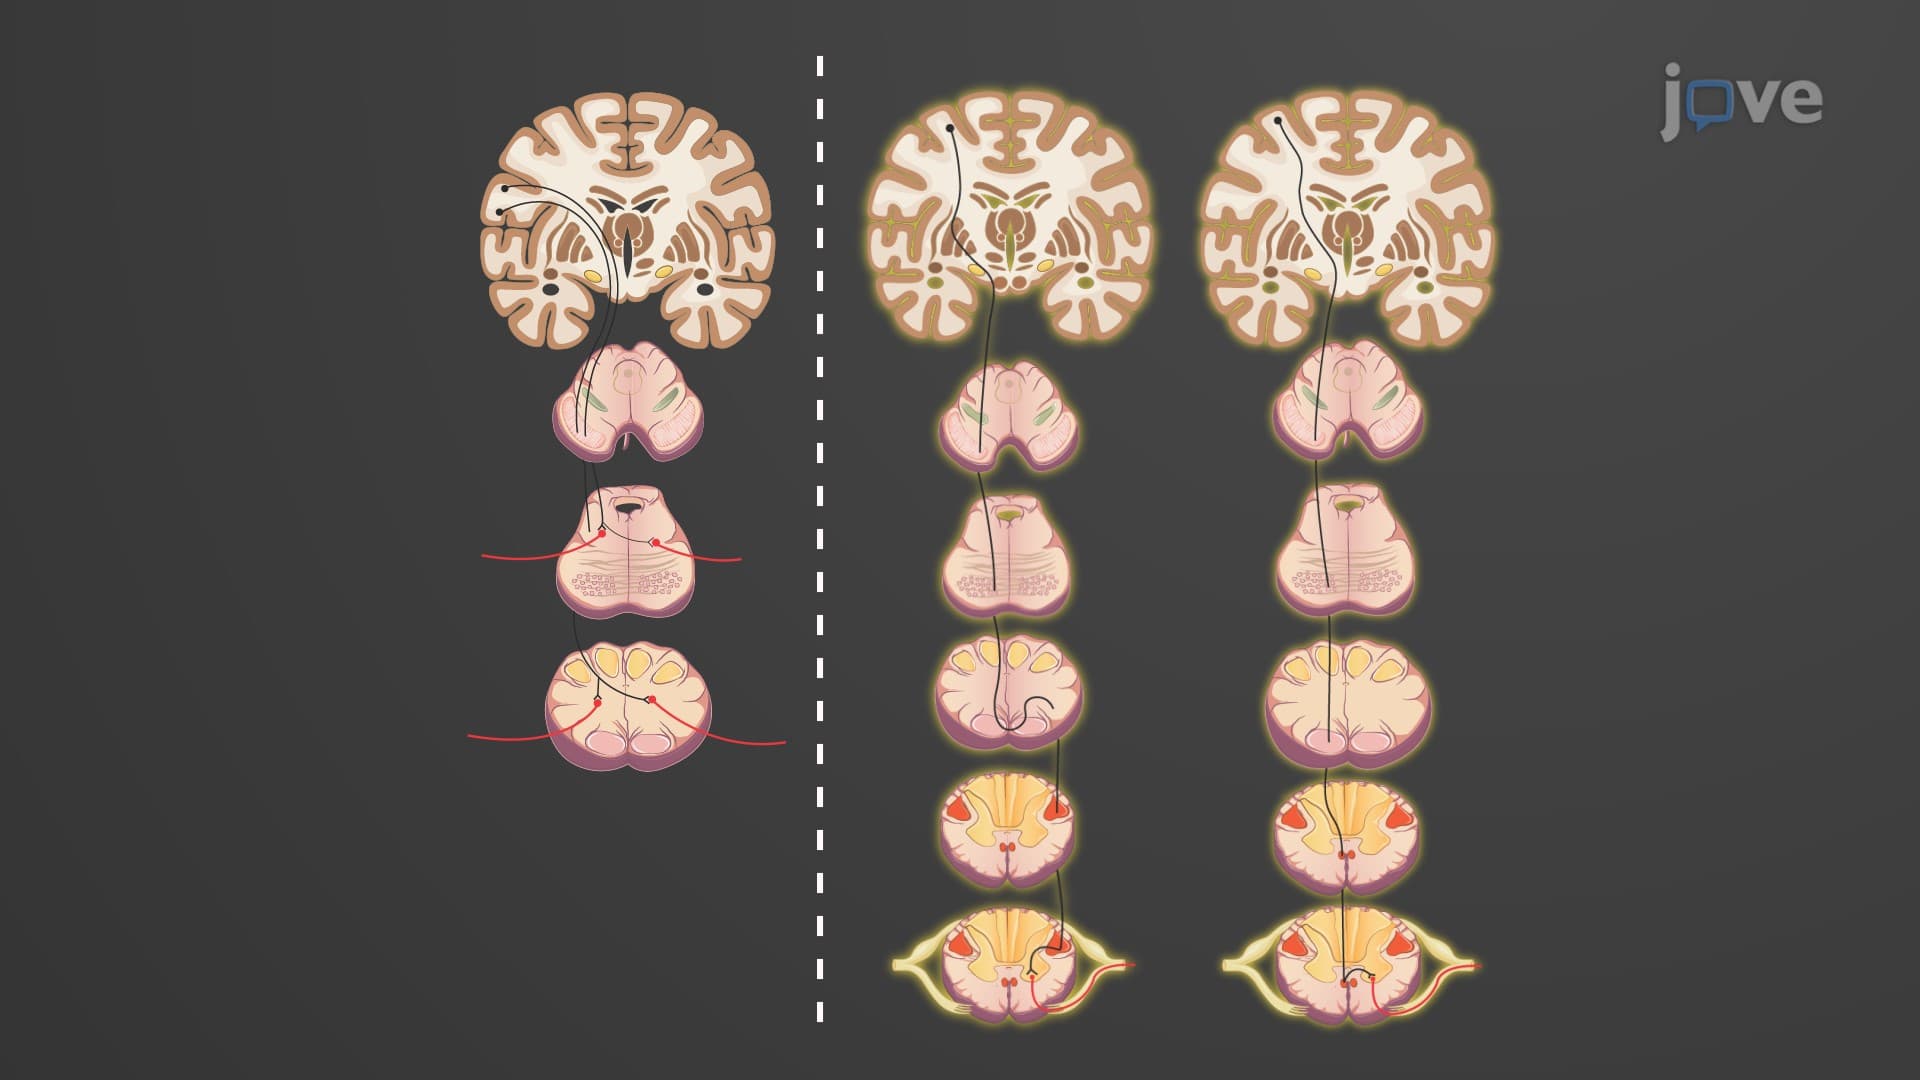
Direct Motor Pathways
The corticospinal tract is responsible for the voluntary movement of the limbs and trunk. It originates in the cerebral cortex of the brain and descends through the cerebrum's internal capsule and the...