Related Experiment Video
Updated: May 28, 2026


High-Resolution Endocardial and Epicardial Optical Mapping in a Sheep Model of Stretch-Induced Atrial Fibrillation
Published on: July 29, 2011
Waveform optimization for internal cardioversion of atrial fibrillation
Vivek Kodoth1, Noel C Castro, Ben M Glover
1The Heart Centre, Royal Victoria Hospital, Belfast, Northern Ireland.

Introduction:
A novel atrial defibrillator was developed at the Royal Victoria Hospital in collaboration with the Nanotechnology and Integrated Bio-Engineering Centre, University of Ulster. This device is powered by an external pulse of radiofrequency energy and designed to cardiovert using low-tilt monophasic waveform (LTMW) and low-tilt biphasic waveform (LTBW), 12 milliseconds pulse width. This study compared the safety and efficacy of LTMW with LTBW for transvenous cardioversion of atrial fibrillation (AF).
Methods:
Patients were anticoagulated with warfarin to maintain International Normalized Ratio between 2 and 3 for 4 weeks prior cardioversion. Warfarin international normalized ratio level was maintained in between 2 and 3 for 4 weeks prior cardioversion. St Jude's defibrillating catheter was positioned in the distal coronary sinus and right atrium and connected to the defibrillator via a junction box. After a test shock using a dummy load, the patient was cardioverted in a step-up progression from 50 to 300 V. Shock success was defined as return of sinus rhythm for 30 seconds or more. If cardioversion was unsuccessful at peak voltage, the patient was crossed over to the other arm of the waveform type and cardioverted at peak voltage.
Results:
Thirty patients were randomized equally to LTBW and LTMW (15 each). Seven out of 15 patients (46%) cardioverted to sinus rhythm with LTBW, and 1 (6%) of 15, with LTMW (P = .035). Including crossover patients, 14 patients (46%) converted to sinus rhythm. After crossover, 4 patients were cardioverted with LTBW and 2 with LTMW. Overall mean voltage, current, and energy used for cardioversion were 270.53 ± 35.96 V, 3.68 ± 0.80 A, and 9.12 ± 3.73 J, respectively, and intracardiac impedance was 70.82 ± 13.46 Ω. For patients who were successfully cardioverted, mean voltage, current, energy, and intracardiac impedance were 268.28 ± 42.41 V, 3.52 ± 0.63 A, 8.51 ± 3.16 J, and 73.92 ± 12.01 Ω. There were no major adverse complications during the study. Cardiac markers measured postcardioversion were unremarkable.
Conclusion:
Low-tilt biphasic waveform was more efficacious for low-energy transvenous cardioversion of AF. A significant proportion of patients were successfully cardioverted to sinus rhythm with low energy. Radiofrequency-powered defibrillation can be safely used for transvenous cardioversion of AF.


Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:29
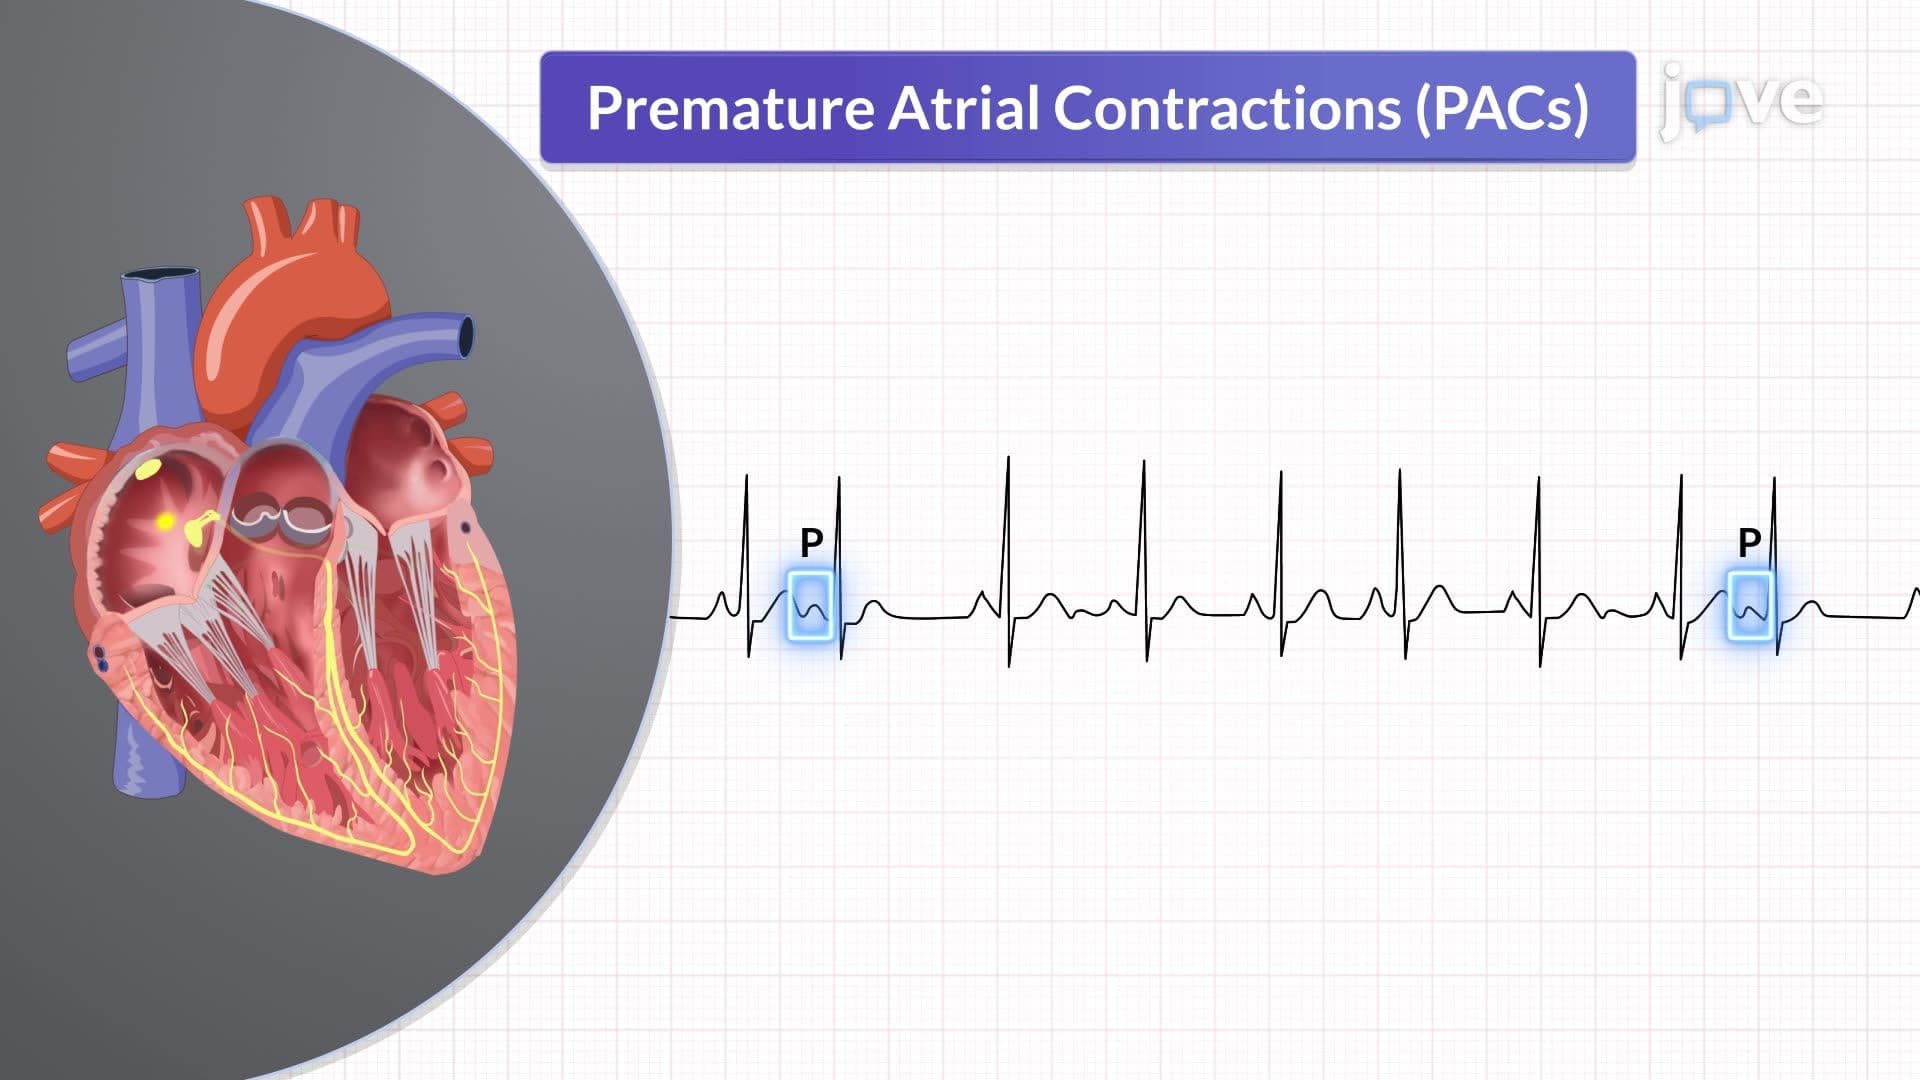
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:28
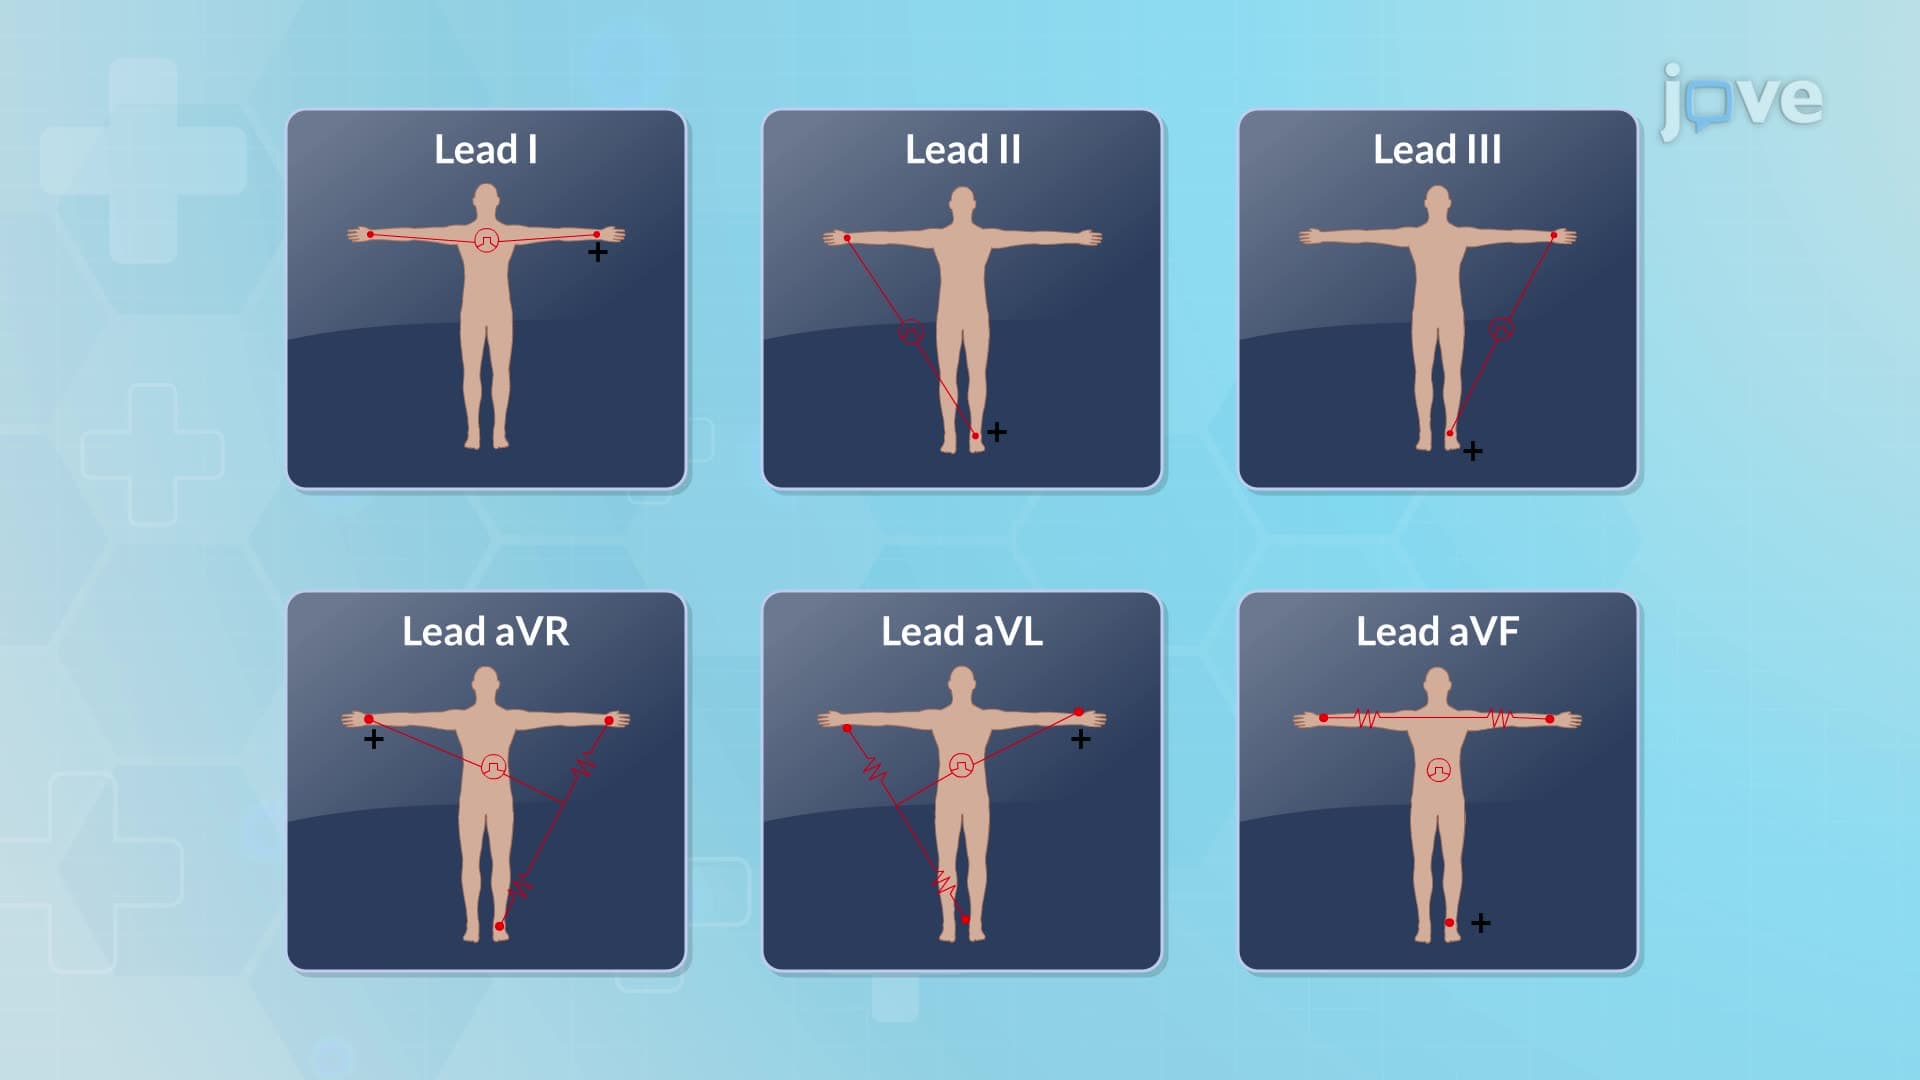
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin to...