Related Experiment Video
Updated: May 25, 2026
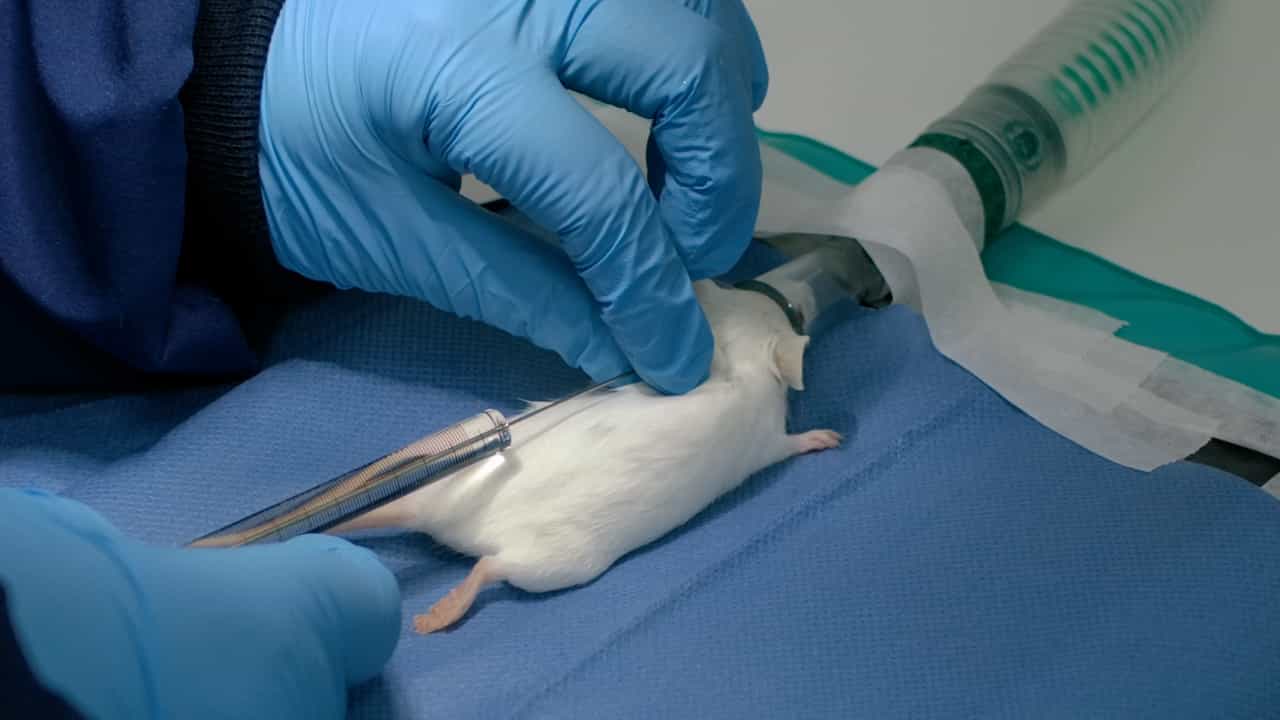

Combined In Vivo Electroporation and Short-Term Reinnervation of the Cranial Levator Auris Longus Skeletal Muscle
Published on: November 1, 2024
[The pathophysiology and treatment of autoimmune neuromuscular junction diseases]
1Department of Clinical Neuroscience and Neurology, Graduate School of Biomedical Sciences, Nagasaki University.

Abstract:
The neuromuscular junction lacks the protection of the blood-nerve barrier and is vulnerable to antibody-mediated disorders. Myasthenia gravis (MG) is caused by the failure of neuromuscular transmission mediated by autoantibodies against acetylcholine receptors (AChR) and muscle-specific receptor tyrosine kinase (MuSK)/LDL-receptor related protein 4 which are AChR-associated transmembrane post-synaptic proteins involved in AChR aggregation. The seropositivity rates for AChR positive and MuSK positive MG in Japan are 80-85% and 5-10%/less than 1%,respectively. The incidence of late-onset MG, defined as onset after age 50 years, has been increasing worldwide. A nationwide epidemiological survey in Japan also revealed that the rates of late-onset MG had increased from 20% in 1987 to 42% in 2006. In 2010, a guideline for standard treatments of late-onset MG was published by the Japanese Society of Neurological Therapeutics. Lambert-Eaton myasthenic syndrome (LEMS) is an autoimmune disease of the neuromuscular junction and approximately 60% of LEMS patients have a tumor, mostly small cell lung cancer (SCLC), as a paraneoplastic neurological syndrome. The clinical pictures of Japanese LEMS patients are as follows; male dominant sex ratio (3 : 1), mean age 62 years (17-80 years), 61% of LEMS have SCLC, and the remaining are without cancer. In less than 10% of cases there are signs of cerebellar dysfunctions (paraneoplastic cerebellar degeneration with LEMS; PCD-LEMS) as well, often associated with SCLC. Most patients benefit from 3, 4-diaminopyridine plus pyridostigmine. In paraneoplastic LEMS, treatment of the tumor often results in neurological improvement. In non-paraneoplastic LEMS, prednisone alone or combined with immunosuppressants are treatment options. In both MG and LEMS, where weakness is severe, plasma exchange or intravenous immunoglobulin treatment may provide short-term benefit.
More Related Videos
 11:03
Characterization of Neuromuscular Junctions in Mice by Combined Confocal and Super-Resolution Microscopy
Published on: December 8, 2021
 12:18
The Neuromuscular Junction: Measuring Synapse Size, Fragmentation and Changes in Synaptic Protein Density Using Confocal Fluorescence Microscopy
Published on: December 26, 2014
Related Concept Videos
 01:22
Myasthenia Gravis ll: Pathophysiology
 01:20
Myasthenia Gravis: Overview and Treatment
These antibodies interfere with the function of the nicotinic receptors in three ways: by binding to the receptor and disrupting acetylcholine binding; by causing cross-linking of receptors which leads...
 01:29
Neuromuscular Junction And Blockade
 01:19
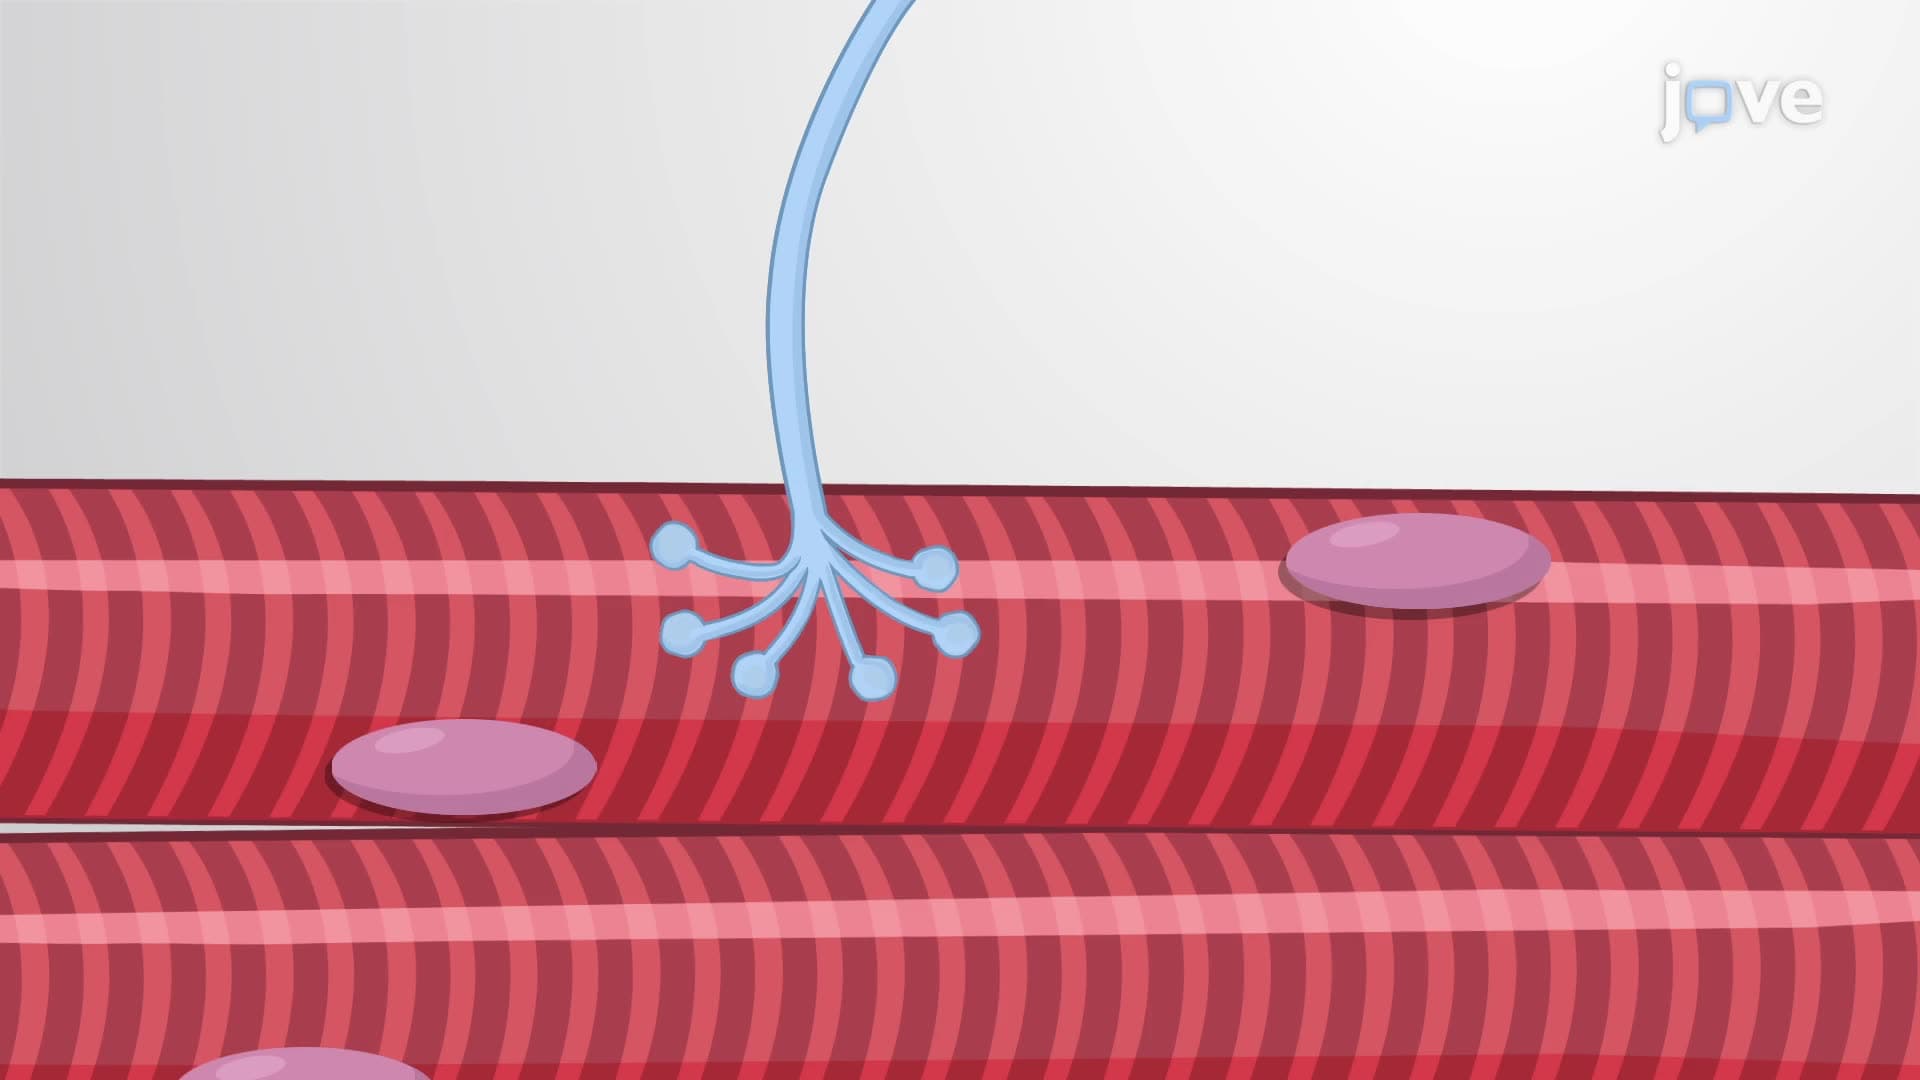
The Neuromuscular Junction
 01:26
Chemical Synapses
Because chemical synapses depend on the release of neurotransmitter molecules from synaptic vesicles to pass on their signal, there is an approximately one millisecond delay between when the axon potential reaches the presynaptic terminal and when the neurotransmitter leads to opening of postsynaptic ion channels. Additionally, this signaling is...
01:26Chemical Synapses
Because chemical synapses depend on the release of neurotransmitter molecules from synaptic vesicles to pass on their signal, there is an approximately one millisecond delay between when the axon potential reaches the presynaptic terminal and when the neurotransmitter leads to opening of postsynaptic ion channels. Additionally, this signaling is...