Related Experiment Video
Updated: May 23, 2026


Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
Left ventricular lead position for cardiac resynchronization: a comprehensive cinegraphic, echocardiographic,
Ying-Xue Dong1, Brian D Powell, Samuel J Asirvatham
1Division of Cardiovascular Diseases, Mayo Clinic, 200 First Street SW, Rochester, MN 55905, USA.

Insights
Optimal cardiac resynchronization therapy (CRT) outcomes depend on left ventricular (LV) lead placement. Anterolateral (AL) and posterolateral (PL) LV lead positions show superior clinical and survival benefits compared to anterior placements.
Area of Science:
- Cardiology
- Electrophysiology
- Medical Devices
Background:
- Cardiac resynchronization therapy (CRT) is a treatment for heart failure.
- Left ventricular (LV) lead placement is crucial for CRT efficacy.
- The lateral LV wall has been considered optimal for LV lead placement.
Purpose of the Study:
- To evaluate the impact of LV lead location on clinical and survival outcomes in CRT recipients.
- To compare the effectiveness of different LV lead positions (anterior, anterolateral, posterolateral, posterior).
Main Methods:
- Retrospective analysis of 457 CRT recipients (pacemaker or defibrillator) implanted between 2002-2008.
- LV lead positions categorized using echocardiographic 16-segment analysis.
- Clinical outcomes (NYHA class) and survival rates were compared across lead locations.
Main Results:
- Anterolateral (AL) and posterolateral (PL) LV lead positions showed significantly greater improvement in NYHA class compared to the anterior position.
- A trend towards improved LV ejection fraction was observed in AL and PL positions versus the anterior position.
- Four-year survival estimates were highest for AL (72%) and posterior (72%) locations, followed by PL (62%), and lowest for the anterior (48%) location (P=0.003).
Conclusions:
- All LV lead positions provide some benefit to CRT recipients.
- Anterolateral (AL) and posterolateral (PL) LV lead placements are more advantageous for achieving optimal CRT benefits than anterior placements.
Aims:
We sought to determine the clinical and survival outcomes of cardiac resynchronization therapy (CRT) associated with left ventricular (LV) lead location. The lateral left ventricle has been considered the optimal LV lead location for CRT.
Methods And Results:
Left ventricular lead cinegrams taken in 30° right and left anterior oblique views were evaluated in 457 recipients of CRT with a pacemaker or a defibrillator from 1 January 2002 to 31 December 2008 in this retrospective study. Left ventricular lead placement was prioritized at implantation into posterolateral (PL), anterolateral (AL), middle cardiac, and anterointerventricular coronary veins. Using echocardiographic LV 16-segment analysis, we grouped the leads as anterior, AL, PL, and posterior locations. New York Heart Association (NYHA) class and echocardiography were assessed before and after CRT. Clinical and survival outcomes after CRT were compared among the four LV lead locations. Patient baseline demographic characteristics were similar among these four groups. Improvement in NYHA class was significantly greater in the AL (P= 0.04) and PL (P= 0.03) locations than in the anterior location. There was a tendency for greater improvement in LV ejection fraction among the AL (P= 0.11) and PL (P= 0.08) locations than the anterior location. Kaplan-Meier survival estimate at 4 years varied for location: AL, 72%; anterior, 48%; PL, 62%; and posterior, 72% (P= 0.003).
Conclusion:
Cardiac resynchronization therapy recipients are profiting from all lead positions. However, LV lead placed in the AL and PL positions is more preferential for achieving optimal CRT benefit than leads placed in the anterior position.
More Related Videos
 10:17
Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
Related Concept Videos
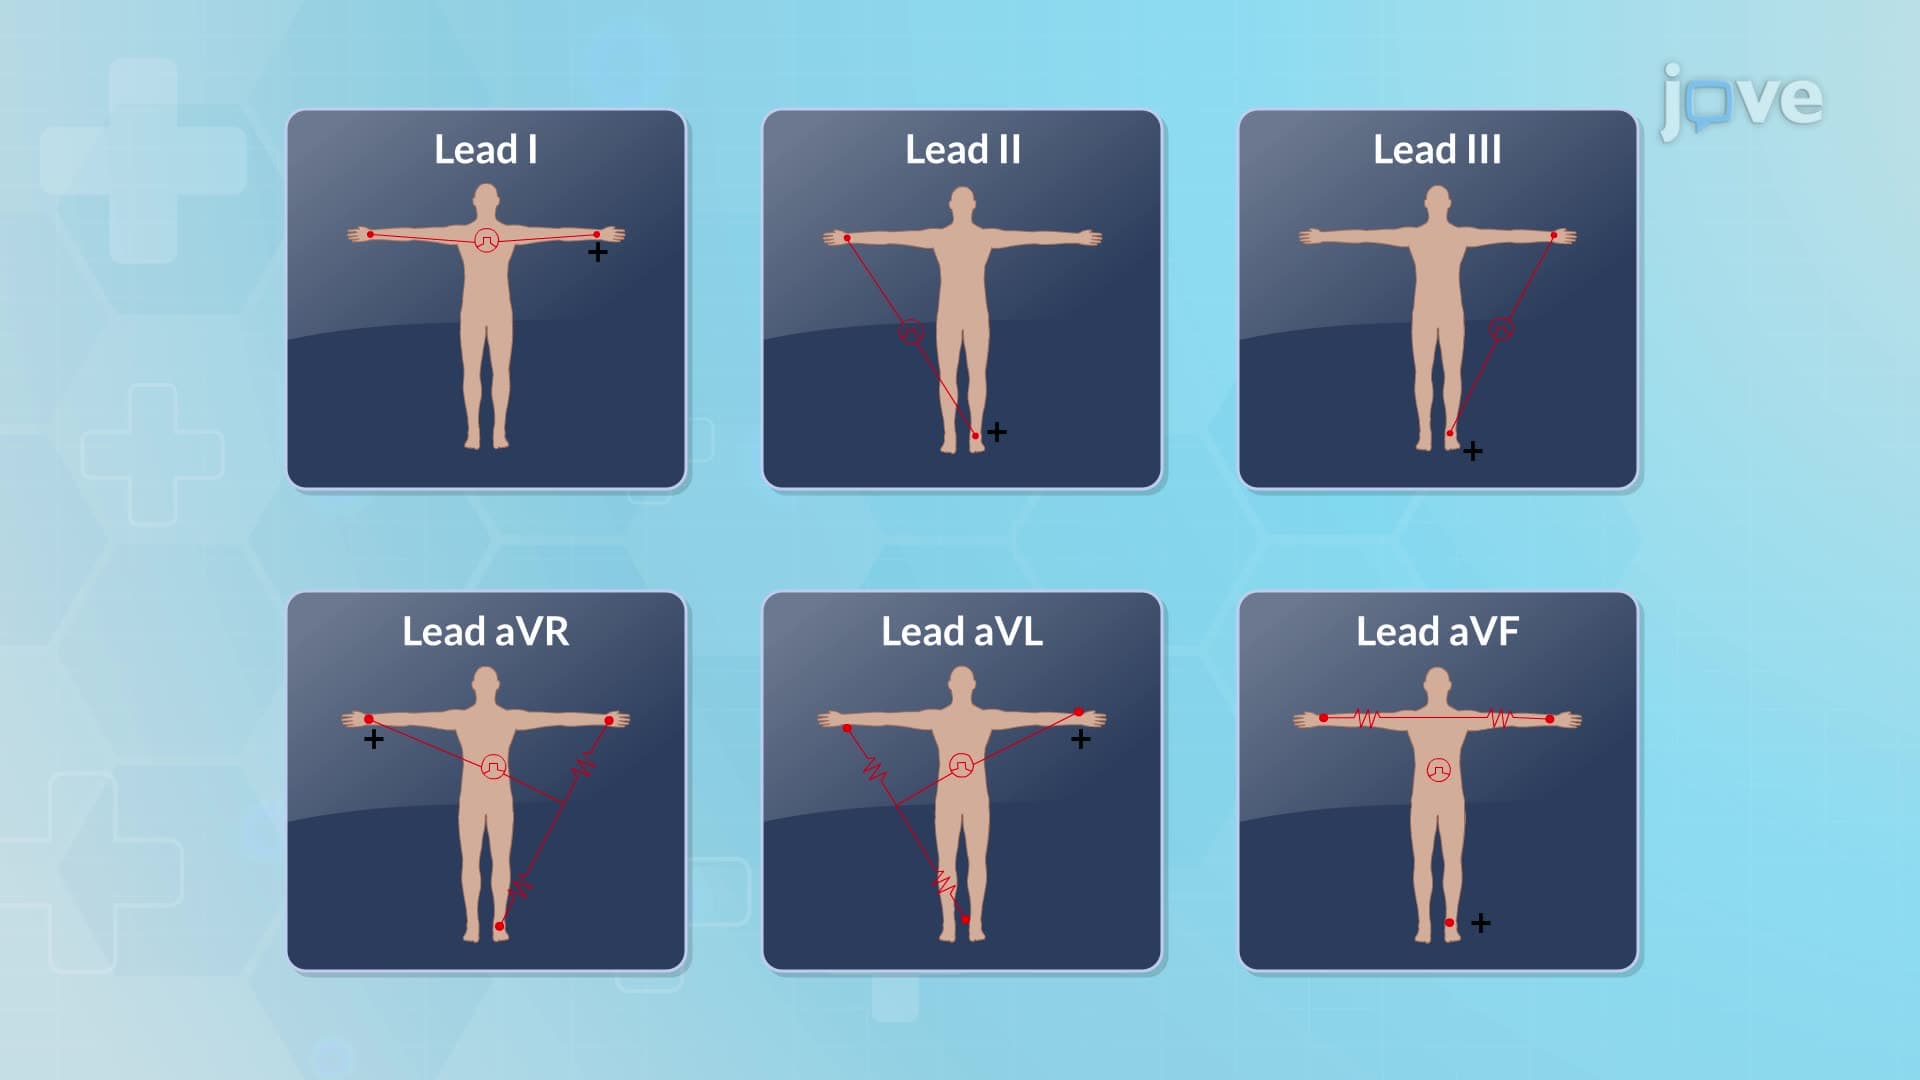 01:28
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin to...
 01:29
Cardiomyopathy V: Interprofessional Care