Related Experiment Video
Updated: May 22, 2026
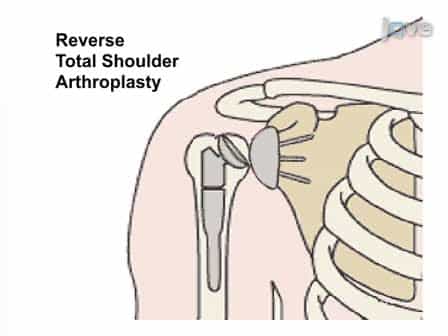
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Surgical treatment options for the young and active middle-aged patient with glenohumeral arthritis
Sanjeev Bhatia1, Andrew Hsu, Emery C Lin
1Division of Sports Medicine, Department of Orthopaedic Surgery, Rush University Medical Center, 1611 W. Harrison Street, Suite No. 300, Chicago, IL 60612, USA.

Abstract:
The diagnosis and treatment of symptomatic chondral lesions in young and active middle-aged patients continues to be a challenging issue. Surgeons must differentiate between incidental chondral lesions from symptomatic pathology that is responsible for the patient's pain. A thorough history, physical examination, and imaging work up is necessary and often results in a diagnosis of exclusion that is verified on arthroscopy. Treatment of symptomatic glenohumeral chondral lesions depends on several factors including the patient's age, occupation, comorbidities, activity level, degree of injury and concomitant shoulder pathology. Furthermore, the size, depth, and location of symptomatic cartilaginous injury should be carefully considered. Patients with lower functional demands may experience success with nonoperative measures such as injection or anti-inflammatory pharmacotherapy. When conservative management fails, surgical options are broadly classified into palliative, reparative, restorative, and reconstructive techniques. Patients with lower functional demands and smaller lesions are best suited for simpler, lower morbidity palliative procedures such as debridement (chondroplasty) and cartilage reparative techniques (microfracture). Those with higher functional demands and large glenohumeral defects will usually benefit more from restorative techniques including autograft or allograft osteochondral transfers and autologous chondrocyte implantation (ACI). Reconstructive surgical options are best suited for patients with bipolar lesions.
