Related Experiment Video
Updated: May 22, 2026
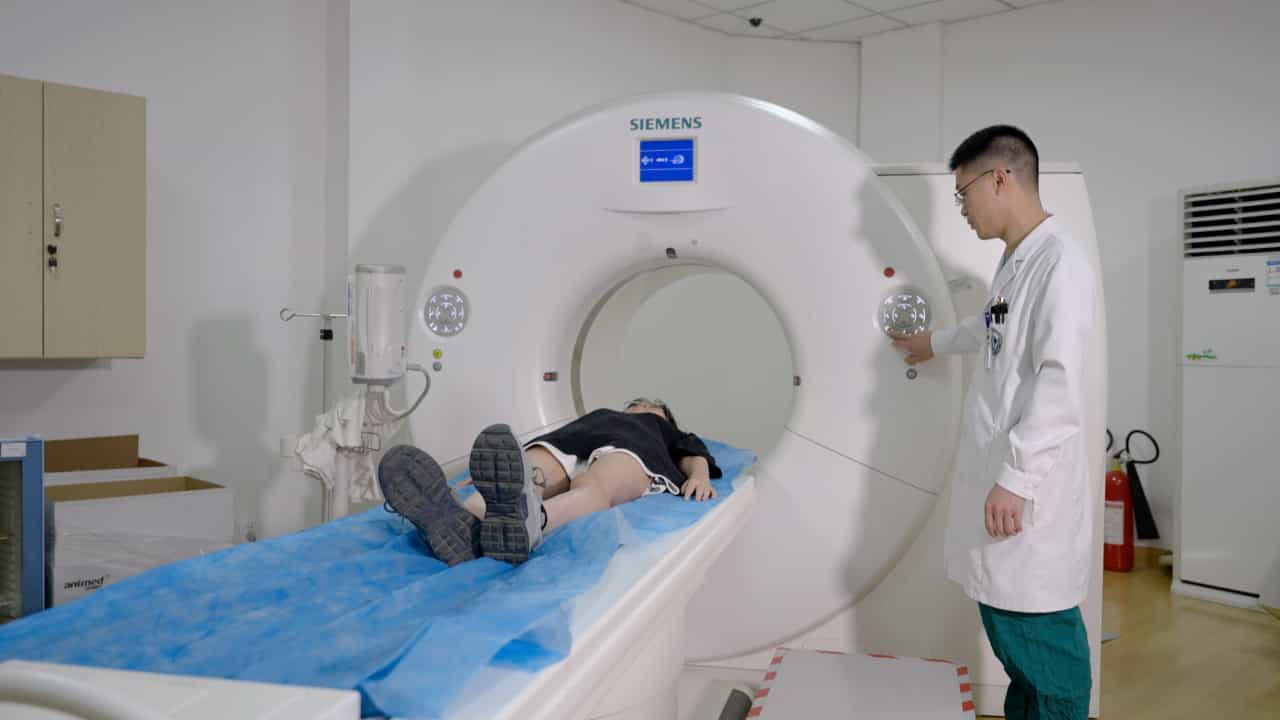
Computer-Aided Three-Dimensional Visualization in the Treatment of Locally Advanced Thyroid Cancer
Published on: June 9, 2023
Simulation of post-thyroidectomy treatment alternatives for triiodothyronine or thyroxine replacement in pediatric
Rotem Ben-Shachar1, Marisa Eisenberg, Stephen A Huang
1Biocybernetics Laboratory, Department of Computational & Systems Biology, University of California-Los Angeles, CA, USA.

Background:
As in adults, thyroidectomy in pediatric patients with differentiated thyroid cancer is often followed by (131)I remnant ablation. A standard protocol is to give normalizing oral thyroxine (T(4)) or triiodothyronine (T(3)) after surgery and then withdraw it for 2 to 6 weeks. Thyroid remnants or metastases are treated most effectively when serum thyrotropin (TSH) is high, but prolonged withdrawals should be avoided to minimize hypothyroid morbidity.
Methods:
A published feedback control system model of adult human thyroid hormone regulation was modified for children using pediatric T(4) kinetic data. The child model was developed from data for patients ranging from 3 to 9 years old. We simulated a range of T(4) and T(3) replacement protocols for children, exploring alternative regimens for minimizing the withdrawal period, while maintaining normal or suppressed TSH during replacement. The results are presented with the intent of providing a quantitative basis to guide further studies of pediatric treatment options. Replacement was simulated for up to 3 weeks post-thyroidectomy, followed by various withdrawal periods. T(4) vs. T(3) replacement, remnant size, dose size, and dose frequency were tested for effects on the time for TSH to reach 25 mU/L (withdrawal period).
Results:
For both T(3) and T(4) replacement, higher doses were associated with longer withdrawal periods. T(3) replacement yielded shorter withdrawal periods than T(4) replacement (up to 3.5 days versus 7-10 days). Higher than normal serum T(3) concentrations were required to normalize or suppress TSH during T(3) monotherapy, but not T(4) monotherapy. Larger remnant sizes resulted in longer withdrawal periods if T(4) replacement was used, but had little effect for T(3) replacement.
Conclusions:
T(3) replacement yielded withdrawal periods about half those for T(4) replacement. Higher than normal hormone levels under T(3) monotherapy can be partially alleviated by more frequent, smaller doses (e.g., twice a day). LT(4) may be the preferred option for most children, given the convenience of single daily dosing and familiarity of pediatric endocrinologists with its administration. Remnant effects on withdrawal period highlight the importance of minimizing remnant size.

Related Concept Videos
 01:20
Synthesis and Regulation of Thyroid Hormones
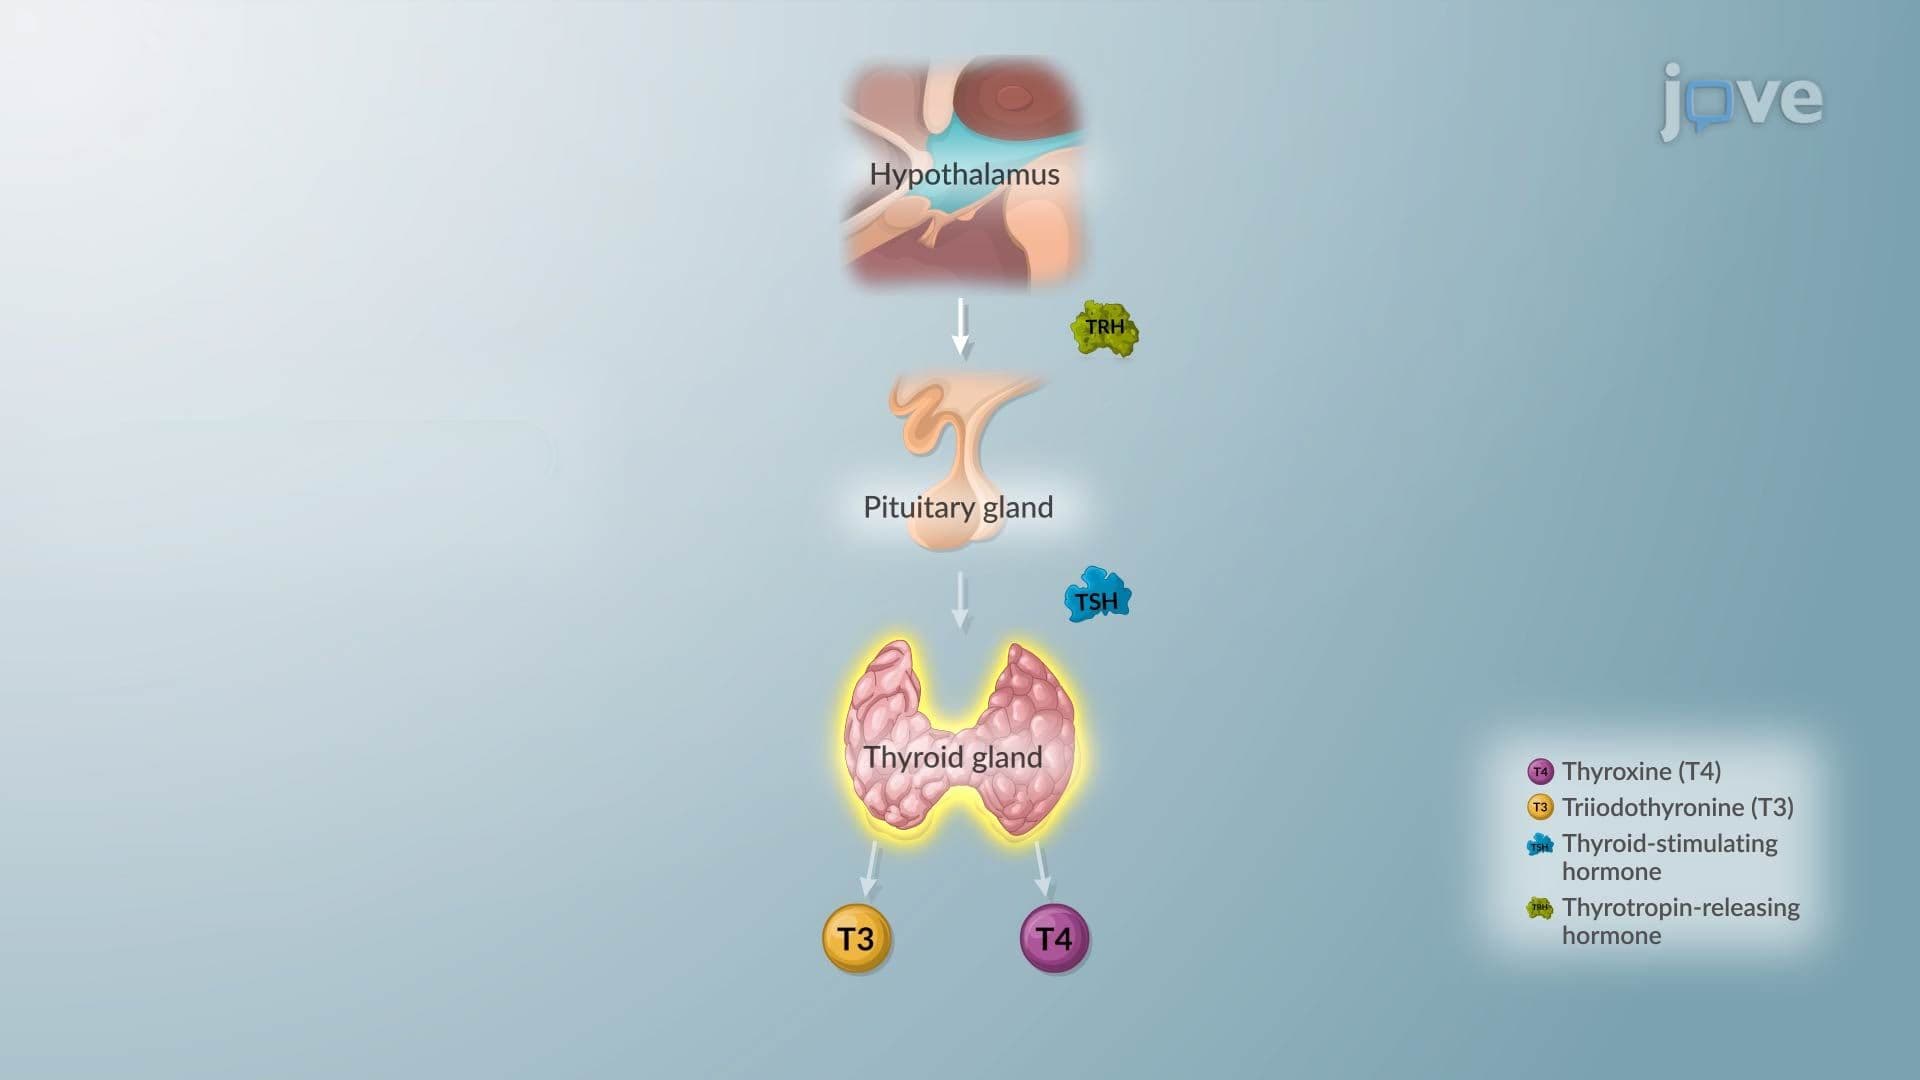
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology