Related Experiment Video
Updated: May 22, 2026

Clinical Efficacy of Ultrasound-Assisted Scoliosis-Specific Exercise in Mild-Grade Adolescent Idiopathic Scoliosis
Published on: December 2, 2025
Scoliosis associated with airflow obstruction due to endothoracic vertebral hump
Kenyu Ito1, Noriaki Kawakami, Kazuyoshi Miyasaka
1Department of Orthopaedic Surgery and Spine Center, Meijo Hospital, Nagoya, Japan.

Study Design:
A retrospective clinical study of scoliosis-associated airflow obstruction due to endothoracic vertebral hump.
Objective:
The purpose of this study was to evaluate and present anatomical features of patients with scoliosis who showed airflow obstruction caused by endothoracic vertebral hump.
Summary Of Background Data:
It is well known that severe scoliosis causes airflow restriction due to thoracic cage deformity. There have been few reports of clinical data and anatomical features on scoliosis associated with airflow obstruction due to endothoracic vertebral hump.
Methods:
The subjects were 6 patients. The diagnoses were idiopathic scoliosis in 3 patients, symptomatic scoliosis in 2 patients, and thoracogenic scoliosis in 1 patient. The radiological outcome, comorbidities, pre- and postoperative respiratory function, and surgical complication were analyzed.
Results:
Four patients had preoperative atelectasis on the convex side of the lower lobe and improved after the operations. All patients showed main thoracic curves and their apex was located at T7-T9. All patients had lordoscoliosis except 1, who demonstrated kyphosing scoliosis. The correction rate was 78% (62.8%-83.5%). Preoperative thoracic lordosis within the range of -5° to -47° was postoperatively corrected to a substantially normal kyphosis within the range of 9° to 24°. The average vital capacity, percent VC improved from 0.72 L (0.33-1.17 L) to 1.21 L (0.82-1.71 L) and 45.5% (37.3%- 50.8%) to 63.7% (41.0%-88.6%) relatively. Spine Penetration Index improved from 23% (18%-35%) to 16% (13%-19%). Endothoracic hump ratio improved from 1.34 (0.98-1.93) to 1.12 (0.86-1.28).
Conclusion:
Each patient with symptomatic scoliosis and thoracogenic scoliosis required relatively long periods of respiration management. Patients having lordoscoliosis with an apex located between T7 and T9 may develop airflow obstruction due to an endothoracic vertebral hump. Correction of lordoscoliosis through anterior and posterior approaches successfully improved endothoracic hump ratio and atelectasis in all patients.


Related Concept Videos
 01:16
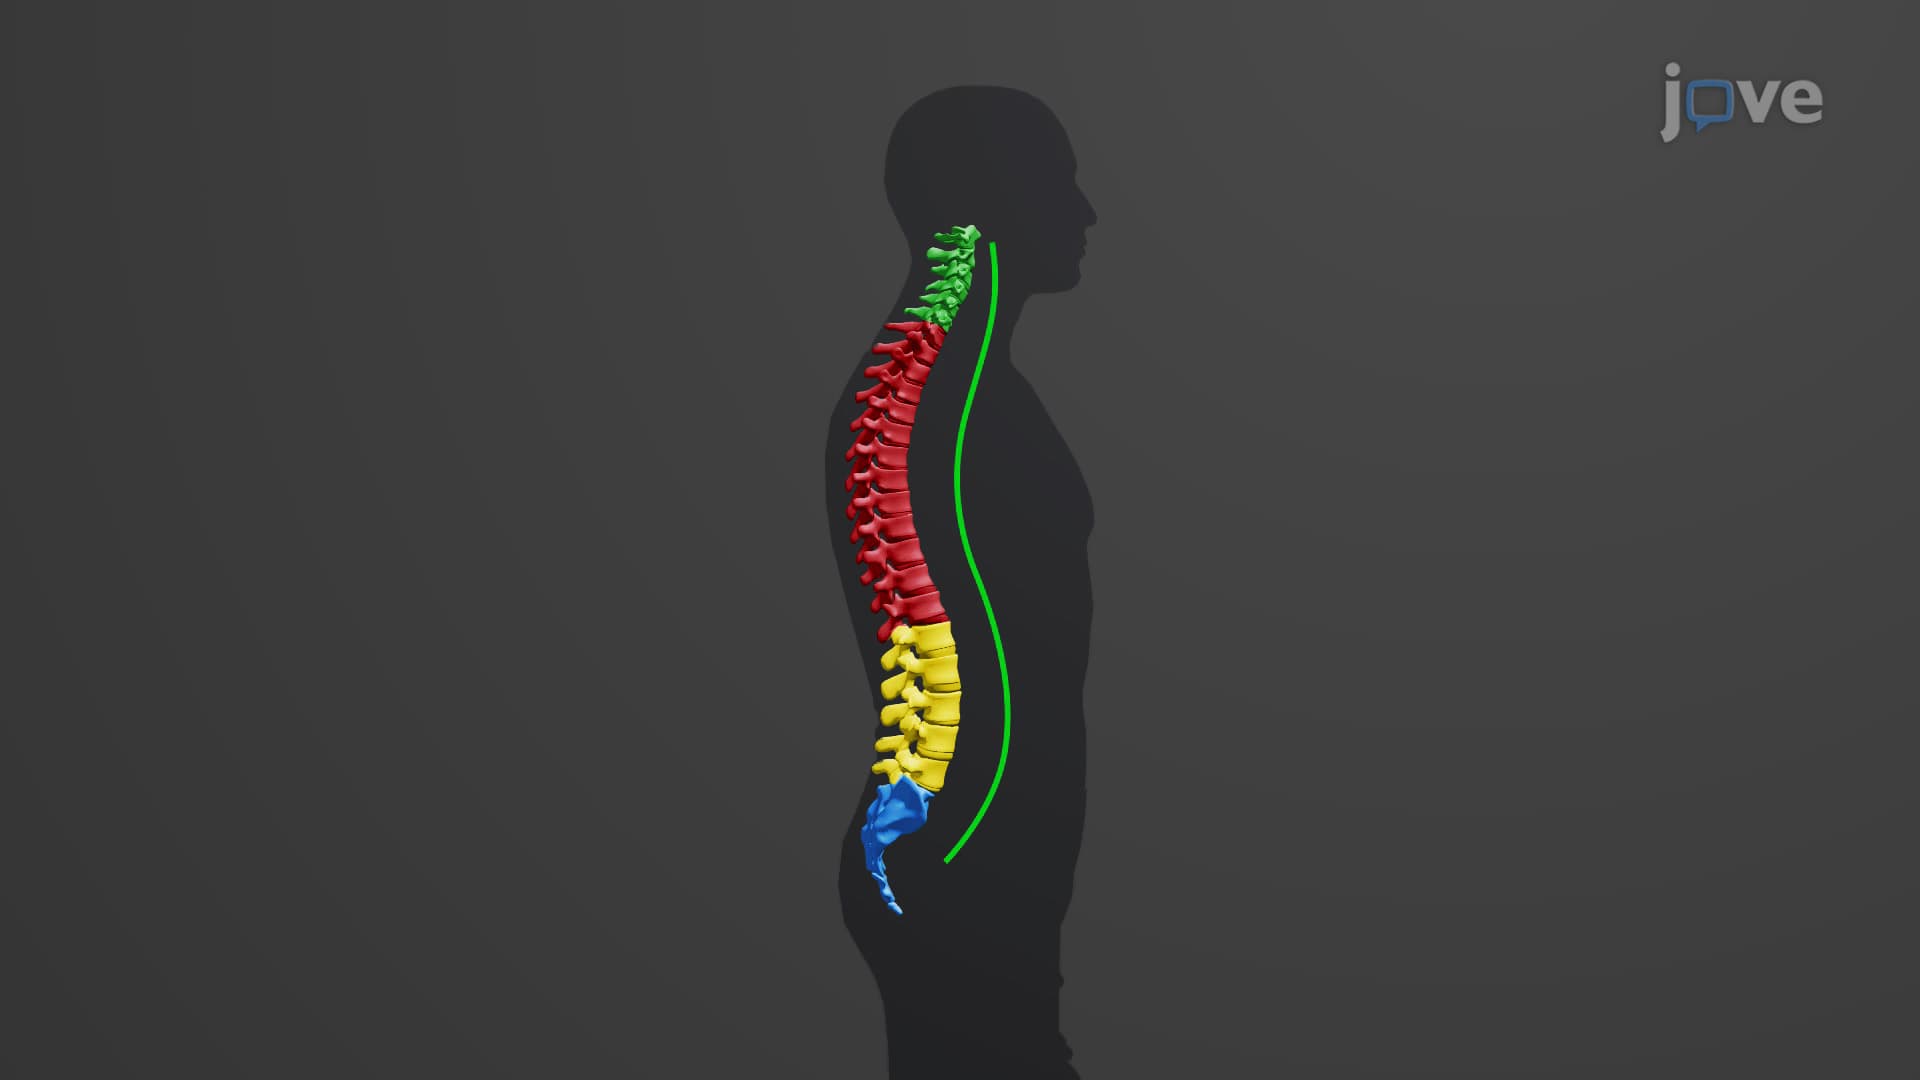
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:08
Pneumothorax II: Pathophysiology
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...