Related Experiment Video
Updated: May 17, 2026


Technical Considerations and Approach to Redo Foregut Surgery
Published on: September 22, 2023
Gastroesophageal reflux disease and antireflux surgery-what is the proper preoperative work-up?
Brian Bello1, Marco Zoccali, Roberto Gullo
1Department of Surgery, University of Chicago Pritzker School of Medicine, 5841 S. Maryland Ave., MC 5095, Chicago, IL 60637, USA.

Background:
Many surgeons feel comfortable performing antireflux surgery (ARS) on the basis of symptomatic evaluation, endoscopy, and barium esophagography. While esophageal manometry is often obtained to assess esophageal peristalsis, pH monitoring is rarely considered necessary to confirm the diagnosis of gastroesophageal reflux disease (GERD).
Aims:
The aim of this study was to analyze the sensitivity and specificity of symptoms, endoscopy, barium esophagography, and manometry as compared to pH monitoring in the preoperative evaluation of patients for ARS.
Patients And Methods:
One hundred and thirty-eight patients were referred for ARS with a diagnosis of GERD based on symptoms, endoscopy, and/or barium esophagography. Barium esophagography, esophageal manometry, and ambulatory 24-h pH monitoring were performed preoperatively in every patient.
Results:
Four patients were found to have achalasia and were excluded from the analysis. Based on the presence or absence of gastroesophageal reflux on pH monitoring, the remaining 134 patients were divided into two groups: GERD+ (n = 78, 58 %) and GERD- (n = 56, 42 %). The groups were compared with respect to the incidence of symptoms, presence of reflux and hiatal hernia on esophagogram, endoscopic findings, and esophageal motility. There was no difference in the incidence of symptoms between the two groups. Within the GERD+ group, 37 patients (47 %) had reflux at the esophagogram and 41 (53 %) had no reflux. Among the GERD- patients, 17 (30 %) had reflux and 39 (70 %) had no reflux. A hiatal hernia was present in 40 and 32 % of patients, respectively. Esophagitis was found at endoscopy in 16 % of GERD+ patients and in 20 % of GERD- patients. Esophageal manometry showed no difference in the pressure of the lower esophageal sphincter or quality of peristalsis between the two groups.
Conclusions:
The results of this study showed that (a) symptoms were unreliable in diagnosing GERD, (b) the presence of reflux or hiatal hernia on esophagogram did not correlate with reflux on pH monitoring, (c) esophagitis on endoscopy had low sensitivity and specificity, and (d) manometry was mostly useful for positioning the pH probe and rule out achalasia. Ambulatory 24-h pH monitoring should be routinely performed in the preoperative work-up of patients suspected of having GERD in order to avoid unnecessary ARS.

Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
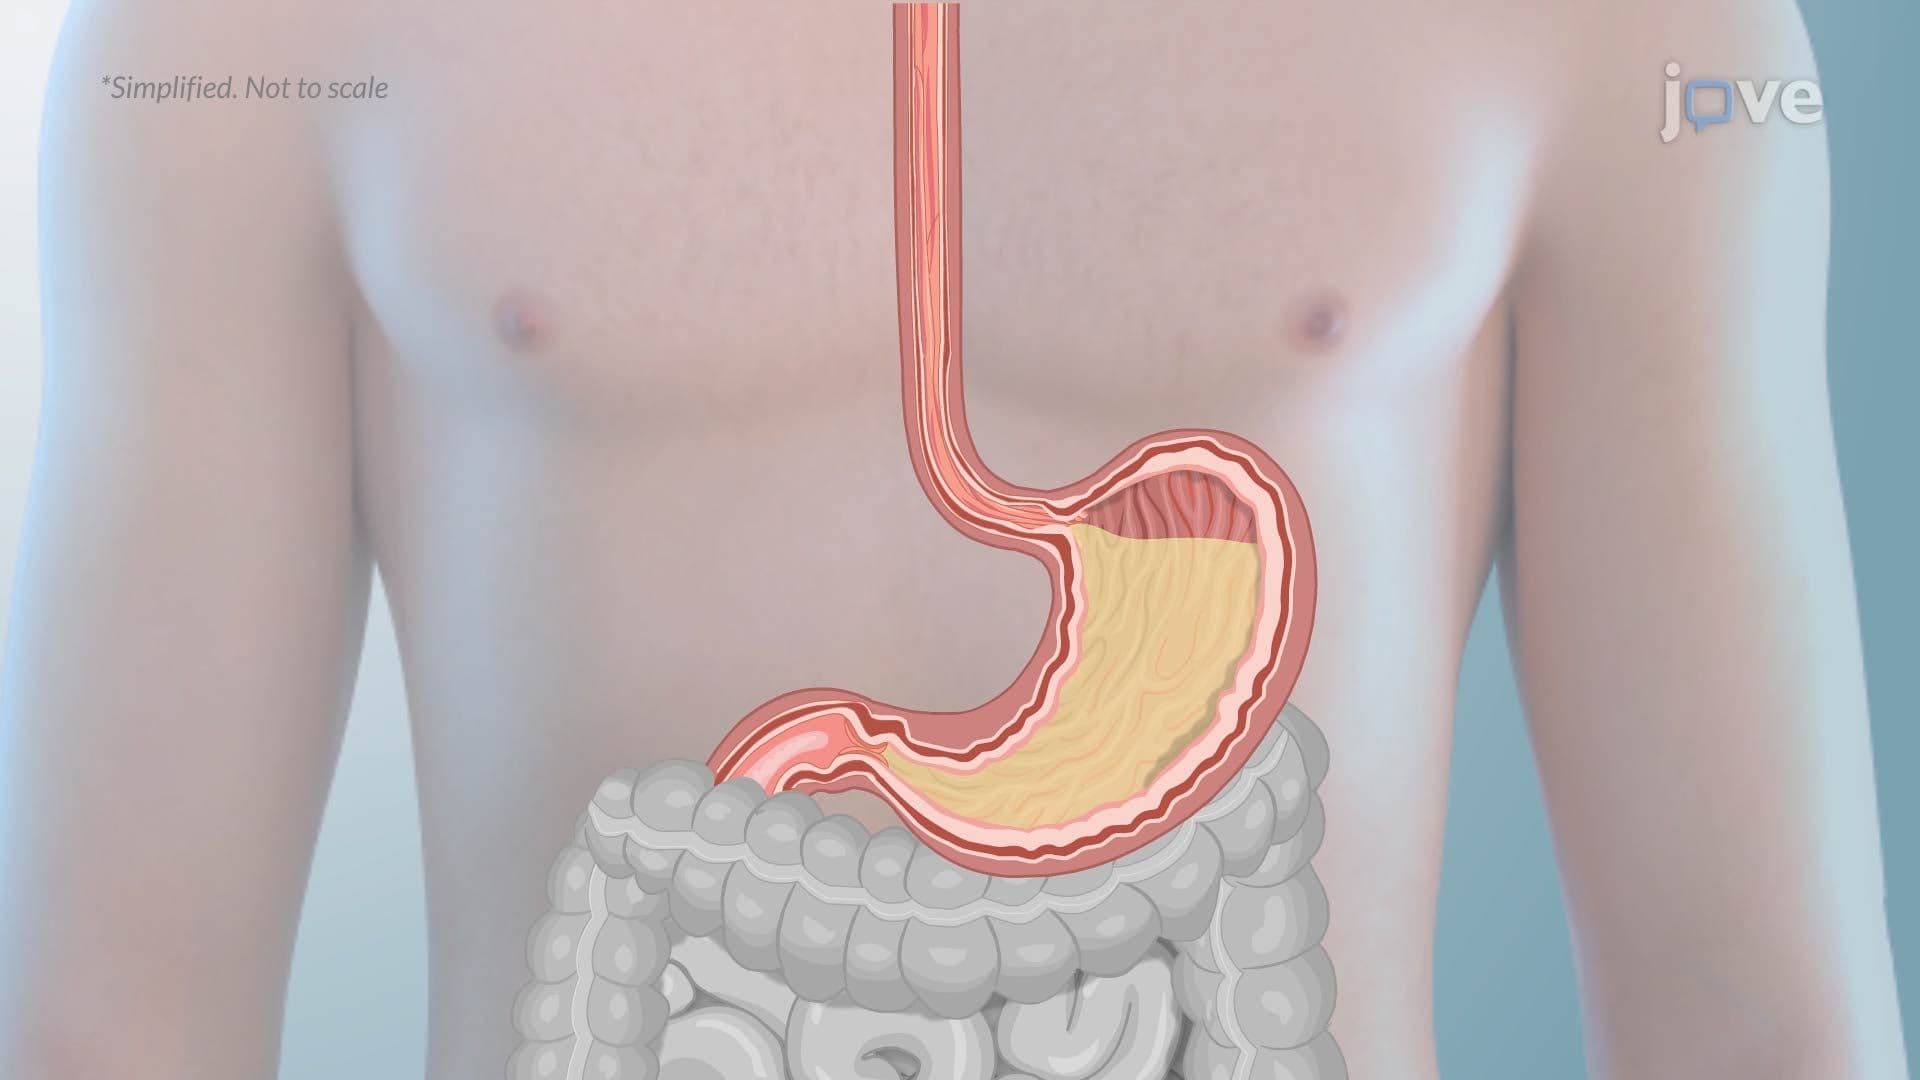 01:25
Gastroesophageal Reflux Disease
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:24
Upper GI Series: Barium Swallow
Purpose and Procedure
Patients undergoing this procedure ingest a liquid containing barium sulfate with a chalky...