Related Experiment Video
Updated: May 16, 2026

Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Respiratory impedance and bronchodilator responsiveness in healthy children aged 2-13 years
Claudia Calogero1, Shannon J Simpson, Enrico Lombardi
1Unit of Respiratory Medicine, Department of Paediatrics, University of Florence, Anna Meyer University Hospital for Children, Florence, Italy.

Insights
This study establishes reference ranges for respiratory impedance in children using the forced oscillation technique (FOT). It also defines bronchodilator responsiveness (BDR) cut-offs for healthy children, aiding in lung function assessment.
Area of Science:
- Pediatric pulmonology
- Respiratory physiology
- Diagnostic techniques
Background:
- The forced oscillation technique (FOT) is valuable for assessing lung function in children unable to perform spirometry.
- Limited data exists on FOT outcomes and bronchodilator responsiveness (BDR) in healthy children beyond preschool age.
- This study aimed to establish reference ranges for FOT outcomes and define BDR in healthy children.
Purpose of the Study:
- To create multi-center reference ranges for respiratory impedance outcomes in healthy children.
- To determine bronchodilator responsiveness (BDR) in a large cohort of healthy children using FOT.
- To define cut-offs for a positive BDR in pediatric populations.
Main Methods:
- Respiratory impedance was measured in 760 healthy children (aged 2-13 years) from Australia and Italy.
- Anthropometric predictors for respiratory system resistance (R(rs)), reactance (X(rs)), resonant frequency (Fres), frequency dependence of R(rs) (Fdep), and area under the reactance curve (AX) were identified.
- Bronchodilator response was assessed in 508 children after inhaling 200 µg of salbutamol.
Main Results:
- Respiratory system resistance (R(rs)), reactance (X(rs)), and area under the reactance curve (AX) were found to be dependent on height and sex.
- Bronchodilator responsiveness (BDR) cut-offs were established for absolute, relative, and Z-score changes in R(rs8), X(rs8), and AX.
- Specific cut-offs for a positive BDR were determined, including relative changes like -32% for R(rs8) and 65% for X(rs8).
Conclusions:
- Generalizable reference ranges for respiratory impedance using FOT have been established for healthy children.
- Cut-offs for defining a positive bronchodilator response (BDR) in healthy children have been successfully defined.
- These findings provide valuable tools for interpreting FOT results and assessing BDR in pediatric populations.
Background:
The forced oscillation technique (FOT) can be used in children as young as 2 years of age and in those unable to perform routine spirometry. There is limited information on changes in FOT outcomes in healthy children beyond the preschool years and the level of bronchodilator responsiveness (BDR) in healthy children. We aimed to create reference ranges for respiratory impedance outcomes collated from multiple centers. Outcomes included respiratory system resistance (R(rs)) and reactance (X(rs)), resonant frequency (Fres), frequency dependence of R(rs) (Fdep), and the area under the reactance curve (AX). We also aimed to define the physiological effects of bronchodilators in a large population of healthy children using the FOT.
Methods:
Respiratory impedance was measured in 760 healthy children, aged 2-13 years, from Australia and Italy. Stepwise linear regression identified anthropometric predictors of transformed R(rs) and X(rs) at 6, 8, and 10 Hz, Fres, Fdep, and AX. Bronchodilator response (BDR) was assessed in 508 children after 200 µg of inhaled salbutamol.
Results:
Regression analysis showed that R(rs), X(rs), and AX outcomes were dependent on height and sex. The BDR cut-offs by absolute change in R(rs8), X(rs8), and AX were -2.74 hPa s L(-1), 1.93 hPa s L(-1), and -33 hPa s L(-1), respectively. These corresponded to relative and Z-score changes of -32%; -1.85 for R(rs8), 65%; 1.95 for X(rs8), and -82%; -2.04 for AX.
Conclusions:
We have established generalizable reference ranges for respiratory impedance and defined cut-offs for a positive bronchodilator response using the FOT in healthy children.
Related Concept Videos
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:15
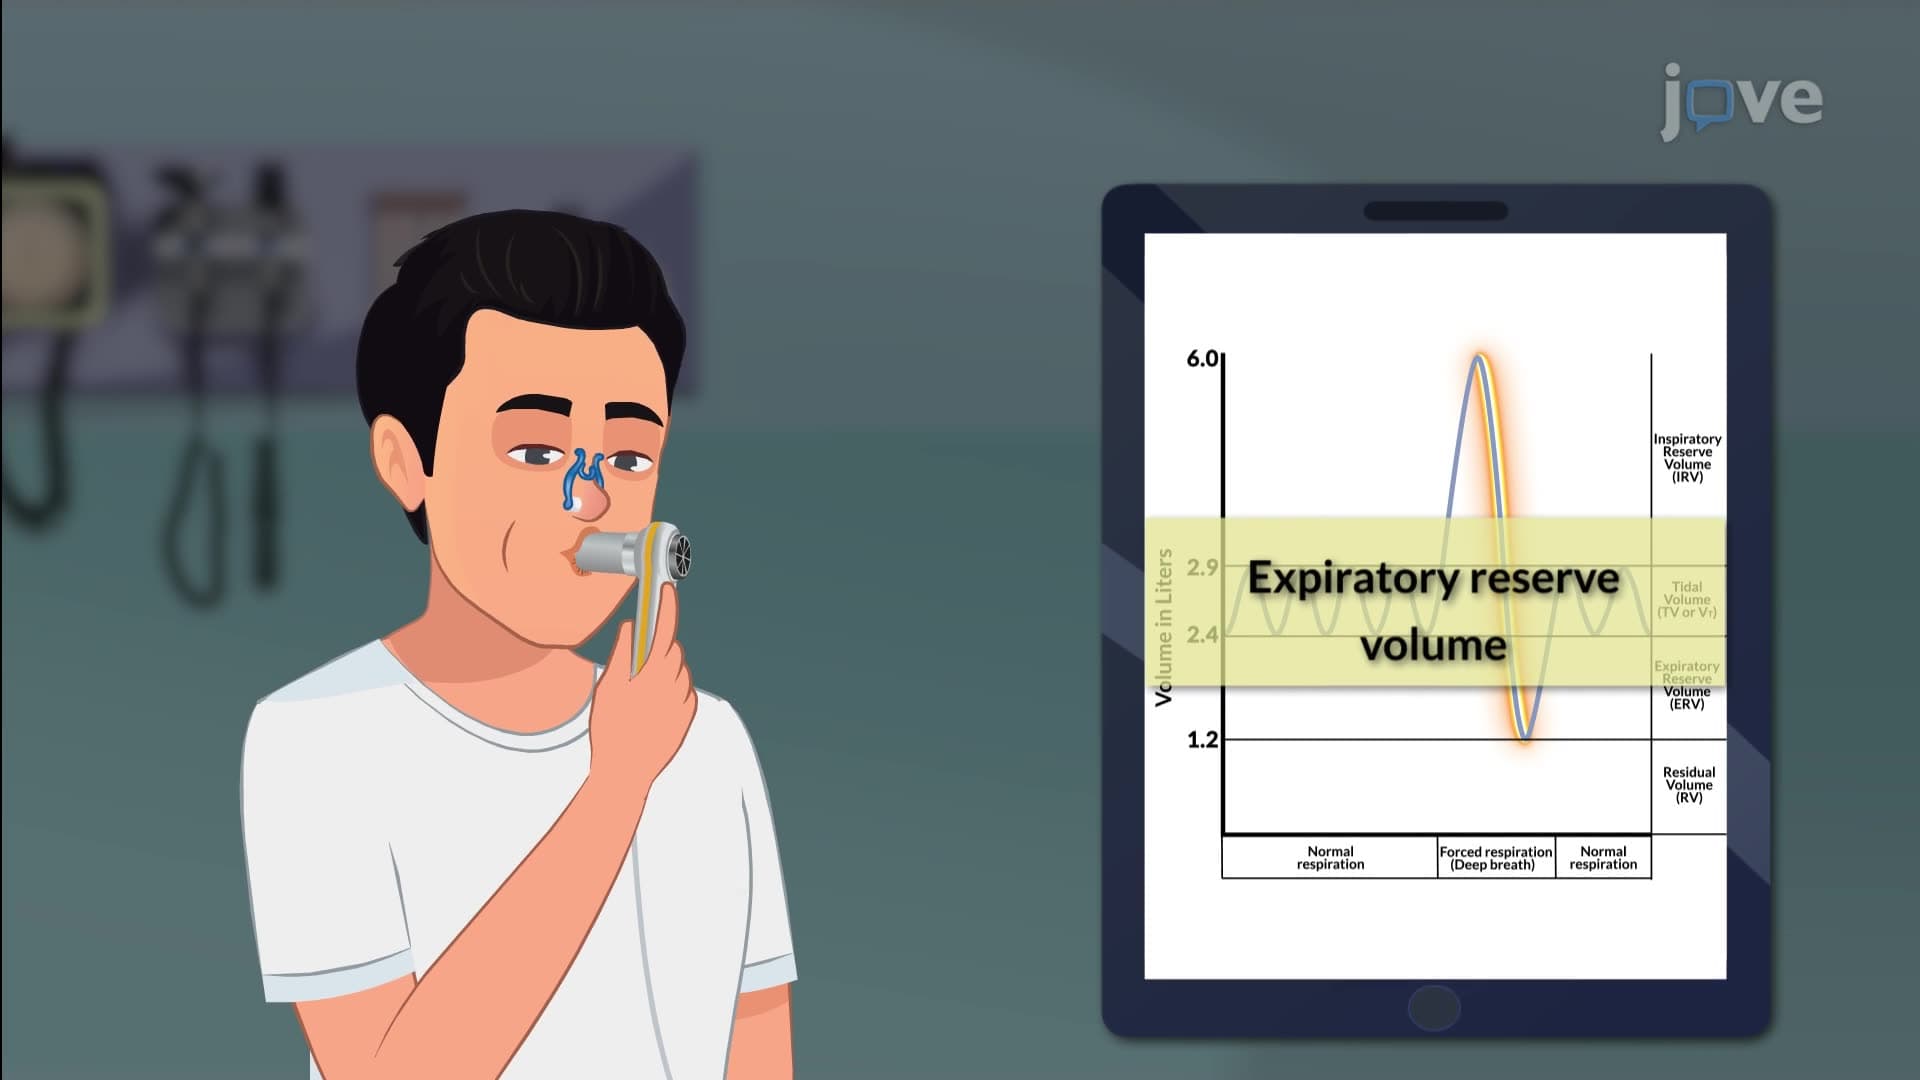
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:28
Physical Assessment of the Respiratory Tract I: Health History
Subjective Data
Subjective data provides vital information about the patient's health history and symptoms. This data is typically collected through interviews in which patients describe their experiences, symptoms, and concerns.
Health history and key...