Related Experiment Video
Updated: May 15, 2026
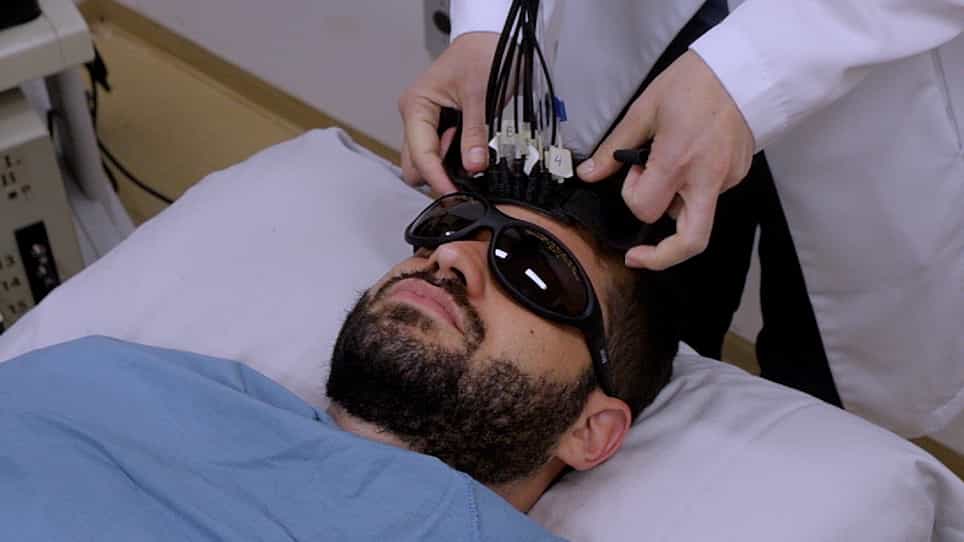

Real-Time Monitoring of Neurocritical Patients with Diffuse Optical Spectroscopies
Published on: November 19, 2020
Can neurophysiological assessment improve timing of intervention in posthaemorrhagic ventricular dilatation?
Katrin Klebermass-Schrehof1, Zsofia Rona, Thomas Waldhör
1Division of Neonatology, Intensive Care and Neuropediatrics, Department of Pediatrics and Adolescent Medicine, Medical University of Vienna, Waehringer Guertel 18-20, Vienna, Austria. katrin.klebermass-schrehof@meduniwien.ac.at

Insights
Flash visual evoked potentials (fVEP) and amplitude-integrated electroencephalography (aEEG) effectively monitor preterm infants with posthaemorrhagic ventricular dilatation (PHVD). These neurophysiological tools detect changes before clinical signs, aiding in evaluating intervention effectiveness.
Area of Science:
- Neonatal neurology
- Neurophysiology
- Pediatric neurosurgery
Background:
- Intraventricular haemorrhage is a primary cause of brain lesions in preterm infants.
- Posthaemorrhagic ventricular dilatation (PHVD) can result in significant neurological deficits.
- Non-invasive neurophysiological monitoring is crucial for managing PHVD.
Purpose of the Study:
- To evaluate flash visual evoked potentials (fVEP) and amplitude-integrated electroencephalography (aEEG) in preterm infants with progressive PHVD.
- To correlate fVEP and aEEG findings with the severity of ventricular dilatation.
- To assess the utility of fVEP and aEEG before and after neurosurgical intervention for PHVD.
Main Methods:
- Weekly fVEP and aEEG recordings were performed in 17 preterm infants with developing PHVD.
- Recording frequency increased to twice weekly when the ventricular index reached the 97th percentile.
- Neurophysiological data were collected until and after cerebrospinal fluid removal via external ventricular drainage.
Main Results:
- All patients (100%) showed increased fVEP wave latencies with progressive PHVD.
- Increased aEEG suppression was observed in 76% of patients with worsening ventricular dilatation.
- Neurophysiological patterns normalized within approximately 8.5 days post-intervention, often preceding clinical signs of increased intracranial pressure.
Conclusions:
- fVEP and aEEG are valuable non-invasive tools for evaluating preterm infants with progressive PHVD.
- These methods provide early detection of neurological changes associated with PHVD.
- fVEP and aEEG aid in monitoring treatment response after cerebrospinal fluid diversion procedures.
Objective:
Intraventricular haemorrhage is still the most common cause of brain lesion in preterm infants and development of a posthaemorrhagic ventricular dilatation (PHVD) can lead to additional neurological sequelae. Flash visual evoked potentials (fVEP) and amplitude-integrated electroencephalography (aEEG) are non-invasive neurophysiological monitoring tools. The aim of the study was to evaluate fVEPs and aEEGs in preterm infants with progressive PHVD prior to and after neurosurgical intervention for cerebrospinal fluid removal and to correlate the findings with severity of ventricular dilatation.
Design:
fVEPs and aEEGs were performed weekly in infants with developing PHVD. As soon as the ventricular index reached the 97th percentile recordings were performed twice a week.
Methods:
17 patients admitted to the neonatal intensive care unit of the Medical University of Vienna who developed progressive PHVD were evaluated using fVEP and aEEG until and after reduction of intracranial pressure by placement of an external ventricular drainage.
Results:
In all 17 cases (100%) wave latencies of fVEP increased above normal range and aEEG showed increased suppression in 13 patients (76%) with increasing ventricular dilatation. Both methods showed normalisation of patterns mostly within a week of successful therapeutic intervention (mean 8.5 days). Both changes in fVEP latencies and aEEG background patterns were detected before clinical signs of elevated intracranial pressure occurred. In only 10 patients (58.8%) ventricular width exceeded the 97th percentile+4 mm.
Conclusions:
fVEP and aEEG are useful additional tools for the evaluation of preterm infants with progressive PHVD.
