Divergence in student and educator conceptual structures during auscultation training
Related Experiment Video
Updated: May 15, 2026
Using Simulation Models to Train Clinicians in the Use of Point-of-Care Ultrasound
Published on: August 9, 2024
Ryan Brydges1, Adam Peets, S Barry Issenberg
1Department of Medicine, University of Toronto, Toronto, Ontario, Canada. ryan.brydges@utoronto.ca

Context:
Simulation-based medical education allows trainees to engage in self-regulated learning (SRL), yet research aimed at elucidating the mechanisms of SRL in this context is relatively absent. We compared 'unguided' SRL with 'directed' SRL (DSRL), wherein learners followed an expert-designed booklet.
Methods:
Year 1 medical students (n = 37) were randomly assigned to practise identifying seven cardiac murmurs using a simulator and video only (SRL group) or a simulator and video plus the booklet (DSRL group). All participants completed a 22-item test 3 weeks later. To compare interventions, we analysed students' diagnostic accuracy. As a novel source of evidence, we documented how participants autonomously sequenced the seven murmurs during initial and delayed practice sessions. In addition, we surveyed clinical educators (n = 17) to find out how they would sequence their teaching of these murmurs.
Results:
The DSRL group used 50% more training time than the SRL group (p < 0.001). The groups' diagnostic accuracy, however, did not differ significantly on the post-test, retention test or transfer test items (p > 0.12). Despite practising with the expert-defined 'timing-based' approach to murmur diagnosis (i.e. systolic versus diastolic), 84% of DSRL participants implemented a location-based approach (i.e. practising aortic murmurs separately from mitral murmurs) during a second, unguided practice session. Notably, most SRL participants used that same approach spontaneously. By contrast, clinical educators were split in their use of the timing-based (n = 10) and the location-based (n = 6) approaches. Chi-squared analyses suggested educators' conceptions for organising murmurs differed significantly from students' conceptions.
Conclusions:
Contrary to our predictions, directing students' SRL produced no additional benefit and increased their practice time. Our findings suggest one potential source of these results was a divergence between student and educator conceptions for structuring the practice of cardiac auscultation skills. This phenomenon has not been well articulated in the medical education literature, and may have important implications in many (especially technology-mediated) educational contexts.
Related Concept Videos
 01:25
Assessment of the Cardiovascular System IV: Auscultation
Normal Heart Sounds
S1 (First Heart Sound)-
S1 is made by the closure of the mitral and tricuspid valves (atrioventricular valves), marking the beginning of systole.
S2 (Second Heart Sound)-
S2 is made by the closure of the aortic and pulmonic valves (semilunar valves), marking the end of the systole.
 01:25
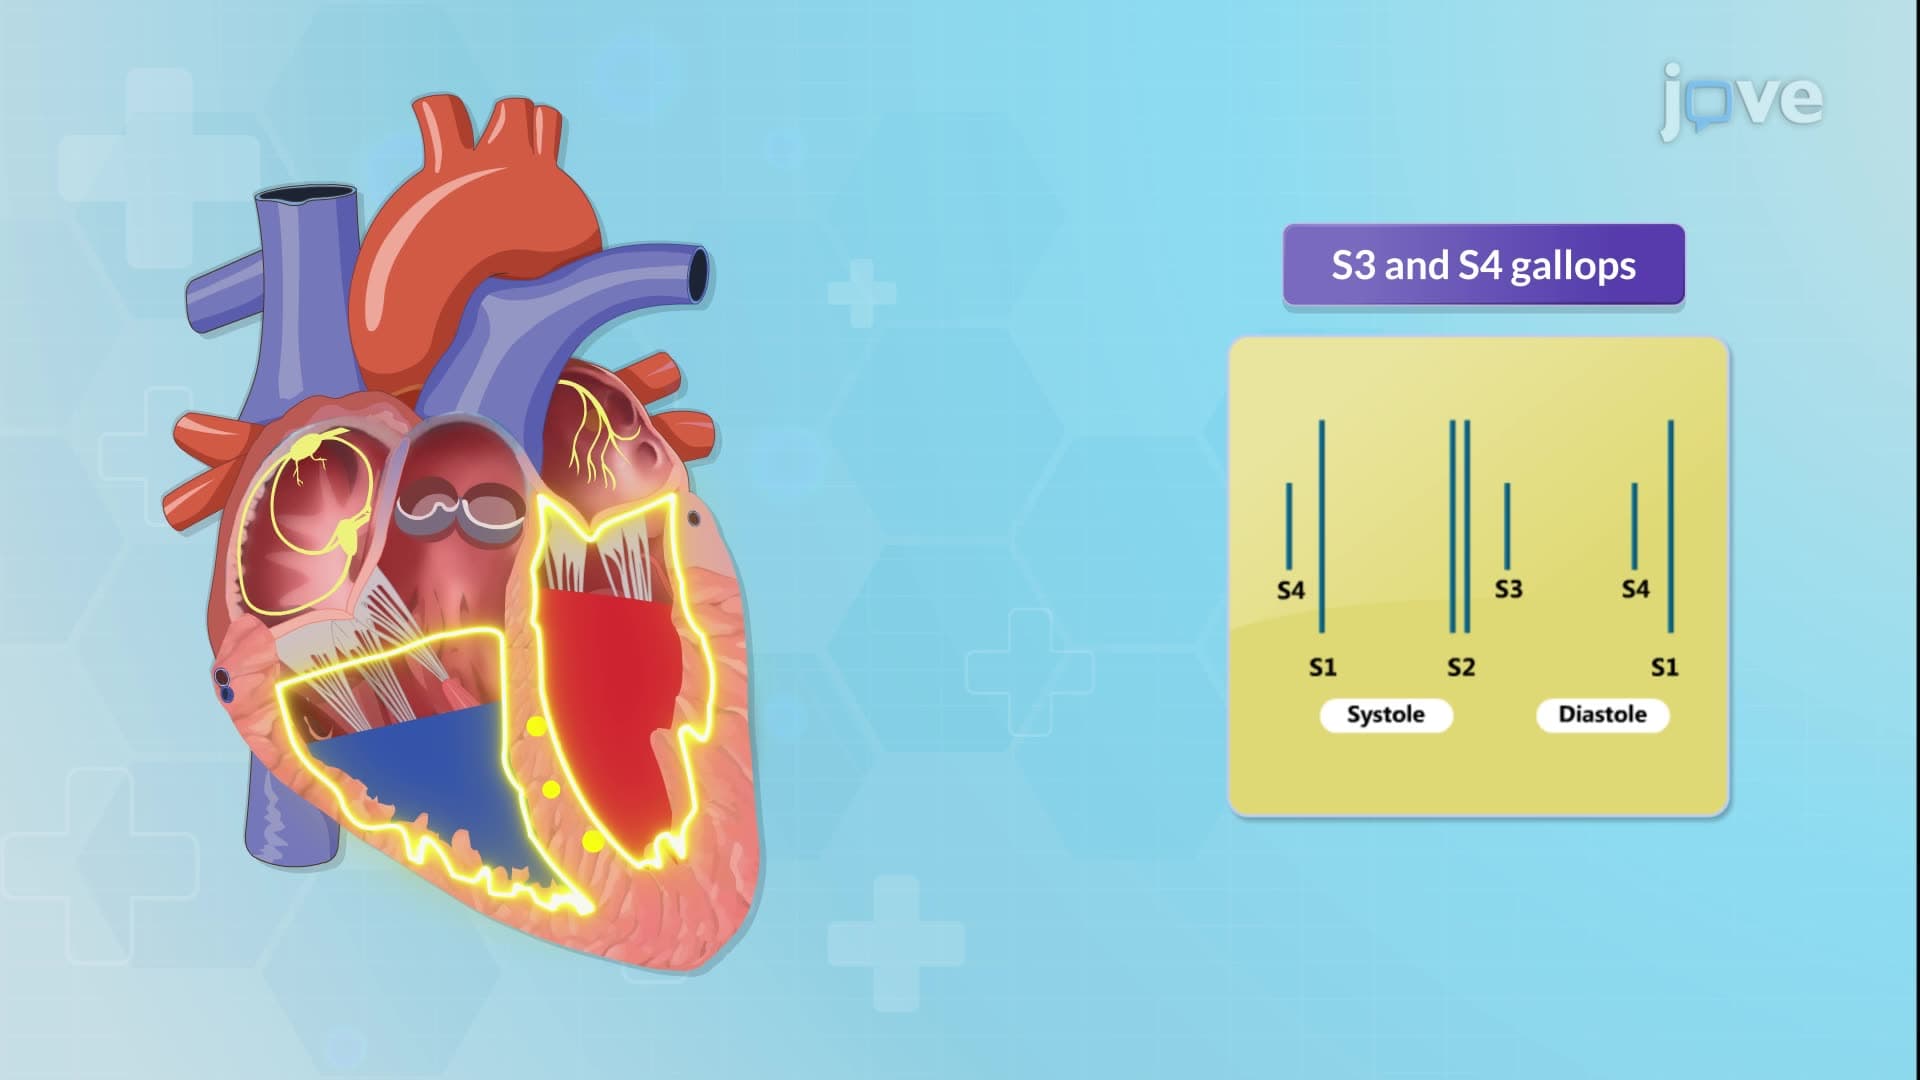
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:28
Physical Assessment of the Respiratory Tract IV: Auscultation
Breath Sounds
Breath sounds are categorized into vesicular, bronchovesicular, and bronchial.
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities:
 01:25
Assessment of the Abdomen I: Inspection and Auscultation
The abdominal examination is a cornerstone of clinical medicine, serving as a critical tool in diagnosing various gastrointestinal (GI) diseases. It involves a systematic approach that includes inspection and auscultation, each with distinct yet complementary roles in assessing the abdomen. This article will delve into these two primary methods healthcare professionals use to examine the abdomen.
Inspection of the Abdomen
The first step in any abdominal examination is inspection.
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: