Related Experiment Video
Updated: May 12, 2026
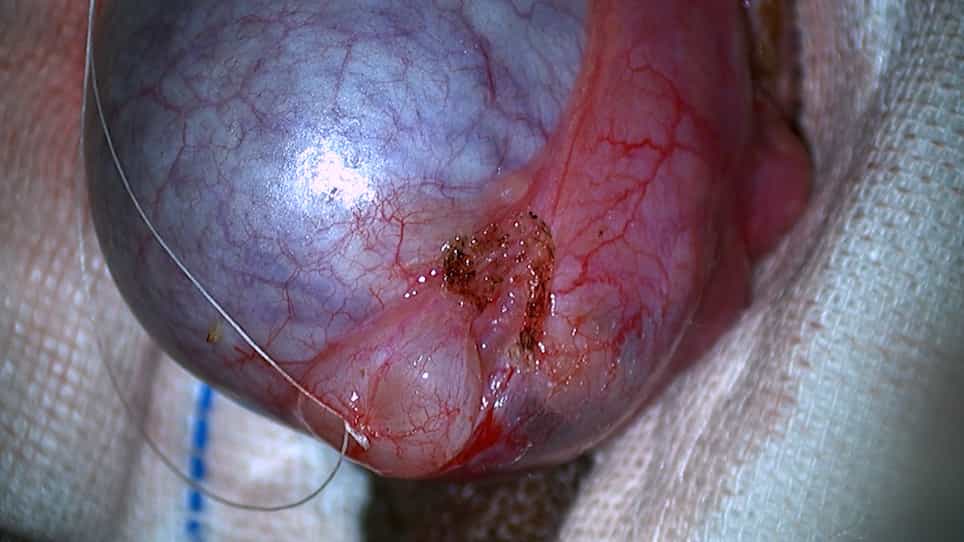

Microscopic Cyst Resection for the Treatment of Patients Diagnosed with Epididymal Cyst
Published on: March 31, 2023
Battlefield scrotal trauma: how should it be managed in a deployed military hospital?
R J Williams1, C A Fries, M Midwinter
1Institute of Naval Medicine, Alverstoke, Gosport, PO12 2DL, United Kingdom. Richard.williams8@nhs.net

Aim:
There is little documented advice on the management of scrotal trauma sustained in combat. This paper reviews this injury, its present surgical management and makes recommendations for the future.
Method:
All UK forces sustaining scrotal injuries between 2003 and 2009, in Iraq and Afghanistan, initially treated at a Role 2 (enhanced) or Role 3 deployed military surgical facility were identified from the Joint Theatre Trauma Registry. The cause and extent of the injury, in addition to the surgical management, are reported.
Results:
Twenty-seven patients sustained trauma to their scrotum; improvised explosive device (IED) (n=21), mine (n=3), rocket propeller grenade (RPG) (n=2), mortar round (n=1). Of those injured by an IED, eleven had traumatic orchidectomies, of which 4 were bilateral, one received fragmentation wounds to the scrotum with a testicular injury that was salvaged and there were six scrotal fragmentation wounds not associated with a testicular injury. Scrotal exploration was performed with testicular salvage in all cases involving mortar, RPG or mines. For all aetiologies the scrotum was debrided with primary closure over a drain (n=7), debridement and subsequent delayed primary closure (DPC) (n=4) or healing by secondary intension (n=6). Skin grafts were applied in two cases of traumatic bilateral orchidectomy. To date there have been two cases of delayed orchidectomy; chronic pain and delayed presentation of a disrupted testis. All reported patients survived.
Conclusion:
The established principles of debridement should be the mainstay of treatment. Testicular ischaemia, a consequence of cord transaction, necessitates orchidectomy. Salvage of the disrupted testis, with debridement and closure of the tunica rather than orchidectomy, should be performed whenever possible, particularly when there is significant bilateral testicular injury. Scrotal wounds can be treated by closure over a drain, DPC or healing by secondary intention.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...