Related Experiment Video
Updated: May 11, 2026


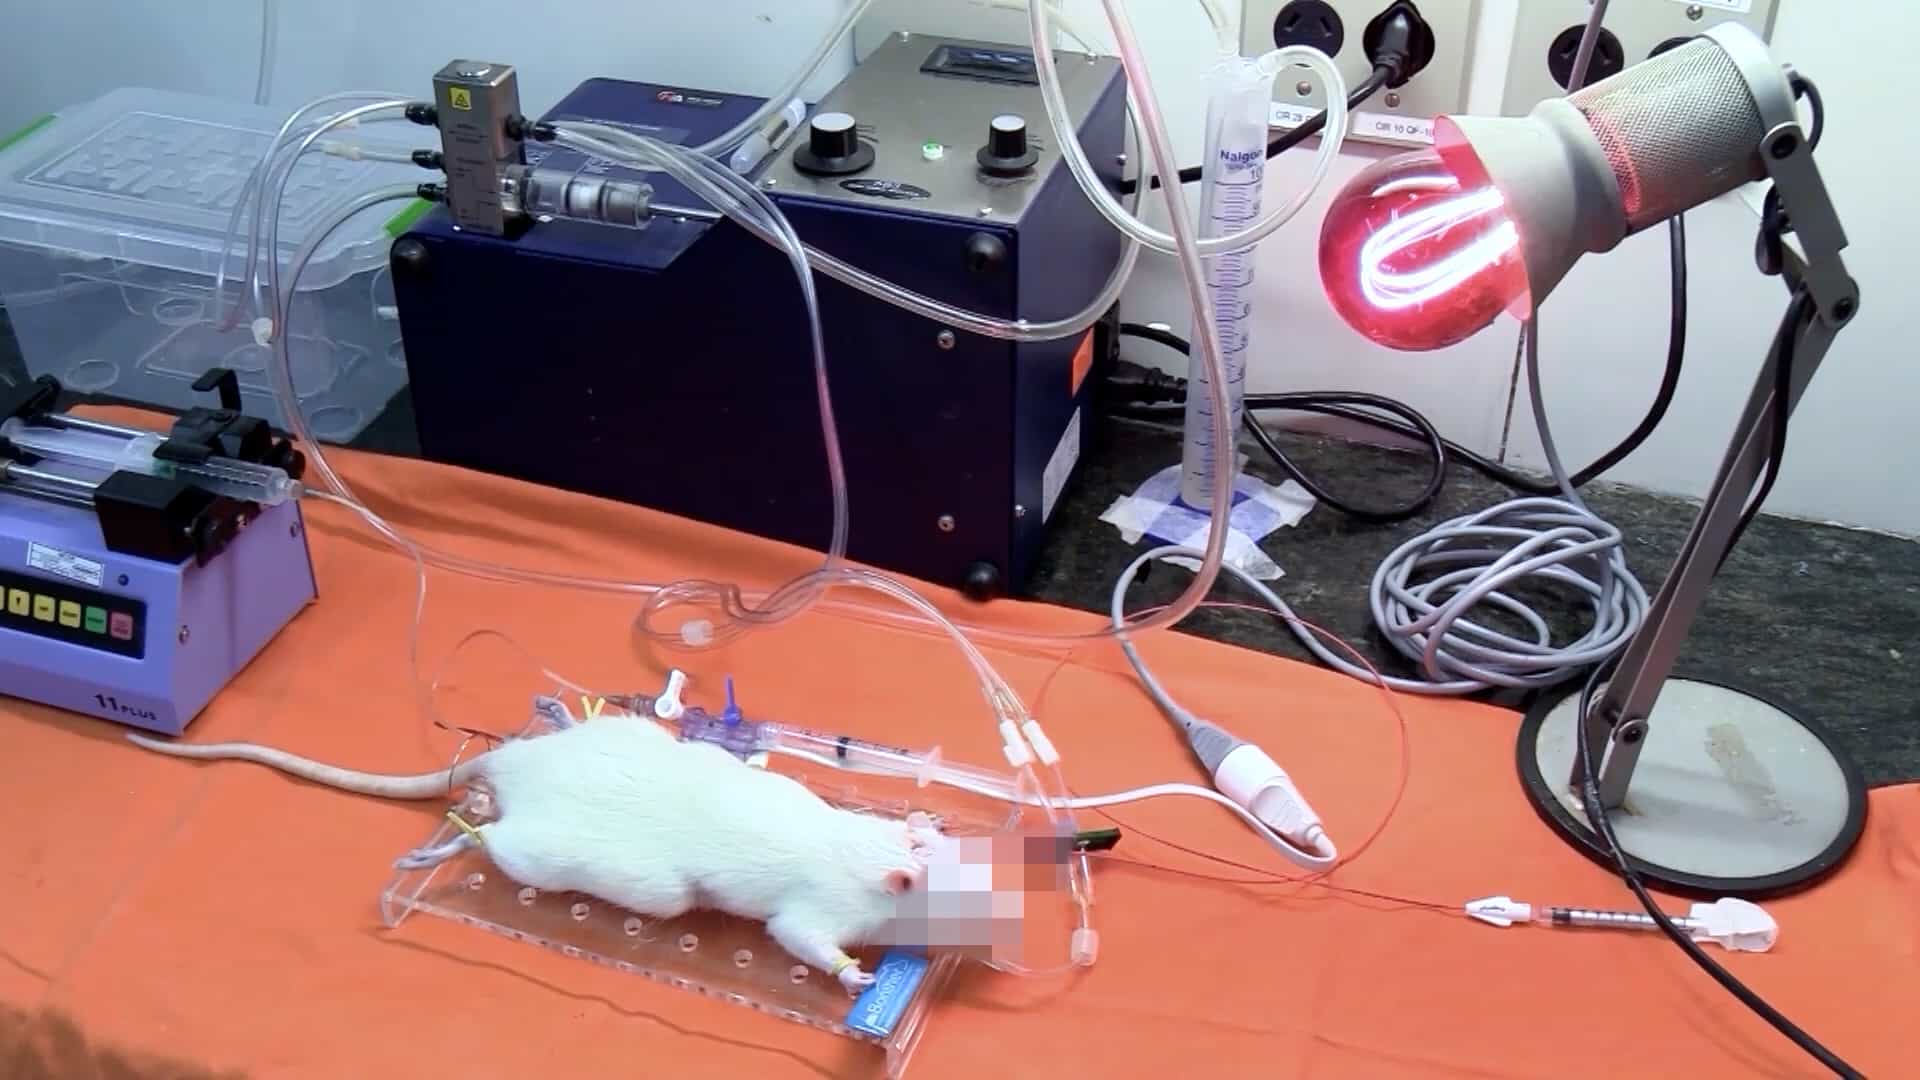
Brain Death Induction in Mice Using Intra-Arterial Blood Pressure Monitoring and Ventilation via Tracheostomy
Published on: April 17, 2020
Coma and brain death
Fenella J Kirkham1, Stephen Ashwal
1Neurosciences Unit, University College London Institute of Child Health, London, UK.

Abstract:
Coma must persist for at least 1 hour to distinguish it from transient unconsciousness. Traumatic and nontraumatic coma are common problems in pediatric practice with high mortality and morbidity. Emergency neuroimaging is worthwhile even when etiology is known, as treatable complications, such as venous sinus thrombosis, as well as extradural and intracerebral hemorrhage, are commonly diagnosed. There is a wide range of possible etiologies in the previously well child, most of which may be diagnosed from neuroimaging and laboratory testing available as an emergency, or can be treated presumptively, e.g., with antimicrobials for infections. The modified Child's Glasgow Coma Scale (CGCS) for recording depth of consciousness in children is widely used and should be supplemented by examination for the signs of reversible central and uncal brainstem herniation due to acute intracranial hypertension. An evidence-based guideline for the investigation and management of decreased level of consciousness in children, written by an expert panel using the DELPHI principles, is available. Monitoring and rehabilitation should also be part of the management plan. Etiology, depth and duration of coma, and serial neurophysiology and imaging are predictors of outcome in survivors but must be interpreted cautiously. There are no reports of children meeting adult brain death criteria making good neurological recovery.

Related Concept Videos
 01:28
Traumatic Brain Injury l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:26
Brain Abscess l: Introduction
 01:29
Hepatic Encephalopathy
 01:19
Cerebral Edema l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology