Related Experiment Video
Updated: May 10, 2026


Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Prolonged treatment with vitamin D in postmenopausal women with primary hyperparathyroidism
Ranganathan R Rao1, Harpal S Randeva, Sailesh Sankaranarayanan
1Warwickshire Institute for the Study of Diabetes, Endocrinology and Metabolism University Hospitals Coventry and Warwickshire NHS Trust Coventry UK.

Introduction/Background:
Vitamin D deficiency further increases circulating parathyroid hormone (PTH) levels in patients with primary hyperparathyroidism (pHPT), with potential detrimental effects on bone mass.
Methods:
This was an observational clinical study in consecutive conservatively treated postmenopausal women (n=40) with pHPT and coexistent 25-hydroxyvitamin D deficiency (25OHD ≤50 nmol/l (≤20 ng/ml)). Patients who showed an increase in serum 25OHD above the threshold of vitamin D deficiency (>50 nmol/l; n=28) using treatment with various commonly prescribed vitamin D preparations were, for the purposes of statistical analyses, allocated to the treatment group. Patients who were retrospectively identified as having received no treatment with vitamin D and/or remained vitamin D deficient were considered as non-responders/controls (n=12). Adjusted calcium (adjCa), PTH and 25OHD concentrations were monitored in all subjects up to 54 months (mean observation period of 18±2 months).
Results:
Prolonged increased vitamin D intake, regardless of the source (serum 25OHD, increase from 32.2±1.7 nmol/l at baseline to 136.4±11.6 nmol/l, P<0.0001), significantly reduced serum PTH (13.3±1.1 vs 10.5±1.0 pmol/l, P=0.0001), with no adverse effects on adjCa levels (2.60±0.03 vs 2.60±0.02 mmol/l, P=0.77) and renal function tests (P>0.73). In contrast, serum PTH remained unchanged (15.8±2.6 vs 16.3±1.9 pmol/l, P=0.64) in patients who remained vitamin D deficient, with a significant difference between groups in changes of PTH (P=0.0003). Intrapartial correlation analyses showed an independent negative correlation of changes in 25OHD with PTH levels (r ic=-0.41, P=0.014).
Conclusions:
Prolonged treatment with vitamin D in various commonly prescribed preparations appeared to be safe and significantly reduced PTH levels by 21%.
Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 00:59
The Parathyroid Glands
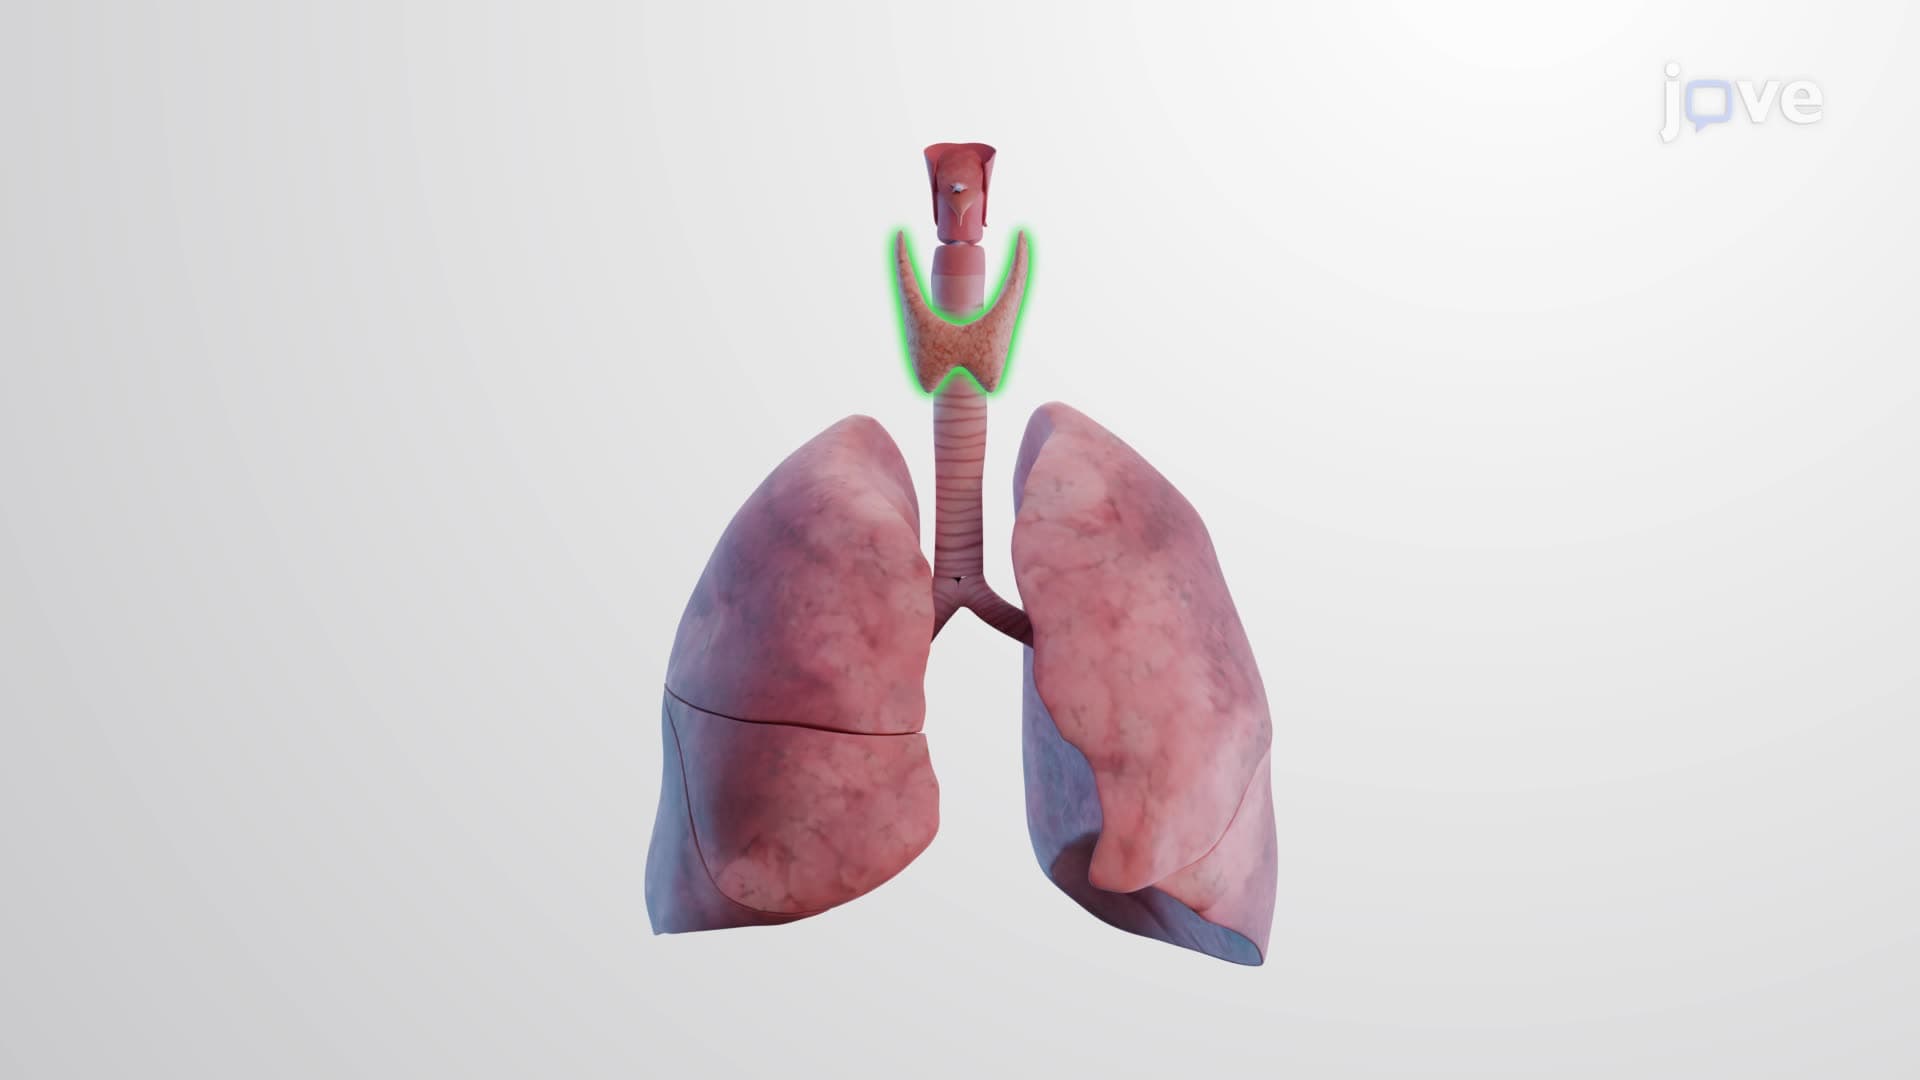
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 01:21
Skeleton and Calcium Homeostasis
 01:23
Role of Skin in Vitamin D Synthesis
The solar UV B rays (290-315 nm) are absorbed by the skin, and 7-dehydrocholesterol (provitamin D3) photolyzes it to previtamin D3, which undergoes a rapid transformation to vitamin D3(cholecalciferol).
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...