Related Experiment Video
Updated: May 9, 2026
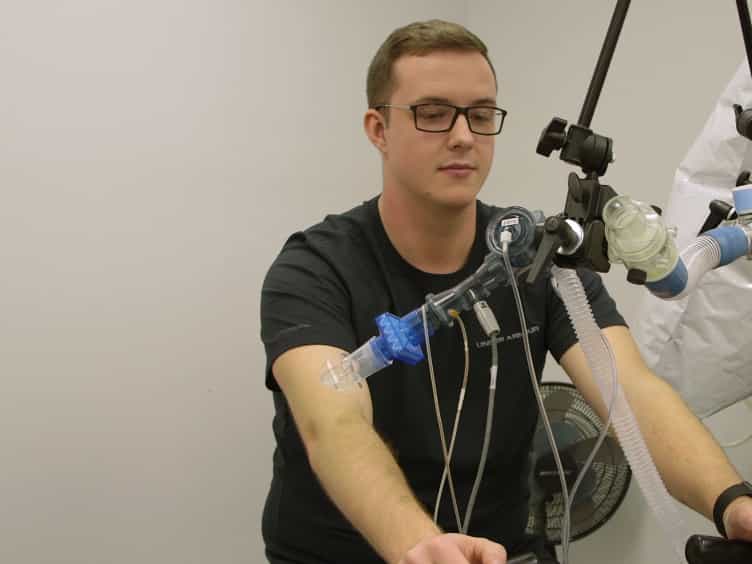

Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Airways obstruction and pulmonary capillary blood volume in children with sickle cell disease
Catherine J Wedderburn1, David Rees, Susan Height
1Division of Asthma, Allergy and Lung Biology, MRC & Asthma UK Centre in Allergic Mechanisms of Asthma, King's College London, London, SE5 9RS, United Kingdom.

Insights
In children with sickle cell disease (SCD), increased pulmonary capillary blood volume contributes to airway obstruction. This suggests bronchodilators may offer limited benefit for treating airway obstruction in these patients.
Area of Science:
- Pulmonary Medicine
- Pediatric Hematology
- Respiratory Physiology
Background:
- Airway obstruction is a significant complication in children with sickle cell disease (SCD).
- Understanding the underlying physiological mechanisms is crucial for effective treatment strategies.
Purpose of the Study:
- To investigate the relationship between pulmonary capillary blood volume and airway obstruction in children with SCD.
- To determine if increased pulmonary capillary blood volume contributes to airway obstruction in pediatric SCD patients.
Main Methods:
- An observational study comparing 25 children with SCD to 25 matched controls.
- Assessment of respiratory system resistance (R5 %pred), pulmonary capillary blood volume (Vc), alveolar volume (VA), and spirometry before and after bronchodilator administration.
- Lung volume measurements were also performed.
Main Results:
- Children with SCD exhibited higher respiratory system resistance and pulmonary capillary blood volume compared to controls, both before and after bronchodilator use.
- Pulmonary capillary blood volume (Vc/VA) showed a significant correlation with respiratory system resistance (R5 %pred) specifically in children with SCD.
- Bronchodilator administration resulted in similar reductions in respiratory system resistance in both groups, with no significant changes in pulmonary capillary blood volume.
Conclusions:
- Increased pulmonary capillary blood volume is a contributing factor to airway obstruction in children with SCD.
- The findings suggest that bronchodilators may have limited efficacy in ameliorating airway obstruction in this population.
- Further research into alternative therapeutic approaches targeting pulmonary vascular changes in pediatric SCD is warranted.
Objectives And Working Hypothesis:
Airways obstruction occurs in young children with sickle cell disease (SCD). Our aim was to test the hypothesis that increased pulmonary capillary blood volume at least in part explained the increased airways obstruction as this would inform which therapy might be most appropriate to treat the airway obstruction.
Study Design:
Observational study.
Patient-Subject Selection:
Twenty-five SCD children and 25 ethnic origin matched controls were recruited.
Methodology:
Respiratory system resistance, using impulse oscillometry at 5 Hz (R5 %pred), pulmonary capillary blood volume (Vc), alveolar volume (VA), and spirometry were assessed before and after bronchodilator (ipratropium bromide). Lung volume measurements were also made.
Results:
The SCD children compared to the controls had a higher R5 %pred before (median 133 (range 88-181)% vs. 102 (83-184)%, P = 0.0046) and after (105 (79-150)% vs. 91 (64-147)%, P = 0.0489) bronchodilator and their median Vc/VA (ml/L) was higher before (26 (18-38) vs. 18 (14-28) P < 0.0001) and after (26 (19-41) vs. 18 (13-27) P < 0.0001) bronchodilator. There were similar decreases in R5 %pred post-bronchodilator in the two groups, but no significant changes in Vc/VA in either group. Vc/VA correlated significantly with R5 %pred in the SCD children only.
Conclusions:
Increased pulmonary capillary blood volume contributes to the increased airways obstruction in children with SCD, hence, bronchodilators may be of limited benefit in reducing their airways obstruction.

Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:10
Atelectasis II: Pathophysiology
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:15
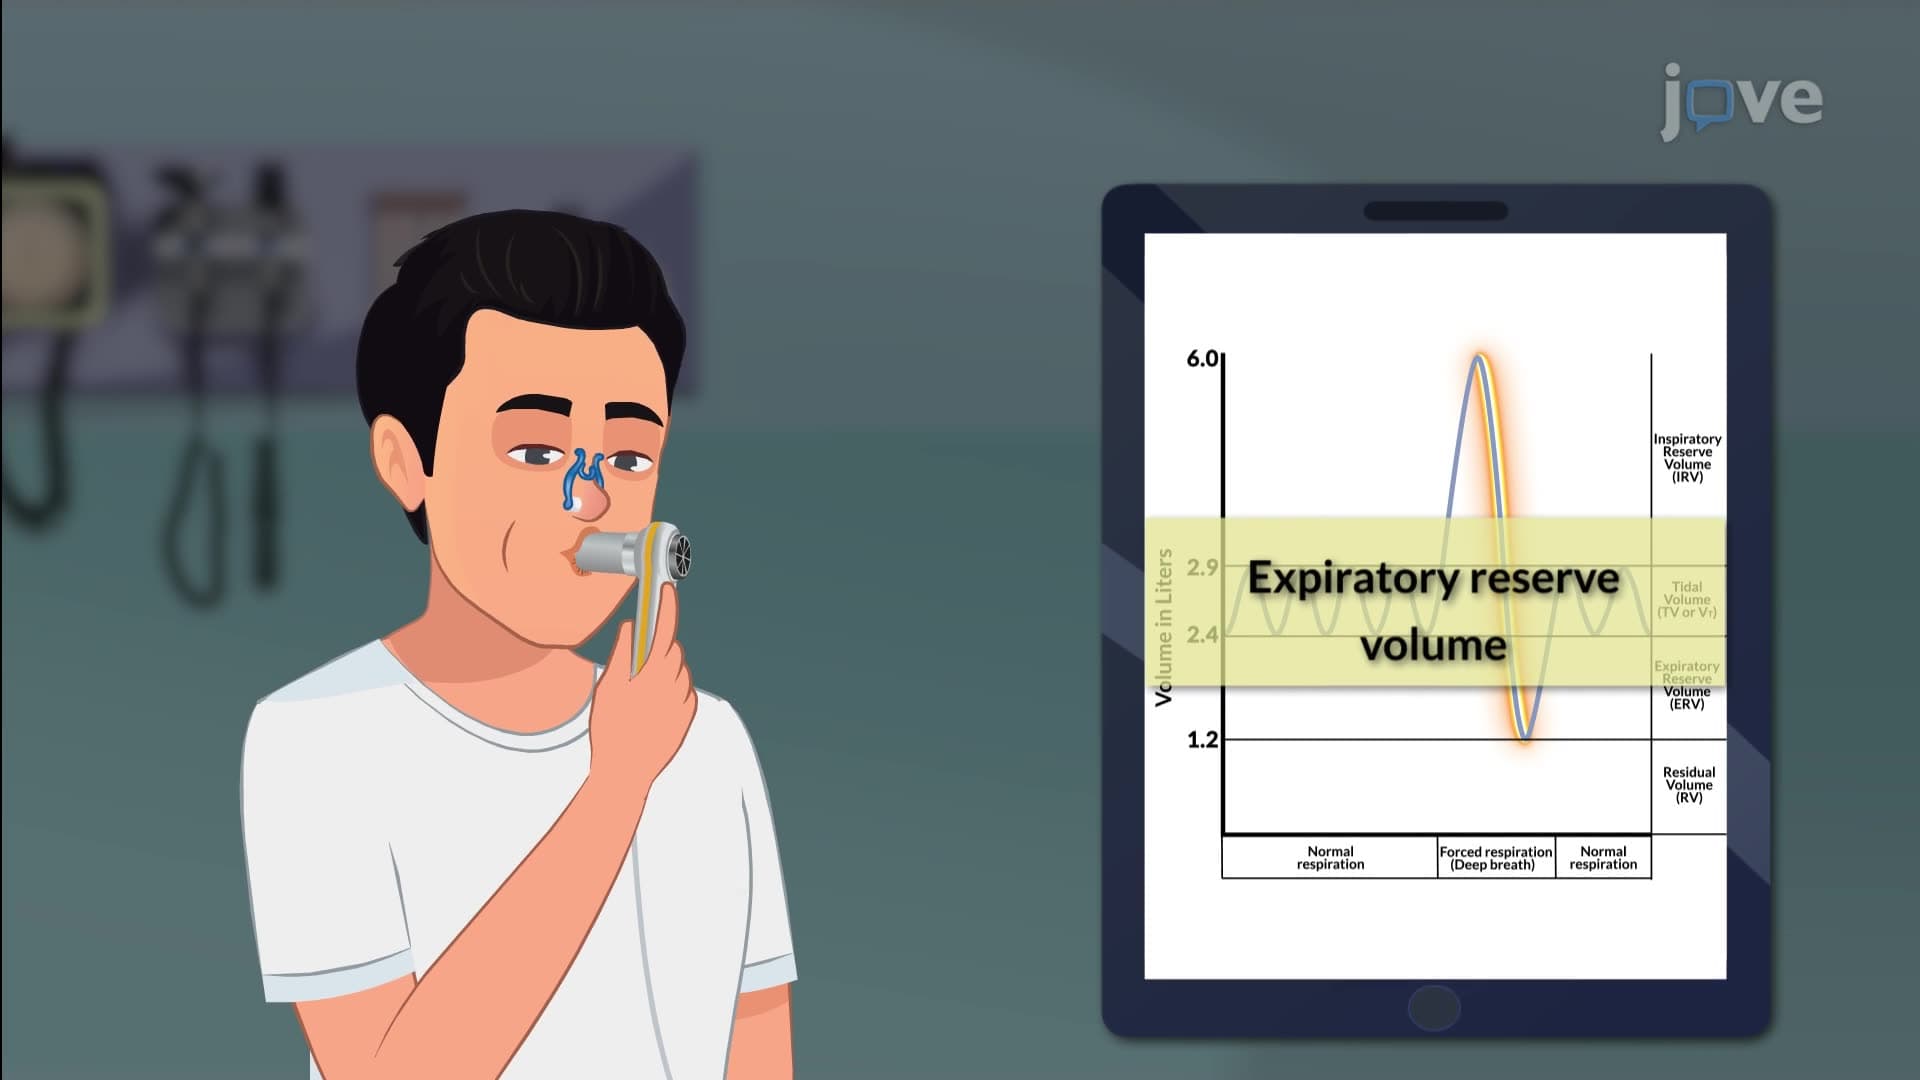
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:22
Respiratory Volumes and Capacities