Related Experiment Video
Updated: May 9, 2026

An Ex vivo Culture System to Study Thyroid Development
Published on: June 6, 2014
Reference range of thyroid hormones in very low birth weight infants at the time of discharge
Daisy K L Chan1, Vina Tagamolila, Jayapriya Ardhanari
11 Departments of Neonatal and Developmental Medicine, Singapore General Hospital , Singapore .

Insights
Thyroid hormone levels in preterm infants vary with age. Free thyroxine (fT4) shows a fair inverse correlation with postmenstrual age, suggesting age-specific reference ranges are crucial for very low birth weight (VLBW) babies.
Area of Science:
- Neonatal endocrinology
- Pediatric thyroid function
Background:
- Limited data exists on thyroid hormone reference ranges for preterm infants, particularly those with very low birth weight (VLBW).
- Understanding thyroid hormone levels in relation to postmenstrual age is essential for assessing thyroid function in this vulnerable population.
Purpose of the Study:
- To evaluate the relationship between thyroid hormone levels (free thyroxine [fT4] and thyrotropin [TSH]) and postmenstrual age in a cohort of stable VLBW infants.
- To establish age-specific norms for thyroid hormones in growing ex-VLBW infants.
Main Methods:
- An observational cohort study was conducted with VLBW infants prior to discharge from a high-dependency nursery.
- Free thyroxine (fT4) and TSH levels were measured and correlated with postmenstrual age.
Main Results:
- A cohort of 129 ex-VLBW infants had thyroid hormones measured at a mean postmenstrual age of 38.5 weeks.
- A fair inverse correlation (r=-0.302) was observed between fT4 levels and postmenstrual age.
- A very weak negative correlation was found between TSH levels and postmenstrual age.
Conclusions:
- A fair inverse correlation exists between fT4 and postmenstrual age in growing ex-VLBW infants, reflecting the maturation of the hypothalamic-pituitary-thyroid axis.
- fT4 levels in growing preterm infants should be interpreted using postmenstrual age-specific norms rather than a single reference interval.
Aim:
There is little information regarding the reference range for thyroid hormones in preterm babies, especially those with very low birth weight (VLBW) of less than 1500 g. The objective of our study was to evaluate the relationship between thyroid hormone levels and postmenstrual age in a cohort of stable VLBW infants.
Method:
An observational cohort study of VLBW infants preparing for discharge from a high-dependency nursery in Singapore. The infants' free thyroxine (fT4) and thyrotropin (TSH) levels were assayed just before discharge and correlated with postmenstrual age, calculated as the sum of the duration of gestation at birth and chronological age in weeks.
Results:
fT4 and TSH levels were sampled in 129 ex-VLBW babies at a mean postmenstrual age of 38.5 (±4.6) weeks. The babies were born at a mean±SD gestation of 28.9±2.4 weeks (median 29.0 weeks, range 24.0-34.5 weeks) with mean±SD birth weight of 1081±268 g (median 1090 g, range 490-1490 g). Linear regression analysis revealed negative and fair correlation between fT4 and postmenstrual age (r=-0.302). The mean±SD fT4 level was 16.8±3.2 pmol/L (median 16.8 pmol/L, range 8.5-28.9 pmol/L). However, there was only a very weak negative correlation between TSH levels and postmenstrual age, both with (r=-0.116) or without logarithmic transformation. The mean±SD TSH was 4.56±2.50 mIU/L (median 4.42 mIU/L, range 1.0-13.5 mIU/L).
Conclusion:
Our study shows a fair and inverse correlation of fT4 with postmenstrual age in a large cohort of growing ex-VLBW infants, in keeping with maturation of the hypothalamic-pituitary-thyroid axis. It suggests that fT4 levels in growing infants are best compared to postmenstrual age-specific norms instead of a single reference interval.

Related Concept Videos
 01:20
Synthesis and Regulation of Thyroid Hormones
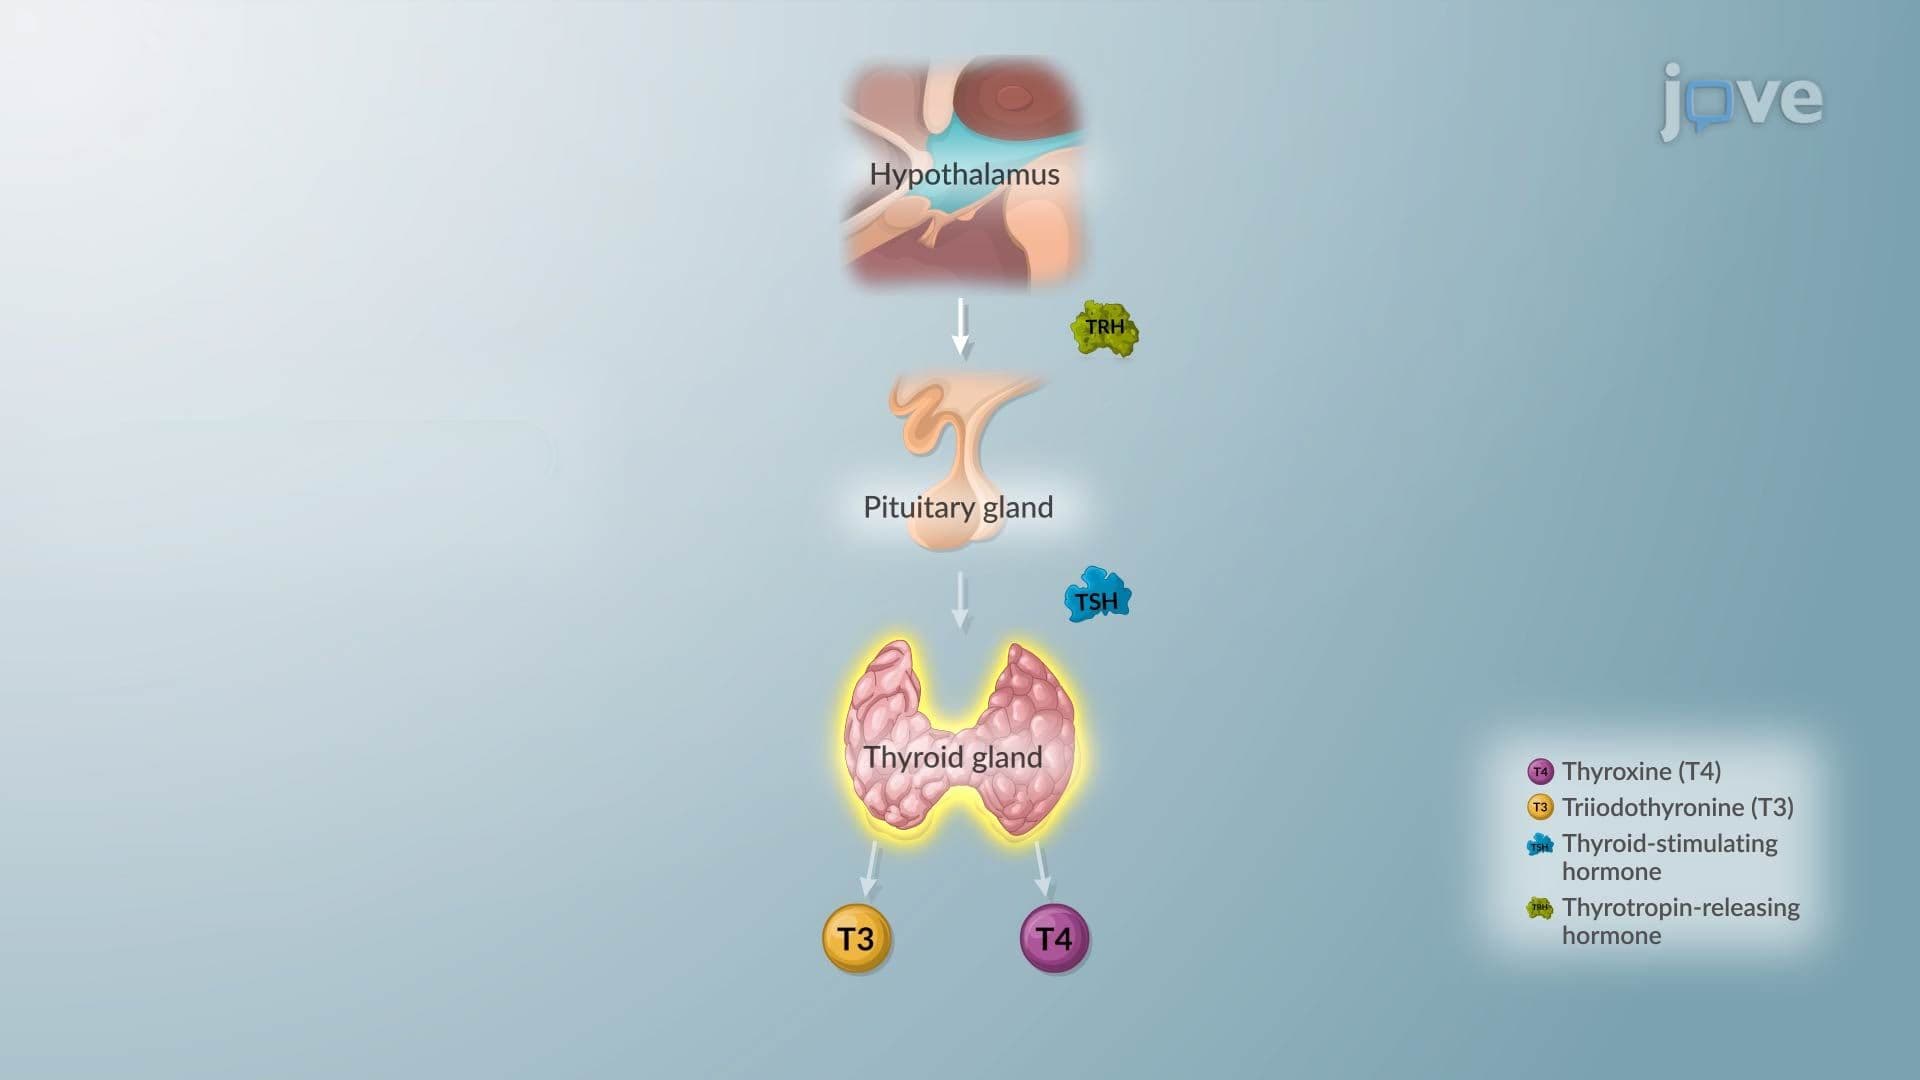
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:23
Hypothyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:27
Hyperthyroidism II: Pathophysiology