End-diastolic flow reversal limits the efficacy of pediatric intra-aortic balloon pump counterpulsation
Related Experiment Video
Updated: May 6, 2026
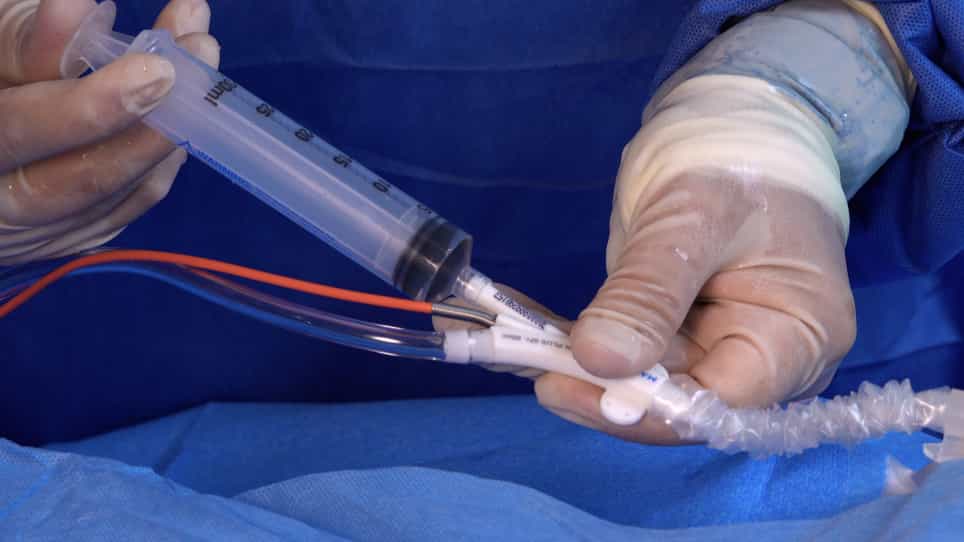
The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Carlo R Bartoli1, Benjamin D Rogers2, Constantine E Ionan3
1Division of Cardiovascular Surgery, University of Pennsylvania, Philadelphia, Pa; MD/PhD Program, University of Louisville School of Medicine, Louisville, Ky.

Insights
Intra-aortic balloon pump (IABP) counterpulsation efficacy in pediatric acute left ventricular failure was not improved by high-fidelity signal timing. Systemic end-diastolic flow reversal limited therapeutic benefits, suggesting alternative strategies are needed.
Area of Science:
- Pediatric Cardiology
- Cardiovascular Physiology
- Biomedical Engineering
Background:
- Intra-aortic balloon pump (IABP) counterpulsation is less established in pediatrics than adults.
- This study investigated IABP efficacy in a pediatric animal model, comparing high-fidelity vs. low-fidelity blood pressure signals for timing.
Purpose of the Study:
- To evaluate if precise IABP timing using high-fidelity signals improves counterpulsation therapy in pediatric acute left ventricular failure.
- To assess the impact of end-diastolic flow reversal on IABP efficacy in this model.
Main Methods:
- Yorkshire piglets with induced left ventricular failure underwent IABP insertion.
- Inflation/deflation timing was controlled using traditional criteria from both low-fidelity (fluid-filled) and high-fidelity (micromanometer) signals.
- Hemodynamic parameters, myocardial oxygen consumption, and blood flow were measured.
Main Results:
- IABP provided diastolic augmentation and afterload reduction but did not improve cardiac output or end-organ flow.
- Significant end-diastolic flow reversal occurred during IABP deflation.
- High-fidelity signal timing did not improve efficacy or reduce flow reversal compared to low-fidelity signals.
Conclusions:
- Systemic end-diastolic flow reversal limits IABP counterpulsation efficacy in pediatric acute left ventricular failure.
- Traditional timing criteria, even with high-fidelity signals, did not enhance IABP effectiveness.
- Alternative deflation timing strategies are necessary for pediatric IABP therapy.
Background:
Counterpulsation with an intra-aortic balloon pump (IABP) has not achieved the same success or clinical use in pediatric patients as in adults. In a pediatric animal model, IABP efficacy was investigated to determine whether IABP timing with a high-fidelity blood pressure signal may improve counterpulsation therapy versus a low-fidelity signal.
Methods:
In Yorkshire piglets (n = 19; weight, 13.0 ± 0.5 kg) with coronary ligation-induced acute ischemic left ventricular failure, pediatric IABPs (5 or 7 mL) were placed in the descending thoracic aorta. Inflation and deflation were timed with traditional criteria from low-fidelity (fluid-filled) and high-fidelity (micromanometer) blood pressure signals during 1:1 support. Aortic, carotid, and coronary hemodynamics were measured with pressure and flow transducers. Myocardial oxygen consumption was calculated from coronary sinus and arterial blood samples. Left ventricular myocardial blood flow and end-organ blood flow were measured with microspheres.
Results:
Despite significant suprasystolic diastolic augmentation and afterload reduction at heart rates of 105 ± 3 beats per minute, left ventricular myocardial blood flow, myocardial oxygen consumption, the myocardial oxygen supply/demand relationship, cardiac output, and end-organ blood flow did not change. Statistically significant end-diastolic coronary, carotid, and aortic flow reversal occurred with IABP deflation. Inflation and deflation timed with a high-fidelity versus low-fidelity signal did not attenuate systemic flow reversal or improve the myocardial oxygen supply/demand relationship.
Conclusions:
Systemic end-diastolic flow reversal limited counterpulsation efficacy in a pediatric model of acute left ventricular failure. Adjustment of IABP inflation and deflation timing with traditional criteria and a high-fidelity blood pressure waveform did not improve IABP efficacy or attenuate flow reversal. End-diastolic flow reversal may limit the efficacy of IABP counterpulsation therapy in pediatric patients with traditional timing criteria. Investigation of alternative deflation timing strategies is warranted.